

Loading, please wait...
Loading, please wait...

The Ministry of Health recently extended the CGHS empanelment deadline to April 30, 2026. This final window allows private hospitals to complete mandatory digital formalities and secure their panel status. Consequently, healthcare providers must finalize their Memorandum of Agreement (MoA) before the cutoff. Any hospital failing to comply will lose its eligibility to treat beneficiaries starting May 1. This de-empanelment directly affects hospital cash flows and patient access. Moreover, only empanelled facilities can offer cashless treatment under the scheme. Because empanelment is strictly tied to reimbursement, any lapse creates significant financial risks. Therefore, administrators should prioritize these submissions to maintain operational continuity and avoid fresh application procedures.
Technical hurdles on the new HEM 2.0 portal prompted this critical extension. While the government aims for transparency, the digital transition has encountered several systemic glitches. Hospitals have reported difficulties in uploading documents and completing applications through the platform. Despite these issues, the Director of CGHS confirmed that authorities will grant no further extensions. Officials clarified that settlement typically takes up to 90 days once a hospital is fully empanelled. However, delays often arise from documentation gaps or unresolved queries. Furthermore, the government highlighted revised rates from late 2025 as an incentive for hospitals to stay compliant. Hospitals must resolve technical errors immediately to meet the final deadline. This proactive approach ensures that they can continue raising claims without interruption.
Q1: What is the final date for hospitals to complete CGHS empanelment?
The final deadline for existing hospitals to sign the MoA and complete formalities is April 30, 2026.
Q2: What happens if a hospital misses the CGHS empanelment deadline?
Hospitals that miss the deadline will be de-empanelled from May 1, 2026. They will no longer be eligible to treat CGHS beneficiaries or raise cashless claims until they complete a fresh application process.
Q3: Why was the deadline extended from March 31 to April 30?
The extension follows reports of technical difficulties and submission delays on the newly launched HEM 2.0 digital portal.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The CGHS empanelment deadline is extended to April 30, 2026. Hospitals missing this window face de-empanelment and loss of cashless treatment eligibility....
6 months ago

Review how tailored exercise programs benefit frail older patients with heart failure. Explore pathophysiological mechanisms, individualized training prescriptions, and strategies to overcome adherence barriers in clinical practice.
Today

Recent clinical studies reveal maternal autoantibodies targeting IL-1RA as potential triggers for preterm labor, opening avenues for targeted cytokine therapies. Concurrently, new perioperative findings show inhaled cannabis increases propofol requirements during upper endoscopy compared to oral edible consumption.
Today
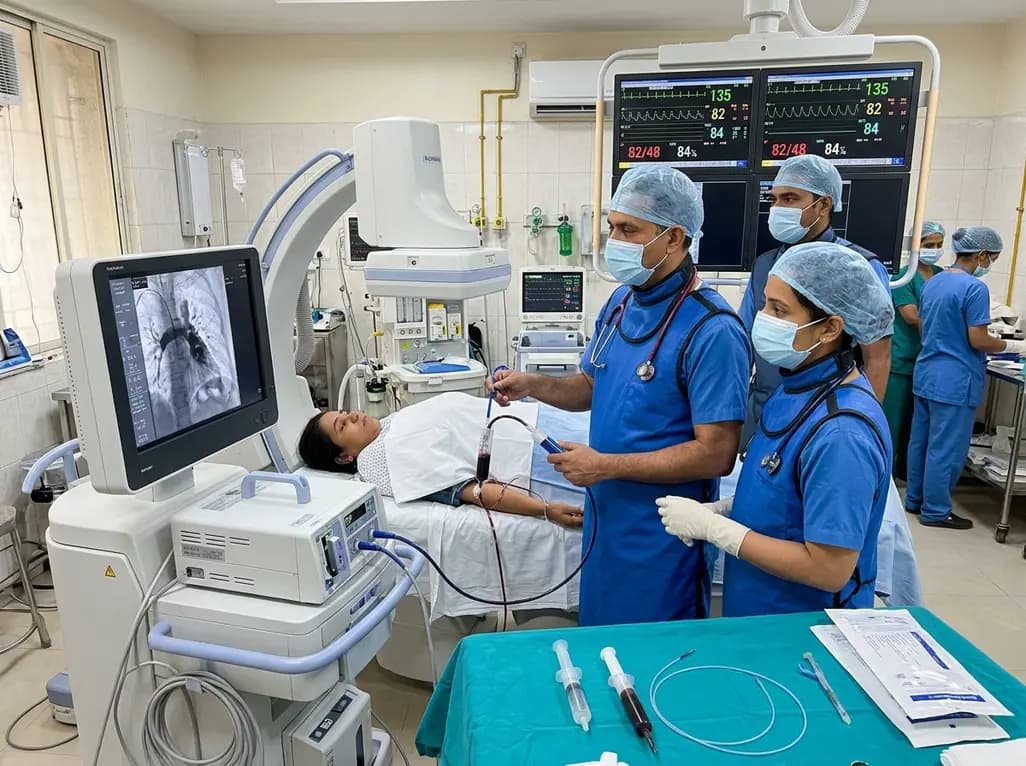
In high-risk pulmonary embolism complicated by severe anemia and active uterine bleeding, systemic thrombolysis is contraindicated. Large-bore aspiration thrombectomy provides rapid hemodynamic rescue without fibrinolysis, supported by inferior vena cava filter placement and multidisciplinary critical care.
Today
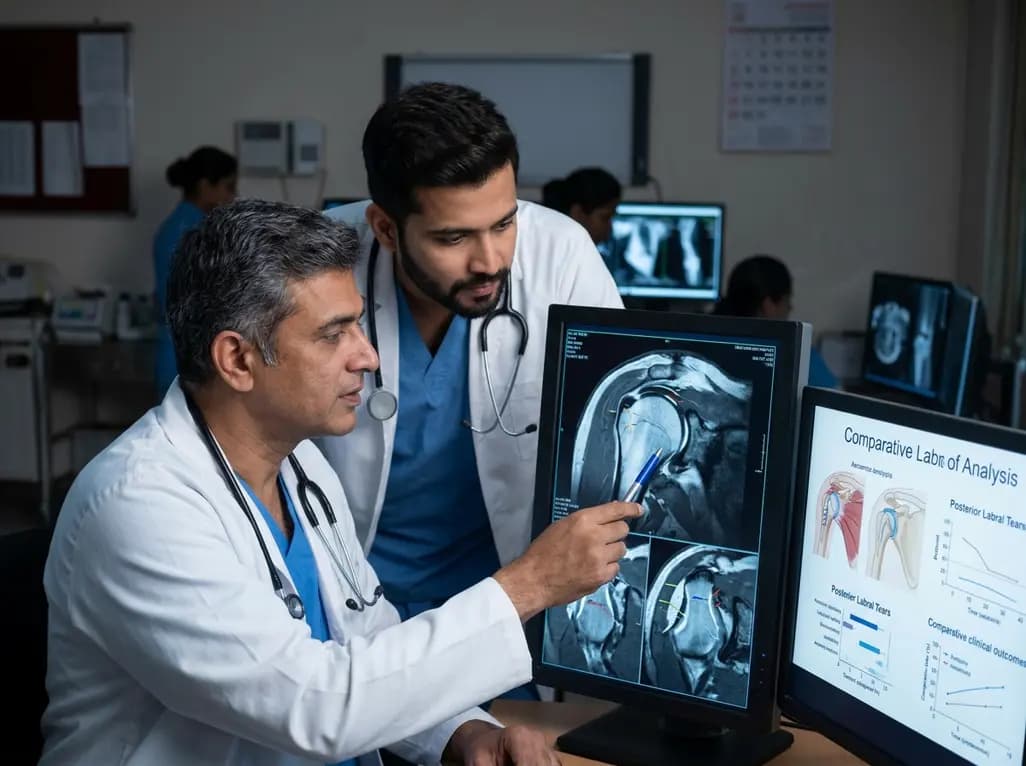
This comparative study evaluates posterior labral tears with and without glenohumeral instability, highlighting distinct demographic patterns, MRI underestimation in stable shoulders, and successful arthroscopic repair outcomes.
Today

A clinical study demonstrates that early intervention with tocilizumab, either as monotherapy or bridged with corticosteroids, achieves significant proptosis reduction and resolves active inflammation in treatment-naive thyroid eye disease.
Today
