

Loading, please wait...
Loading, please wait...

Early-onset epileptic encephalopathies present profound diagnostic challenges for child neurologists and pediatricians. Specifically, CDKL5 deficiency disorder is a severe X-linked neurodevelopmental condition characterized by intractable early-onset epilepsy, developmental impairment, and cortical visual dysfunction. Although seizures typically manifest within the first few weeks of life, initial electroencephalography recordings often show surprisingly mild abnormalities. Consequently, clinicians may experience diagnostic delays or underestimate initial neurodevelopmental trajectory severity. A recent multicenter investigation tracked longitudinal electroencephalography changes over the first two years, providing crucial diagnostic clarity for clinical practice.
During early infancy, baseline cerebral activity often appears deceptively preserved on initial neurophysiological recordings. However, longitudinal analyses demonstrate that electroencephalographic background severity deteriorates significantly across the first twenty-four months of life. Researchers noted that older infants exhibited substantially higher odds of generalized slowing and marked background discontinuity. Specifically, mixed-effects models confirmed that generalized slowing worsened markedly over time, indicating progressive cerebral network dysfunction. Moreover, discontinuity emerged as a prominent feature that distinguished later infancy from earlier neonatal recordings. In addition, physiological sleep architecture gradually degraded, showing an absence of expected vertex waves and normal sleep spindles. These progressive background abnormalities closely reflect worsening epileptic encephalopathy rather than benign developmental delays. Therefore, clinicians must avoid false reassurance from relatively mild baseline tracings obtained during early infancy. Instead, medical teams should schedule serial electroencephalograms whenever infants demonstrate persistent developmental plateaus or clinical spasms. Early neurophysiological vigilance enables physicians to adjust therapy proactively before severe background degradation occurs. Furthermore, tracking background organization aids clinicians in distinguishing medication effects from intrinsic encephalopathic progression. Timely identification of continuous slowing helps guide neuroprotective strategies and individualized drug titration.
Beyond progressive background slowing, interictal patterns in this condition display distinctive regional neurophysiological distributions. In particular, paroxysmal fast activity demonstrates a striking predilection for the parieto-occipital brain regions compared with frontal, central, or temporal areas. Furthermore, focal slowing and sharp epileptiform transients consistently concentrate over these posterior quadrants. Clinicians frequently encounter substantial diagnostic uncertainty when evaluating various early infantile developmental epileptic encephalopathies. Nevertheless, the prominent occurrence of parieto-occipital paroxysmal fast activity provides an exceptionally valuable diagnostic clue. While paroxysmal fast bursts occur across diverse genetic epilepsies, this posterior localization correlates closely with cortical visual impairment, a cardinal clinical hallmark. Consequently, identifying persistent posterior epileptiform discharges should immediately prompt clinicians to initiate targeted genetic investigations. Furthermore, these regional electroencephalographic abnormalities mirror underlying disruptions in posterior corticothalamic circuits. Recognizing this electrophysiological hallmark can accelerate confirmatory genetic sequencing and optimize subsequent interventions. Moreover, understanding this focal vulnerability assists neurophysiologists in differentiating this disorder from nonspecific metabolic encephalopathies. Specifically, these distinctive fast rhythms serve as an essential neurophysiological bio-signature in early differential diagnosis.
The clinical semiology of seizures evolves in a highly stereotypic chronological pattern during early infancy. Initially, infants experience subtle focal seizures or brief tonic posturing during the first three months of life. Subsequently, epileptic spasms and sustained tonic seizures become the predominant manifestations between six and fourteen months. Epileptic spasms specifically reach their peak frequency between seven and eleven months of age. Furthermore, children frequently exhibit complex sequential seizures, which represent a distinctive clinical hallmark of the disorder. These sequential events typically consist of a two-stage semiology, beginning with a tonic phase that transitions directly into epileptic spasms. Because families may only notice the final motor spasms, caregivers often fail to report the subtle preceding tonic stiffening. Accordingly, continuous video-electroencephalography monitoring provides indispensable diagnostic clarity for capturing these rapid multi-phase seizures. Recognizing this sequenced progression helps neurologists avoid misdiagnosing these events as isolated infantile spasms. Accurate clinical classification directly informs therapeutic decisions, enabling clinicians to select tailored, comprehensive anticonvulsant regimens. In addition, recognizing early semiologic shifts allows pediatric teams to modify seizure management protocols before clusters escalate into status epilepticus.
Standardized electroencephalographic scoring provides objective metrics to evaluate disease progression and underlying network destabilization over time. In this multicenter cohort, investigators utilized the Burden of AmplitudeS and Epileptiform Discharges scale to grade interictal severity. Remarkably, researchers identified nine months as the critical discriminatory cutoff age for detecting high-severity scores. Prior to nine months, infants often retained lower scores despite having frequent daily clinical seizures. However, after nine months of age, high-severity scores indicating overt epileptic encephalopathy increased substantially across the cohort. The nine-month threshold demonstrated excellent specificity of ninety-five percent and a sensitivity of sixty-two percent. Consequently, this timeframe marks a crucial physiological transition where secondary epileptic networks consolidate and destabilize background rhythms. Hypsarrhythmia also emerged primarily during this developmental window, reinforcing the biological vulnerability of this transitional period. Pediatric neurologists should therefore anticipate significant electrographic deterioration toward the end of the first year of life. Serial electrophysiological monitoring around this critical developmental window remains indispensable for objectively evaluating ongoing treatment response. Consequently, clinicians can modify therapies before irreversible cognitive deceleration becomes entrenched.
Neurophysiological abnormalities exert a measurable negative impact on functional neurodevelopmental milestones in affected young children. Statistical analyses revealed that lower developmental scale scores correlated strongly with older chronological age and electroencephalographic hypsarrhythmia. In addition, the presence of confirmed epileptic encephalopathy showed an exceptionally strong inverse relationship with developmental progress. Moreover, children who exhibited parieto-occipital epileptiform abnormalities and paroxysmal fast activity experienced significantly poorer cognitive and motor outcomes. These correlations demonstrate that persistent epileptiform activity directly impairs emerging neural connectivity during critical developmental windows. Consequently, treating physicians must prioritize aggressive suppression of interictal discharges alongside overt seizure control. While achieving complete seizure freedom remains difficult, mitigating high discharge burdens may preserve functional potential. Therefore, neurologists should integrate formal neurodevelopmental assessments into routine clinical follow-up visits. Furthermore, therapeutic interventions should target both electrographic patterns and clinical seizures simultaneously. Accordingly, comprehensive developmental therapies must begin promptly to maximize functional capabilities. Early physical and occupational therapy can significantly mitigate long-term neuromuscular disability. Additionally, close interdisciplinary collaboration between pediatric neurologists and therapists ensures proactive intervention as developmental hurdles emerge.
During the earliest weeks of life, routine recordings often appear deceptively normal or show only mild background slowing. However, as infants mature, generalized background slowing, progressive discontinuity, and parieto-occipital paroxysmal fast activity emerge. Clinicians must maintain ongoing neurophysiological monitoring because early mild tracings frequently deteriorate into severe epileptic encephalopathy.
Statistical analyses identify nine months as the optimal cutoff age for developing high-severity scores on the BASED scale. At this developmental milestone, underlying epileptic networks consolidate, leading to overt epileptic encephalopathy and hypsarrhythmia. Consequently, neurophysiologists observe significant electrographic degradation, which strongly correlates with worsening developmental and clinical outcomes.
Sequential seizures classically manifest as a distinct two-stage clinical event, occurring most frequently between seven and eleven months of age. Typically, an initial focal or tonic phase rapidly evolves into clustered epileptic spasms. Recognizing this biphasic sequence helps clinicians differentiate the condition from isolated infantile spasms and guides effective therapy.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A multicenter longitudinal study reveals that neurophysiological severity in CDKL5 deficiency disorder progressively worsens over the first two years of life, highlighting key diagnostic markers.
Today
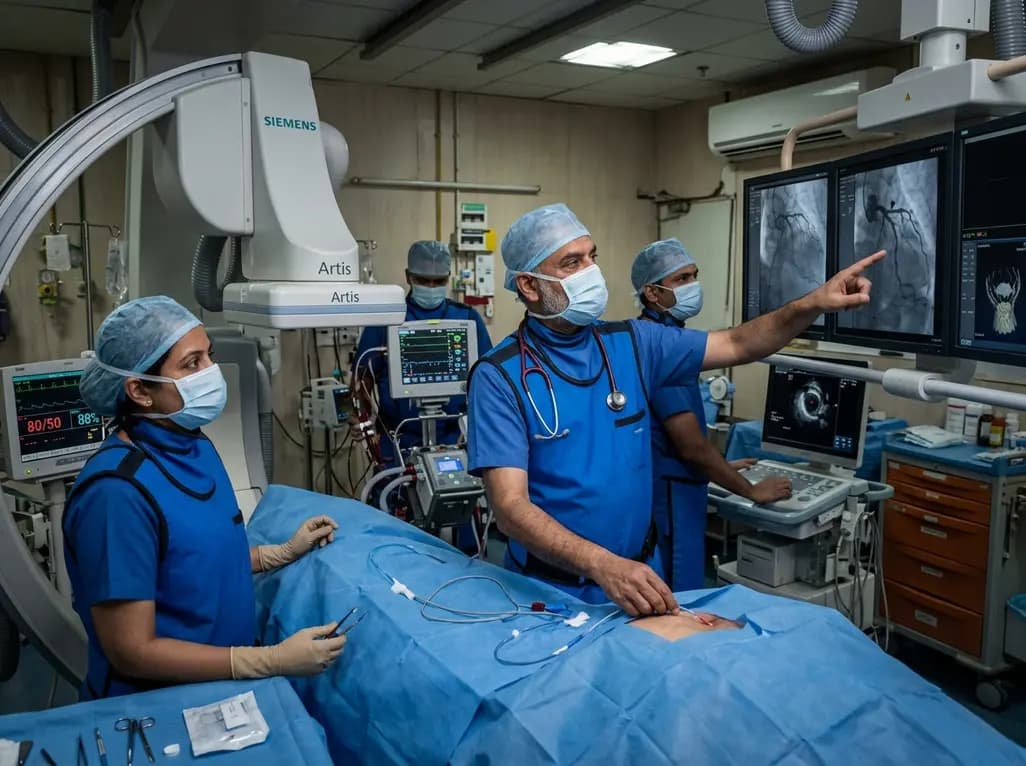
A rare case of acute coronary obstruction during TAVR caused by suspected calcified amorphous tumor embolization underscores the critical role of intracardiac imaging, emergency ECMO, and the paradox of enlarged-aperture valve geometry.
Today

Prelacteal feeding persists in South Asian communities despite known clinical risks. This review examines determinants from Chitral, pathophysiological hazards, and pediatric strategies to eliminate harmful feeds and support exclusive breastfeeding.
Today

Transcatheter mitral valve replacement in patients with degenerated bioprostheses carries a substantial risk of LVOT obstruction. Combining leaflet modification via the BATMAN technique with mechanical circulatory support offers a viable, life-saving solution for anatomically challenging surgical candidates.
Today

A comparative cohort study demonstrates that patients undergoing total hip arthroplasty after prior hip arthroscopy achieve comparable functional recovery, low complication rates, and equivalent implant survivorship when conversion occurs after six months.
Today

A cross-sectional study of 320 adults evaluated the link between habitual fasting duration and dietary quality using Nutrition Quotient scores, highlighting the clinical necessity of balancing time-restricted eating with nutrient density and meal quality in routine metabolic practice.
Today
