

Loading, please wait...
Loading, please wait...

Cardiometabolic diseases increasingly present as complex, overlapping conditions rather than isolated disorders. Traditional risk calculators generally rely on single biomarkers and static risk scores. Consequently, conventional frameworks often fail to capture individual patient heterogeneity. Therefore, understanding cardiometabolic disease progression requires a more granular evaluation of physiological phenotypes. A landmark study published in Diabetes, Obesity and Metabolism addressed this unmet clinical need by utilizing machine learning to analyze large population cohorts. Specifically, researchers examined data from 337,334 participants in the UK Biobank who were initially free of type 2 diabetes, ischaemic heart disease, and stroke. Through unsupervised clustering, the investigators identified discrete clinical subtypes that follow remarkably distinct longitudinal trajectories. Furthermore, the team coupled clinical parameters with circulating metabolomic and proteomic profiles. As a result, this integrated approach clarifies how subclinical dysregulation accelerates transition across discrete disease stages. Ultimately, for practicing physicians, these findings offer a compelling framework to transcend single-organ assessment.
To delineate these risk groups, the investigators applied Multi-task Deep LASSO algorithms to select twelve routine clinical variables. Subsequently, they performed K-means clustering across the massive cohort. This rigorous approach generated four risk-informed phenotypes: metabolically healthy, older cardio-renal-metabolic, lean hypercholesterolaemia, and early-onset metabolic syndrome. Importantly, the variables comprised routine measurements accessible in standard outpatient clinics, including lipid fractions, glycemic indices, renal function markers, and anthropometric metrics. Thus, the stratification relies on readily available tests rather than exotic diagnostic tools. In addition, the researchers employed multi-state Cox proportional hazards models to follow disease transitions over a median follow-up of thirteen years. Unlike traditional survival analyses that assess single endpoints, multi-state modelling tracks the progression from baseline health to a first cardiometabolic disease. Moreover, it captures subsequent transitions to cardiometabolic multimorbidity and all-cause mortality. Because South Asian and global populations face escalating multimorbidity, this dynamic methodology provides vital prognostic precision.
Longitudinal follow-up revealed striking divergences in clinical trajectories among the four identified phenotypes. Notably, participants in the older cardio-renal-metabolic subtype exhibited the highest risk of developing a first cardiometabolic disease. Furthermore, these individuals demonstrated the fastest transition from initial disease to complex cardiometabolic multimorbidity. Both the older cardio-renal-metabolic and early-onset metabolic syndrome groups showed robust prospective associations with incident type 2 diabetes. In contrast, the lean hypercholesterolaemia phenotype displayed a distinct pathological trajectory. Specifically, lean hypercholesterolaemic individuals experienced stronger relative associations with ischaemic heart disease and stroke than with type 2 diabetes. However, age adjustment attenuated several associations with stroke and coronary disease in older groups. Meanwhile, diabetes associations remained resilient after demographic adjustments. These divergent patterns highlight that identical baseline lipid abnormalities produce different clinical sequelae depending on systemic metabolic context. Consequently, treating physicians must tailor preventive therapies based on comprehensive phenotype rather than isolated cholesterol numbers.
To uncover underlying biological drivers, the authors profiled 251 plasma metabolic measures and circulating proteins across the cohort. Phenotypes exhibited markedly divergent metabolic signatures that mirrored their clinical trajectories. Specifically, functional protein enrichment analyses revealed prominent activation of complement cascades, coagulation pathways, and vascular remodelling processes. These biological pathways explain why patients with combined cardio-renal-metabolic dysfunction experience accelerated vascular damage. In addition, metabolite panels modestly improved predictive discrimination beyond comprehensive clinical models. Incorporating these panels increased the ten-year area under the receiver operating characteristic curve for cardiometabolic multimorbidity from 0.834 to 0.848. Interestingly, adding cluster membership on top of metabolite data provided limited incremental statistical gain. Nevertheless, the molecular profiles validate the biological authenticity of these data-driven clinical phenotypes. Therefore, routine biomarkers effectively reflect deep circulating omic pathology. This biological alignment reassures clinicians that standard laboratory panels capture meaningful molecular dysfunction.
These empirical findings carry profound implications for contemporary preventive medicine and chronic disease management. Historically, guidelines have promoted broad risk categories that often overlook atypical presentations, such as lean individuals with atherogenic lipid profiles. By distinguishing lean hypercholesterolaemia from classic metabolic syndrome, clinicians can individualize therapeutic interventions more effectively. For example, patients with early-onset metabolic syndrome warrant intensive lifestyle modification, insulin sensitization, and weight management. Conversely, clinicians should evaluate lean hypercholesterolaemic patients for targeted lipid lowering and early vascular screening. Furthermore, patients with cardio-renal-metabolic phenotypes require aggressive multidisciplinary treatment, including sodium-glucose cotransporter-2 inhibitors and renin-angiotensin-aldosterone system blockers. Although external validation across diverse multi-ethnic populations remains essential, these phenotypes provide an intuitive roadmap. Consequently, adopting subtype-informed care empowers clinicians to intercept disease trajectories before patients advance to debilitating multimorbidity.
The transition from a solitary diagnosis to multimorbidity represents a critical turning point in patient survival and functional autonomy. Therefore, early identification of high-risk trajectories is crucial for reducing hospitalizations and premature mortality. In populations with severe metabolic burdens, such as South Asians, individuals often develop cardiometabolic diseases at younger ages and lower body mass indices. Accordingly, the early-onset metabolic syndrome and lean hypercholesterolaemia subtypes identified in this research resonate strongly with daily clinical encounters. Moreover, dynamic multi-state modeling underscores that preventing the initial cardiometabolic event dramatically curbs subsequent transition to multisystem failure. Healthcare systems must therefore transition from fragmented episodic care toward coordinated cardiometabolic surveillance. In conclusion, integrating routine clinical parameters into algorithmic subtyping allows providers to deliver precise, proactive, and equitable chronic disease prevention.
Standard risk calculators primarily estimate short-term probability for single vascular endpoints and overlook multisystem interactions. In contrast, data-driven clustering integrates twelve routine biomarkers to map patients into distinct biological trajectories. Consequently, this approach captures whether an individual is prone to isolated atherothrombotic events or rapid transition toward cardiometabolic multimorbidity. Clinicians can therefore tailor preventive strategies, surveillance frequency, and pharmacotherapy to the specific pathophysiological trajectory rather than relying on one-size-fits-all algorithms.
Unlike classic metabolic syndrome, the lean hypercholesterolaemia phenotype presents without severe obesity, marked hyperglycemia, or overt renal impairment. However, individuals within this group harbor elevated atherogenic lipid particles that drive early macrovascular injury. Consequently, these patients exhibit a disproportionate relative risk for developing ischaemic heart disease and stroke rather than type 2 diabetes. Recognizing this unique presentation ensures that clinicians do not mistakenly overlook cardiovascular danger in non-obese patients who appear otherwise healthy.
Traditional survival analyses usually evaluate time to a single primary endpoint, which treats health and disease as binary outcomes. Multi-state modelling, however, evaluates successive clinical transitions from health to first disease, subsequently to multimorbidity, and ultimately to death. Therefore, it illustrates the full disease continuum over extended follow-up periods. This granular perspective helps clinicians identify critical therapeutic windows where targeted intervention can halt transition from a single chronic illness into complex multisystem multimorbidity.
Disclaimer: This content is for informational and educational purposes only. It is not intended as medical advice. Healthcare professionals should exercise independent clinical judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A large UK Biobank study identified four routine biomarker subtypes that predict cardiometabolic disease progression to multimorbidity. Integrating multi-state modelling, metabolomics, and proteomics revealed distinct biological pathways, offering new avenues for tailored clinical risk stratification.
last month

Gastrointestinal smooth muscle cells rely on nanoscale membrane domains to integrate mechanosensitive currents. Recent insights show that nanodomain architecture, rather than channel properties alone, orchestrates motility, opening new therapeutic avenues for clinical dysmotility and gastrointestinal aging.
Today

A landmark study reveals that lipid-rich malignant ascites alters the T-cell metabolic transcriptome, causing cholesterol efflux and impaired fatty acid oxidation. This suppresses TCR signalling and blocks BiTE immunotherapy, while lipid depletion restores antitumour cytotoxicity in ovarian cancer.
Today
Novel clinical evidence demonstrates the feasibility of combining VA-ECMO with the NyokAssist self-expanding transvalvular pump for active left ventricular unloading in infarct-related cardiogenic shock, achieving successful stabilization and decannulation.
Today
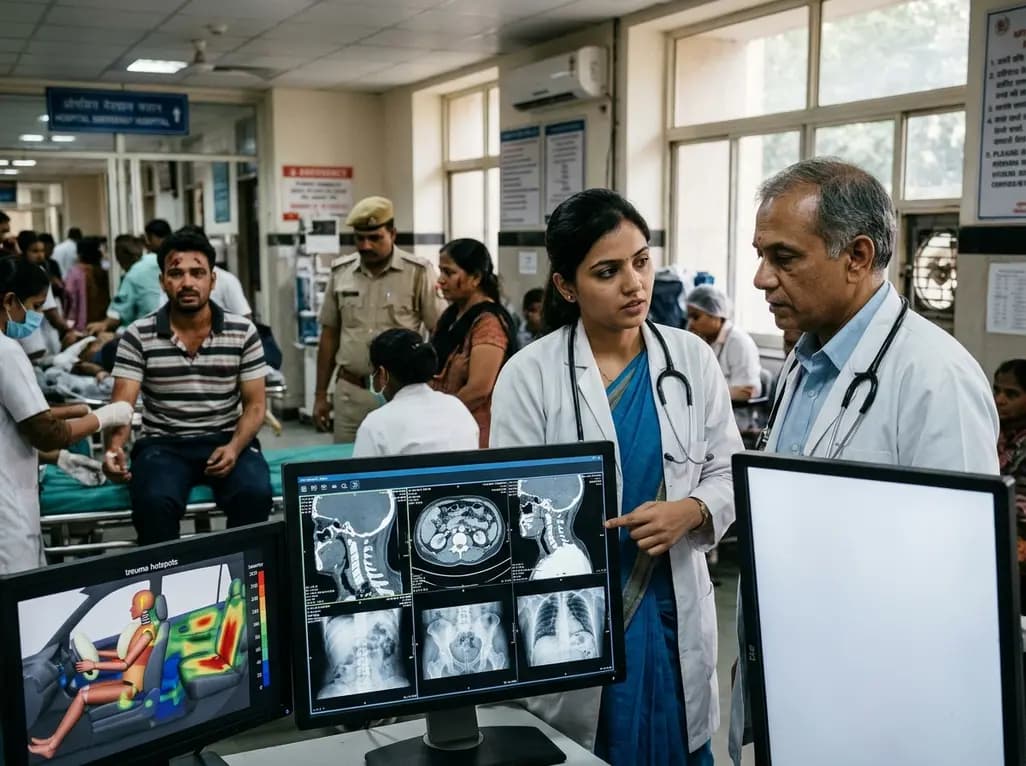
Recent crash analyses demonstrate significant variations in traffic injury severity across vehicle seating positions. Electric vehicle passengers face disproportionately higher trauma risks than drivers, particularly during airbag deployments, demanding adapted emergency assessment and clinical vigilance.
Today

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
