

Loading, please wait...
Loading, please wait...

Severe acquired brain injury frequently leaves survivors with profound neurological and cognitive deficits. Among these complications, an impairment in self-awareness presents a major challenge to functional recovery. Clinicians frequently encounter patients who fail to recognize their physical, sensory, or cognitive limitations. Consequently, evaluating self-awareness in brain injury represents a pivotal step during post-acute neurorehabilitation. When individuals lack insight into their deficits, they often resist therapeutic recommendations and refuse compensatory strategies. Furthermore, this lack of recognition frequently leads to hazardous behaviors, substantially increasing the risk of secondary trauma. Accurate assessment frameworks are therefore essential to guide therapeutic engagement and improve long-term functional independence.
Impairment in self-awareness prevents individuals from perceiving changes in their physical capabilities and cognitive functioning. Consequently, rehabilitation teams face major hurdles when attempting to engage patients in structured therapy. Survivors with limited insight rarely perceive the necessity for rigorous physical or occupational interventions. Instead, they often attempt unsupported ambulation or operate appliances prematurely, creating immediate physical hazards. Moreover, this unawareness commonly triggers severe frustration between patients, clinical staff, and family members. Caregivers experience significant emotional distress because relatives may perceive safety precautions as arbitrary limitations imposed by healthcare providers. In addition, the inability to appreciate neurocognitive deficits impairs vocational reintegration and social participation. Therefore, early identification of awareness deficits is vital for patient safety and targeted goal setting. Clinicians must distinguish organic cognitive anosognosia from psychological defense mechanisms like denial. Because organic deficits stem from widespread disruption in frontoparietal networks, standard motivational counseling alone rarely resolves the issue. Instead, comprehensive neurorehabilitation demands structured cognitive retraining coupled with objective task appraisals.
Traditional assessment methodologies for self-awareness rely predominantly on declarative discrepancy measures. In these standard protocols, clinicians administer questionnaires assessing functional competence to both the patient and an informed family member. Researchers then calculate discrepancy scores to determine insight impairment. However, recent systematic analyses reveal substantial limitations with this retrospective approach. First, questionnaire responses capture only intellectual insight, meaning a patient can verbally state their diagnosis without appreciating practical implications. Second, proxy ratings introduce noticeable observer bias. Family members dealing with acute caregiver burden often underreport or exaggerate patient deficits depending on their emotional fatigue. Third, intellectual awareness measured via static questionnaires fails to predict whether a patient will recognize errors in real-world scenarios. Therefore, declarative assessments provide an incomplete portrait of metacognitive capabilities. Clinicians frequently observe individuals who acknowledge memory difficulties during an interview yet consistently refuse memory aids during daily activities. Consequently, relying solely on declarative metrics obscures subtle executive dysfunctions that compromise patient safety in unstructured environments.
To construct more effective diagnostic paradigms, modern neuropsychology distinguishes between offline and online levels of self-awareness. Offline awareness reflects declarative knowledge regarding personal strengths and weaknesses outside the immediate performance context. Conversely, online awareness involves the dynamic appraisal of cognitive performance during active task execution. Online awareness further divides into emergent awareness and anticipatory awareness. Emergent awareness describes the capacity to recognize an error as it occurs in real time. Anticipatory awareness represents the highest metacognitive level, where an individual anticipates potential errors before beginning a demanding activity. Unfortunately, existing clinical literature concentrates almost exclusively on static offline evaluations. When neurorehabilitation teams evaluate only offline declarative insight, they overlook critical deficits in online self-monitoring. Patients who exhibit intact offline verbal awareness often demonstrate profound deficits in emergent error correction. As a result, comprehensive neurocognitive assessments must evaluate whether a patient can monitor live performance and implement adaptive strategies during real-time cognitive and physical tasks.
Addressing critical gaps highlighted in systematic reviews requires a refined classification of offline cognitive capacity. Historically, offline self-awareness was treated as a monolithic, intellectual construct. However, researchers now emphasize that offline awareness contains distinct subcomponents, including declarative and anticipatory dimensions. Declarative offline awareness involves answering structured questionnaires about perceived competence in physical, emotional, and cognitive domains. In contrast, offline anticipatory self-awareness involves an individual's capacity to predict future performance on specific, upcoming tasks prior to initiating them. When clinicians separate offline declarative insight from offline anticipatory estimation, they gain deeper insight into executive oversight. For example, predicting how many items one will remember from a list represents offline anticipatory awareness. Comparing advance predictions with actual performance provides an objective, quantified index of insight without relying on subjective caregiver reports. Furthermore, this classification reconciles discrepancies observed between verbal knowledge and behavioral execution. Adopting this refined framework enables clinicians to pinpoint exact metacognitive deficits and tailor restorative interventions effectively.
Integrating refined awareness metrics into clinical practice allows multidisciplinary teams to design targeted, evidence-based neurorehabilitation protocols. Clinicians must transition beyond static questionnaires and incorporate structured performance-based feedback protocols. Specifically, therapists can ask patients to predict their performance before attempting a simulated task of daily living. Following task execution, patients evaluate their actual success against their initial predictions and review objective performance data. This structured contrast fosters genuine emergent and anticipatory insight within a supportive environment. Furthermore, multidisciplinary teams in neurotrauma units should coordinate speech, physical, and occupational therapies around consistent metacognitive prompting. Rather than simply correcting patient errors, clinicians should guide individuals to recognize their own missteps through strategic questioning. In addition, addressing co-occurring emotional indifference, such as anosodiaphoria, is essential for sustained therapeutic motivation. When clinicians systematically target both online and offline awareness, patients achieve greater functional independence, adopt compensatory strategies reliably, and safely navigate community reintegration.
Advancing the clinical management of awareness deficits requires multi-center validation of standardized, multi-level evaluation scales. Future clinical research must focus on establishing normative data across diverse cohorts, including traumatic brain injury, stroke, and anoxic encephalopathy. In addition, integrating digital health technologies and virtual reality simulations could revolutionize real-time cognitive monitoring. Immersive simulations allow clinicians to assess anticipatory and emergent awareness safely within ecologically valid, complex environments. Furthermore, neuroimaging investigations should continue exploring functional connectivity between the prefrontal cortex, insula, and default mode network to clarify the neurobiological substrates of metacognitive monitoring. Standardizing diagnostic terminology will also ensure consistent communication among physiatrists, neurologists, neuropsychologists, and allied rehabilitation therapists worldwide. Ultimately, refining assessment paradigms will transform neurorehabilitation from intuitive clinical management into precise, personalized neurological care.
Impaired self-awareness significantly impedes rehabilitation engagement because affected patients fail to recognize their functional limitations. Consequently, they often reject therapeutic recommendations, neglect compensatory strategies, and engage in unsafe activities. This resistance elevates secondary injury risks and hinders functional independence, ultimately prolonging hospital stays and increasing long-term caregiver burden across post-acute recovery phases.
Offline self-awareness represents declarative knowledge regarding general strengths and weaknesses evaluated outside active task execution. In contrast, online self-awareness occurs during active performance. Online awareness includes emergent insight, which is recognizing an error as it occurs, and anticipatory insight, which is the capacity to predict potential obstacles before starting an activity.
Caregiver discrepancy ratings frequently introduce subjective bias due to psychological distress, emotional burnout, or variable familiarity with specific cognitive demands. Furthermore, these ratings capture only general declarative awareness rather than real-time performance monitoring. Relying solely on caregiver reports therefore overlooks dynamic emergent and anticipatory awareness deficits during daily functional tasks.
Disclaimer: This content is for informational and educational purposes only. It is not intended to provide medical advice, diagnosis, or treatment and should not replace consultation with qualified healthcare professionals. While we strive for accuracy, medical information evolves rapidly, and clinical decisions should be individualized. Clinicians should use their clinical judgment and check multiple sources before relying on this information. The authors and publishers are not liable for any actions taken based on this content. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Evaluating self-awareness after severe acquired brain injury requires clinicians to move beyond simple declarative questionnaires. Assessing both offline anticipatory insight and dynamic online performance optimizes neurorehabilitation outcomes and patient safety.
Today
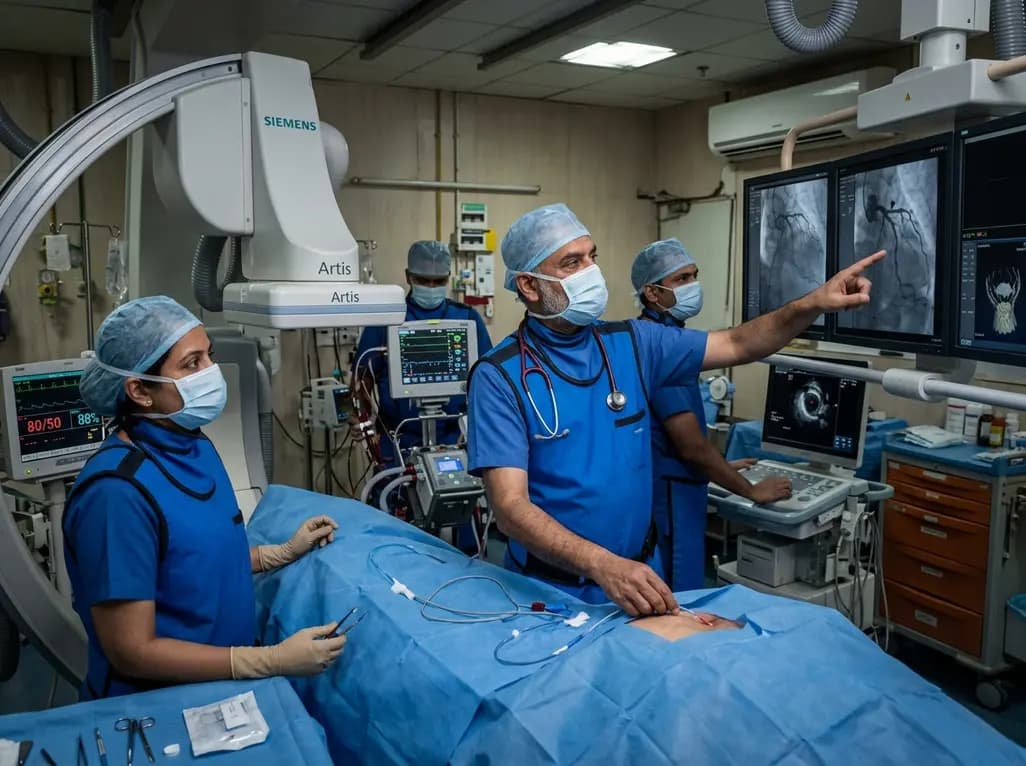
A rare case of acute coronary obstruction during TAVR caused by suspected calcified amorphous tumor embolization underscores the critical role of intracardiac imaging, emergency ECMO, and the paradox of enlarged-aperture valve geometry.
Today

Prelacteal feeding persists in South Asian communities despite known clinical risks. This review examines determinants from Chitral, pathophysiological hazards, and pediatric strategies to eliminate harmful feeds and support exclusive breastfeeding.
Today

Transcatheter mitral valve replacement in patients with degenerated bioprostheses carries a substantial risk of LVOT obstruction. Combining leaflet modification via the BATMAN technique with mechanical circulatory support offers a viable, life-saving solution for anatomically challenging surgical candidates.
Today

A comparative cohort study demonstrates that patients undergoing total hip arthroplasty after prior hip arthroscopy achieve comparable functional recovery, low complication rates, and equivalent implant survivorship when conversion occurs after six months.
Today

A cross-sectional study of 320 adults evaluated the link between habitual fasting duration and dietary quality using Nutrition Quotient scores, highlighting the clinical necessity of balancing time-restricted eating with nutrient density and meal quality in routine metabolic practice.
Today
