

Loading, please wait...
Loading, please wait...

Herpes zoster results from the reactivation of latent varicella-zoster virus within the sensory ganglia. Consequently, prompt initiation of antiviral therapy remains essential to limit viral replication and alleviate acute pain. Clinicians frequently choose valaciclovir for herpes zoster because it offers superior oral bioavailability compared with standard oral acyclovir. Furthermore, randomized controlled trials demonstrate that early intervention with valaciclovir accelerates cutaneous healing and reduces the duration of acute neuritis. Therefore, valaciclovir has become an established standard of care across global clinical practice guidelines.
In recent years, novel agents have emerged to expand treatment options for cutaneous viral conditions. For instance, researchers developed amenamevir, an oral helicase-primase inhibitor that blocks viral unwinding without requiring viral thymidine kinase activation. In clinical trials, amenamevir demonstrated non-inferior clinical efficacy compared with valaciclovir regarding the cessation of new lesion formation. However, clinicians must weigh clinical equivalency against economic costs when selecting therapies. Because healthcare budgets face increasing constraints, economic evaluations provide vital insights for drug selection. Thus, understanding the relative value of these antiviral regimens assists clinicians and healthcare systems in making balanced therapeutic decisions.
To evaluate the comparative economic outcomes of antiviral therapy, researchers constructed a comprehensive decision tree model. Specifically, the model incorporated direct clinical efficacy data from a Japanese randomized controlled trial comparing amenamevir against valaciclovir. Heterogeneity across older clinical trials precluded a harmonized quantitative synthesis of other antiviral agents. Therefore, the investigators focused specifically on this direct head-to-head comparison to maintain analytical precision.
In addition, the researchers integrated utility estimates derived from a dedicated cohort of patients suffering from herpes zoster. They extracted direct medical costs from the 2024 Japanese Medical Fee Schedule and the official 2025 Drug Price List. Furthermore, the economic model adopted a formal healthcare payer perspective over a short-term analytical horizon. The authors conducted both deterministic and probabilistic sensitivity analyses to evaluate the stability of their findings under varying clinical assumptions. Similarly, they performed subgroup evaluations and cost-minimization analyses to explore potential variations among specific patient populations. Consequently, this rigorous methodological framework generated reliable estimates of incremental costs and health gains associated with both regimens.
The health economic analysis revealed significant cost disparities between the two antiviral strategies. Specifically, treatment with amenamevir increased overall direct healthcare costs by 10,010 Japanese yen compared with valaciclovir. Meanwhile, the clinical outcomes yielded an incremental quality-adjusted life-year difference of negative 0.000009. Because the clinical efficacy of both agents was virtually identical in clinical trials, amenamevir failed to generate any measurable health gain. Consequently, the incremental net monetary benefit for amenamevir was negative 10,056 Japanese yen.
Furthermore, probabilistic sensitivity analyses reinforced these baseline economic findings across thousands of simulated cohorts. At a standard willingness-to-pay threshold of 5,000,000 Japanese yen per quality-adjusted life-year, amenamevir achieved cost-effectiveness in only 21.1% of simulations. Thus, in nearly four out of five scenarios, valaciclovir proved economically superior. Because valaciclovir provides equivalent symptomatic relief at a substantially lower acquisition cost, it dominated the economic model. Therefore, health economists concluded that amenamevir does not meet accepted standards for cost-effectiveness under current reimbursement prices. In contrast, valaciclovir reliably delivers high clinical value without inflating medical expenditures.
To contextualize these economic calculations, investigators analyzed real-world claims data from fiscal year 2023. This real-world examination demonstrated an unexpected disconnect between economic value and prescribing behavior. Notably, amenamevir accounted for approximately 44% of all patients treated for acute herpes zoster during that fiscal year. However, because of its premium pricing structure, amenamevir consumed nearly 80% of total antiviral drug expenditures. Consequently, this single medication imposed a disproportionate financial burden on the healthcare reimbursement system.
Moreover, these findings highlight how rapid market adoption of expensive therapies can strain national drug budgets. Physicians often favor amenamevir due to its convenient once-daily dosing and absence of renal dose adjustment requirements. Nevertheless, the real-world budgetary impact underscores the necessity of value-based pricing models. When a novel drug provides non-inferior clinical outcomes without tangible health gains, premium pricing becomes difficult to defend economically. Therefore, healthcare administrators must implement targeted prescribing criteria to ensure responsible utilization. As a result, balancing clinician convenience with systemic affordability remains a pressing priority for modern healthcare governance.
From a clinician perspective, antiviral selection requires balancing pharmacological efficacy, patient compliance, and economic responsibility. Clinicians recognize that valaciclovir delivers dependable viral suppression when initiated within 72 hours of rash onset. In addition, valaciclovir significantly shortens the duration of acute pain and lowers the incidence of persistent postherpetic neuralgia. Although valaciclovir requires dose adjustments in patients with impaired renal function, careful baseline screening mitigates nephrotoxic risks. Therefore, routine laboratory monitoring enables safe outpatient administration across diverse clinical demographics.
In contrast, amenamevir offers genuine pharmacodynamic advantages for patients with moderate to severe renal impairment. Because the drug undergoes non-renal clearance pathways, physicians can prescribe it without dose modification in kidney disease. However, for immunocompetent individuals with normal renal clearance, this specific pharmacokinetic advantage does not justify substantially higher overall costs. Consequently, clinicians should reserve premium agents for specific patient subsets where standard options pose genuine safety concerns. By adhering to rational prescribing pathways, medical practitioners protect patient health while preserving economic resources. Thus, valaciclovir remains the preferred first-line agent for the vast majority of acute zoster cases.
The findings from this Japanese economic evaluation offer critical lessons for global health technology assessment authorities. Regulatory agencies increasingly demand robust evidence demonstrating that drug prices reflect measurable patient benefits. In this investigation, amenamevir demonstrated therapeutic non-inferiority rather than superiority. Therefore, health technology assessors recommend price adjustments to align drug reimbursement with actual clinical utility. If manufacturers reduce pricing through competitive negotiation, amenamevir could potentially achieve acceptable cost-effectiveness thresholds in future reassessments.
Furthermore, healthcare payers must continuously evaluate real-world prescription trends to prevent budgetary distortion. When newer branded agents capture significant market share without incremental health benefits, overall healthcare sustainability diminishes. Consequently, policymakers should consider tiered copayments, mandatory step therapy, or prior authorization protocols. These regulatory mechanisms encourage the initial use of cost-effective generic alternatives like valaciclovir before escalating to premium compounds. Ultimately, aligning reimbursement policies with health economics fosters sustainable healthcare delivery. Through transparent pricing reforms and evidence-based clinical guidelines, health authorities can guarantee accessible, high-quality care for all patients suffering from viral infections.
Valaciclovir is significantly more cost-effective because it achieves equivalent clinical outcomes at a much lower acquisition cost. Randomized clinical trials demonstrate that both drugs provide comparable rates of rash healing and pain resolution. However, amenamevir costs considerably more and yields no measurable gain in quality-adjusted life-years. Consequently, valaciclovir remains the economically superior choice for healthcare systems and patients alike, avoiding unnecessary expenditure without compromising clinical safety or therapeutic success.
Valaciclovir is a prodrug of acyclovir that inhibits viral DNA polymerase following intracellular phosphorylation by viral thymidine kinase. In contrast, amenamevir is a non-nucleoside helicase-primase inhibitor that directly impedes the viral helicase-primase enzyme complex. Because amenamevir does not require activation by viral enzymes, it retains activity against acyclovir-resistant strains. Nevertheless, for typical uncomplicated herpes zoster cases, this unique mechanism provides similar clinical healing compared to standard nucleoside analogues like valaciclovir.
Clinicians primarily consider amenamevir for herpes zoster patients with moderate to severe renal impairment. Unlike valaciclovir, which requires careful dosage reduction to prevent neurotoxicity and acute kidney injury, amenamevir is metabolized and eliminated through non-renal pathways. Furthermore, its once-daily dosing schedule may enhance treatment adherence in elderly individuals taking multiple medications. However, because amenamevir carries a substantial cost premium, physicians should reserve it for specific individuals with significant renal dysfunction.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A health economic evaluation in Japan reveals that amenamevir is not cost-effective compared with valaciclovir for treating herpes zoster. Despite achieving similar clinical efficacy, amenamevir substantially increases drug expenditures, highlighting the critical role of valaciclovir in value-based viral care.
Today

The GESS-AEEM consensus establishes a clear clinical implementation framework for testosterone therapy in postmenopausal women with hypoactive sexual desire disorder, focusing on transdermal dosing, precise laboratory monitoring, and safety communication.
Today
A landmark case reveals transcatheter closure of an atrial septal occluder erosion presenting with hemolysis two decades after implantation. This report highlights the longest documented latency for device erosion, emphasizing multimodality imaging, minimally invasive fistula repair, and lifelong patient surveillance.
Today
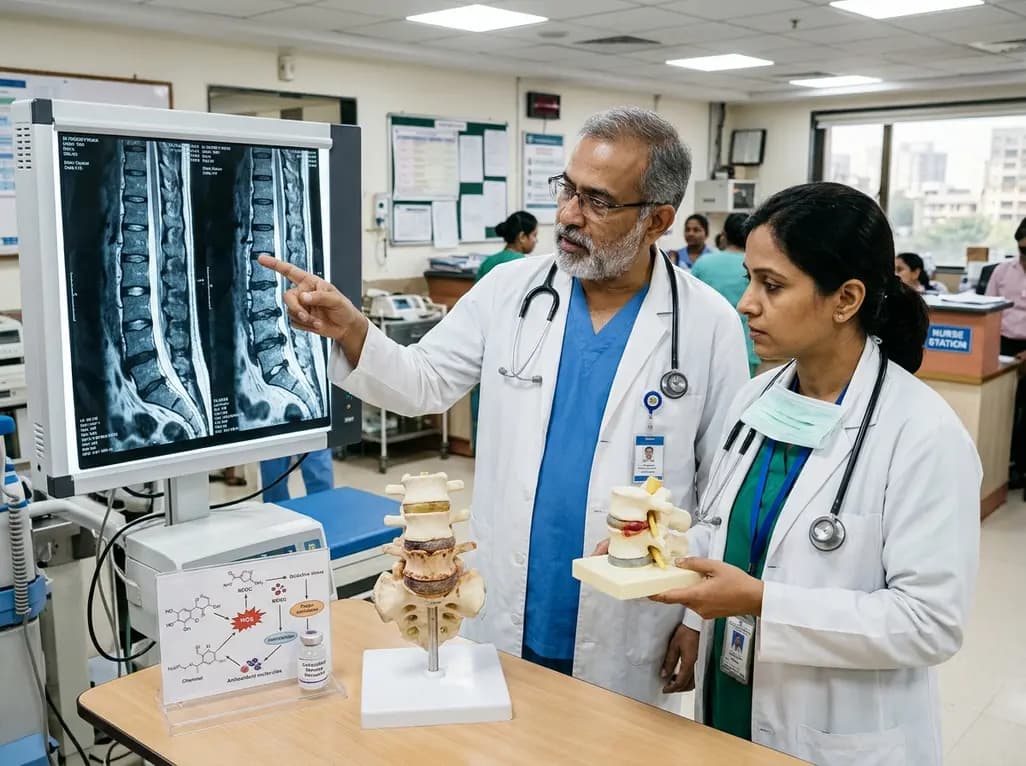
Intervertebral disc degeneration is a primary driver of chronic low back pain. Emerging evidence highlights reactive oxygen species and redox imbalance as central mechanisms. Targeted antioxidant strategies and biomaterial delivery systems offer promising disease-modifying therapies for spine health.
Today

A multicenter cohort study reveals that the 30-minute C-peptide response during OGTT independently predicts cystic fibrosis-related diabetes in patients with normal glucose tolerance, offering an early risk-stratification biomarker.
Today
