

Loading, please wait...
Loading, please wait...
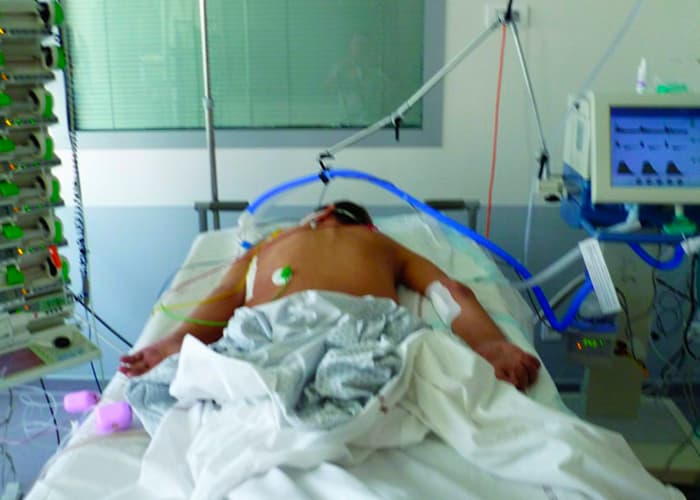
The CLASSIC trial tested whether restricting intravenous fluid administration after initial resuscitation would improve outcomes in adults with septic shock. More than 1,500 patients were randomised to a restrictive-fluid strategy or standard intravenous fluid therapy after receiving at least 1 litre of fluid. The restrictive group received substantially less fluid during the ICU stay, yet 90-day mortality was virtually identical between the strategies. Serious adverse events and days alive without life support were also similar. The trial is important because it challenges the assumption that simply reducing fluid volume will automatically improve survival in septic shock. At the same time, it demonstrates that clinicians can often achieve similar outcomes with much less fluid when unnecessary boluses are avoided. The practical message is therefore one of stewardship rather than blanket restriction. Fluid should be given when a patient is likely to benefit, with repeated assessment of perfusion, fluid responsiveness and the risks of overload. Once shock physiology changes, continued fluid administration can become a source of harm rather than treatment. CLASSIC fits the modern movement toward dynamic, phenotype-based resuscitation in which fluids, vasopressors and other interventions are balanced against the patient's evolving cardiovascular and organ-function profile.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The CLASSIC trial tested whether restricting intravenous fluid administration after initial resuscitation would improve outcomes in adults with septic shock. More than 1,500 patients were randomised to a restrictive-fluid strategy or standard intravenous fluid therapy after receiving at least 1 litre of fluid. The restrictive group received substantially less fluid during the ICU stay, yet 90-day mortality was virtually identical between the strategies. Serious adverse events and days alive without life support were also similar. The trial is important because it challenges the assumption that simply reducing fluid volume will automatically improve survival in septic shock. At the same time, it demonstrates that clinicians can often achieve similar outcomes with much less fluid when unnecessary boluses are avoided. The practical message is therefore one of stewardship rather than blanket restriction. Fluid should be given when a patient is likely to benefit, with repeated assessment of perfusion, fluid responsiveness and the risks of overload. Once shock physiology changes, continued fluid administration can become a source of harm rather than treatment. CLASSIC fits the modern movement toward dynamic, phenotype-based resuscitation in which fluids, vasopressors and other interventions are balanced against the patient's evolving cardiovascular and organ-function profile.
4 weeks back
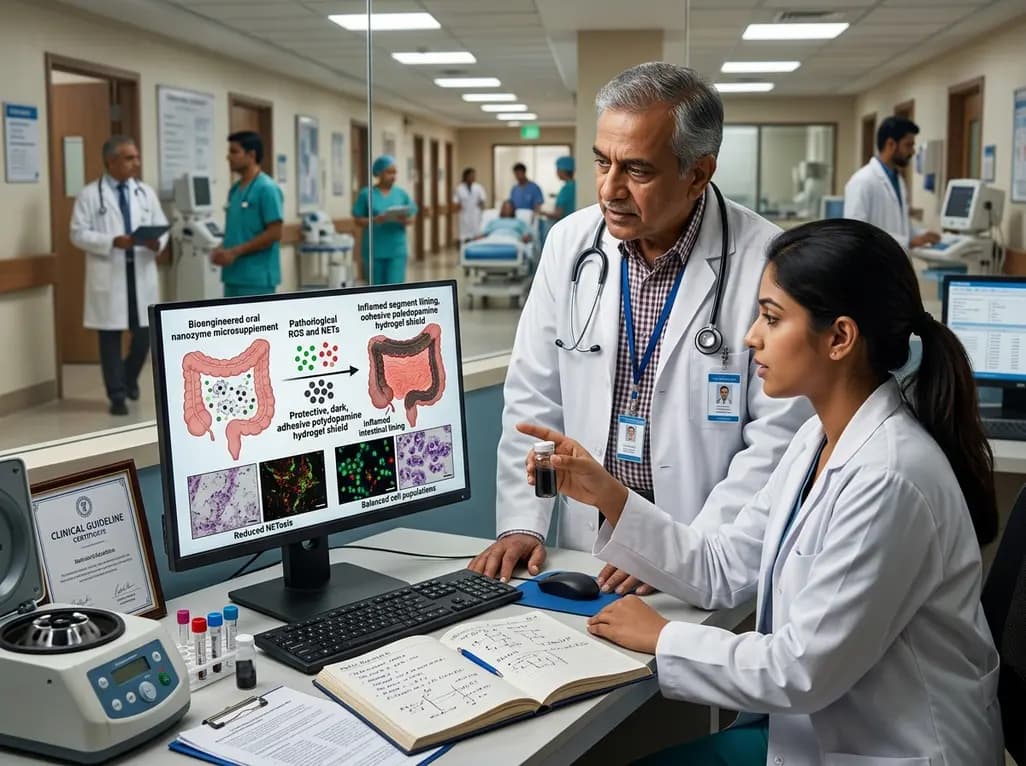
A bioengineered oral nanozyme microsupplement converts pathological ROS into a protective polydopamine hydrogel shield. By curbing neutrophil extracellular traps and balancing T cells, this platform outperforms standard 5-ASA in preclinical colitis models, opening new paths for sustained remission.
4 days back

Recent research reveals that downregulating YAP1/TAZ-TEAD via Hippo signaling triggers spontaneous human trophoblast syncytialization in 3D cultures, illuminating placental biology and preeclampsia.
4 weeks back

Abdominal aortic aneurysm rupture remains a catastrophic vascular emergency. Groundbreaking research reveals that USP53 accelerates aneurysm progression by reprogramming smooth muscle cell metabolism toward aerobic glycolysis, highlighting a promising target beyond conventional diameter-based surveillance.
5 days back
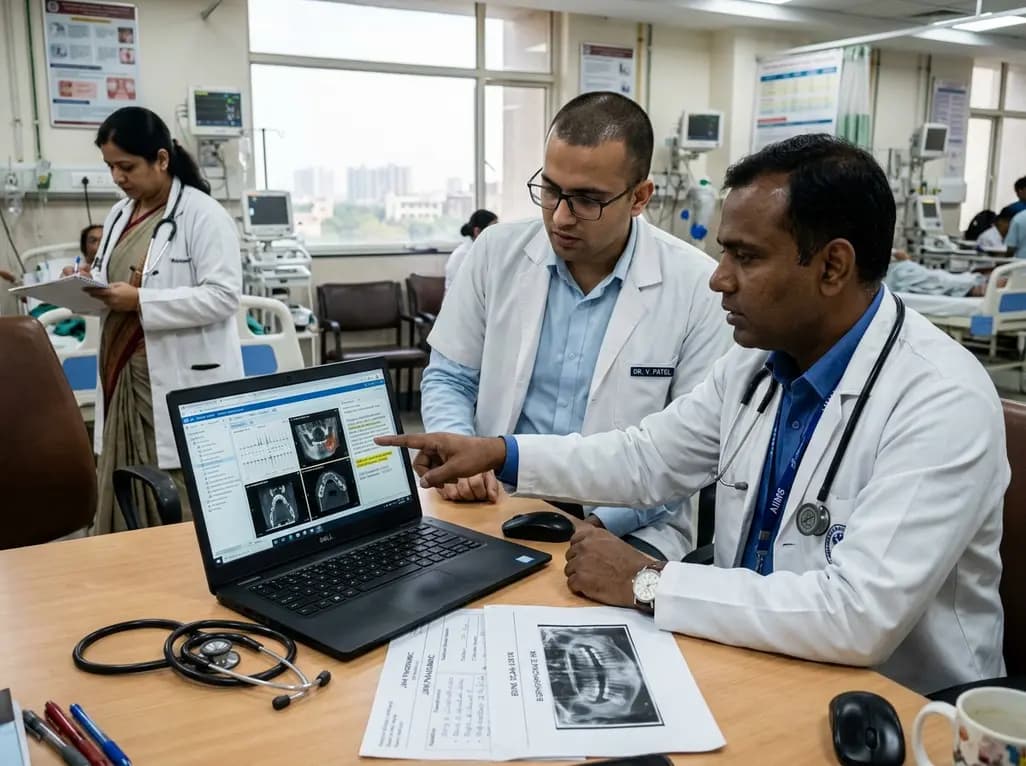
A breakthrough study leverages natural language processing to accurately identify incident medication-related osteonecrosis of the jaw and track antiresorptive drug holidays from clinical narratives in electronic health records, advancing osteoporosis pharmacovigilance and dental safety.
5 days back

Recent research defines ferro-aging as a conserved iron-lipid axis driving organ decline across primates. Age-related iron dyshomeostasis stimulates ACSL4-mediated lipid peroxidation, promoting cellular senescence. Notably, vitamin C directly inhibits ACSL4, suppressing phospholipid oxidation and multi-organ decay.
5 days back
