

Loading, please wait...
Loading, please wait...

Posttraumatic stress disorder represents a severe clinical challenge across healthcare systems globally. Consequently, psychiatric clinicians continuously seek scalable interventions to improve recovery rates. Written Exposure Therapy offers an evidence-based, brief psychological treatment that targets traumatic memories. However, many individuals continue experiencing distressing residual symptoms following standard care.
Standard trauma-focused psychotherapies, such as prolonged exposure and cognitive processing therapy, require extensive clinical time and substantial emotional effort. Consequently, many patients discontinue therapy before completing their protocols. Written Exposure Therapy addresses this challenge directly. Specifically, the manualized protocol delivers five streamlined sessions of thirty minutes each. Patients write detailed personal narratives concerning their primary traumatic events without prolonged verbal exchanges. Furthermore, clinicians provide structured guidance and psychoeducation while remaining nonintrusive during the writing process. This focused exposure promotes fear extinction and cognitive reappraisal within a safe environment. Clinical trials repeatedly demonstrate that this brief approach achieves symptom reductions comparable to longer modalities. In addition, treatment completion rates remain remarkably high because patients encounter fewer logistical barriers. As a result, healthcare systems increasingly implement this protocol in busy outpatient environments. However, a significant subset of treated individuals continues to meet diagnostic criteria after therapy concludes. Therefore, clinician researchers continuously search for synergistic biological strategies to boost clinical recovery rates. Thus, exploring neurostimulation adjunctive therapies represents a logical step forward in translational psychiatry. Furthermore, noninvasive neuromodulation techniques may potentially augment these structured psychological mechanisms.
Neuroimaging studies reveal that posttraumatic stress disorder involves altered functioning across frontolimbic neural circuits. Specifically, patients display amygdala hyperreactivity coupled with hypoactivity in the dorsolateral prefrontal cortex. This prefrontal deficit impairs cognitive top-down regulation and hinders normal fear extinction learning. Consequently, researchers proposed that noninvasive brain stimulation could restore prefrontal control over hyperactive emotional centers. Transcranial direct current stimulation delivers low-intensity electrical currents through scalp electrodes to modulate cortical excitability. Furthermore, anodal stimulation targeting the left dorsolateral prefrontal cortex enhances synaptic plasticity and improves working memory. Preliminary trials indicated that this safe neuromodulatory technique could alleviate hyperarousal and intrusive memories. Therefore, scientists theorized that applying electrical stimulation during psychological exposure would facilitate neural reorganization. Specifically, activating prefrontal pathways during narrative trauma recall might accelerate extinction mechanisms. In addition, the noninvasive device provides excellent tolerability with minimal patient discomfort. Moreover, clinicians can easily apply portable stimulation devices in outpatient offices alongside behavioral protocols. Because both modalities require modest time commitments, the combined approach presents an appealing framework for modern psychiatric interventions.
The pilot randomized clinical trial enrolled twenty-five individuals diagnosed with posttraumatic stress disorder. Investigators randomly allocated participants into two parallel arms: active electrical stimulation or sham stimulation. Furthermore, every patient completed five standardized sessions of Written Exposure Therapy across consecutive weeks. During each treatment session, clinicians positioned electrodes over the dorsolateral prefrontal cortex to deliver electrical currents. In the active stimulation group, participants received continuous low-level current to increase cortical excitability during narrative writing. Conversely, the sham group received brief initial current that simulated tingling sensations without producing lasting neuroplastic alterations. Clinicians carefully monitored participants for adverse effects, including scalp irritation or transient headaches. In addition, blinded evaluators assessed symptom trajectories using rigorous psychometric tools. Specifically, they utilized the Clinician-Administered PTSD Scale for DSM-5 and the self-reported PTSD Checklist for DSM-5. Follow-up evaluations occurred at one month post-treatment to determine long-term therapeutic durability. Consequently, the pilot trial successfully maintained high protocol adherence across both treatment cohorts. Furthermore, participants expressed strong satisfaction with the combined schedule, confirming the practical feasibility of conducting complex neuromodulation trials in clinical trauma populations.
The primary analysis revealed no statistically significant differences between active stimulation and sham stimulation at the one-month follow-up. Specifically, clinician-rated and self-reported trauma symptom measures yielded comparable trajectories across both cohorts. The calculated probability values for between-group differences ranged from p = .573 to p = .619. However, both groups achieved clinically meaningful and statistically significant symptom reductions from baseline to study completion. Notably, participants in both arms experienced substantial relief from intrusive thoughts, avoidance behaviors, and autonomic reactivity. These outcomes confirm that Written Exposure Therapy remains a potent therapeutic tool independently. Nevertheless, adding active electrical current did not confer an extra therapeutic advantage over sham stimulation. Several factors may explain these neutral adjunctive findings. First, the modest sample size of twenty-five participants limited statistical power to detect small effect sizes. Second, the robust standalone efficacy of the written protocol may have created a ceiling effect. Consequently, the potent behavioral intervention might have masked subtle neurostimulation benefits during the pilot evaluation. Moreover, optimal electrode placement, current intensity, and stimulation timing require further systematic optimization. Therefore, clinicians must interpret these results cautiously while acknowledging the undeniable therapeutic power of structured written exposure alone.
These clinical findings offer valuable guidance for mental health professionals managing trauma-related disorders. First, the trial confirms that brief exposure therapy yields substantial clinical benefits even in challenging clinical scenarios. Consequently, busy psychiatric practices can confidently implement five-session written protocols without requiring extensive cognitive restructuring homework. This structure substantially broadens access to care, particularly in resource-constrained medical environments. Second, the lack of added benefit from adjunctive neurostimulation emphasizes that clinicians should not prematurely adopt unproven technology. Although noninvasive brain stimulation holds theoretical promise, routine clinical integration requires robust, definitive evidence from larger multicenter trials. Furthermore, healthcare providers must evaluate cost-effectiveness and equipment availability before investing in novel neurotechnologies. Instead, clinicians should prioritize established, guideline-concordant psychotherapies that demonstrate reproducible clinical outcomes. Meanwhile, researchers must continue refining neuromodulation parameters to determine whether specific patient subgroups might benefit from targeted prefrontal enhancement. Ultimately, thoughtful clinical judgment and adherence to evidence-based practices remain the cornerstone of effective posttraumatic care. In addition, clinicians should focus on strengthening therapeutic alliance and enhancing patient motivation during exposure tasks to maximize long-term recovery.
Written Exposure Therapy differs significantly from traditional trauma-focused treatments because it requires only five brief thirty-minute writing sessions. Unlike prolonged exposure or cognitive processing therapy, it eliminates extensive verbal trauma recounting and between-session homework assignments. Consequently, patients experience substantially lower dropout rates and comparable symptom relief. This concise structure makes the intervention uniquely scalable across busy psychiatric outpatient clinics and resource-limited healthcare facilities.
Researchers investigated transcranial direct current stimulation because patients with posttraumatic stress disorder frequently exhibit hypoactivity in the dorsolateral prefrontal cortex. This prefrontal dysfunction impairs emotional regulation and fear extinction learning. Therefore, scientists theorized that delivering anodal electrical current to this cortical region during trauma writing would enhance neuroplasticity. They hypothesized that boosting prefrontal excitability would accelerate fear extinction and produce greater clinical improvements than therapy alone.
Clinicians should view these findings as confirmation that structured written exposure provides robust therapeutic efficacy on its own. While adjunctive brain stimulation did not outperform sham current, the small sample size may have limited statistical power. Consequently, psychiatrists should rely on proven evidence-based psychotherapeutic protocols rather than routinely adopting adjunctive brain stimulation. Future large-scale trials must clarify whether optimized stimulation parameters can offer meaningful incremental value.
Disclaimer: This content is for informational and educational purposes only and should not be considered as medical advice or used for the guidance of individual patient care. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A pilot randomized clinical trial evaluated Written Exposure Therapy augmented with tDCS targeting the DLPFC for PTSD. While both active and sham groups showed significant symptom reduction at 1 month, no significant group differences emerged, highlighting the robust standalone efficacy of WET.
Today

Health authorities in the Democratic Republic of Congo confirmed the spread of Ebola to North Ubangi province. With cross-border infections and high case counts, healthcare professionals worldwide must review early clinical recognition, differential diagnosis, infection control measures, and isolation protocols.
Today
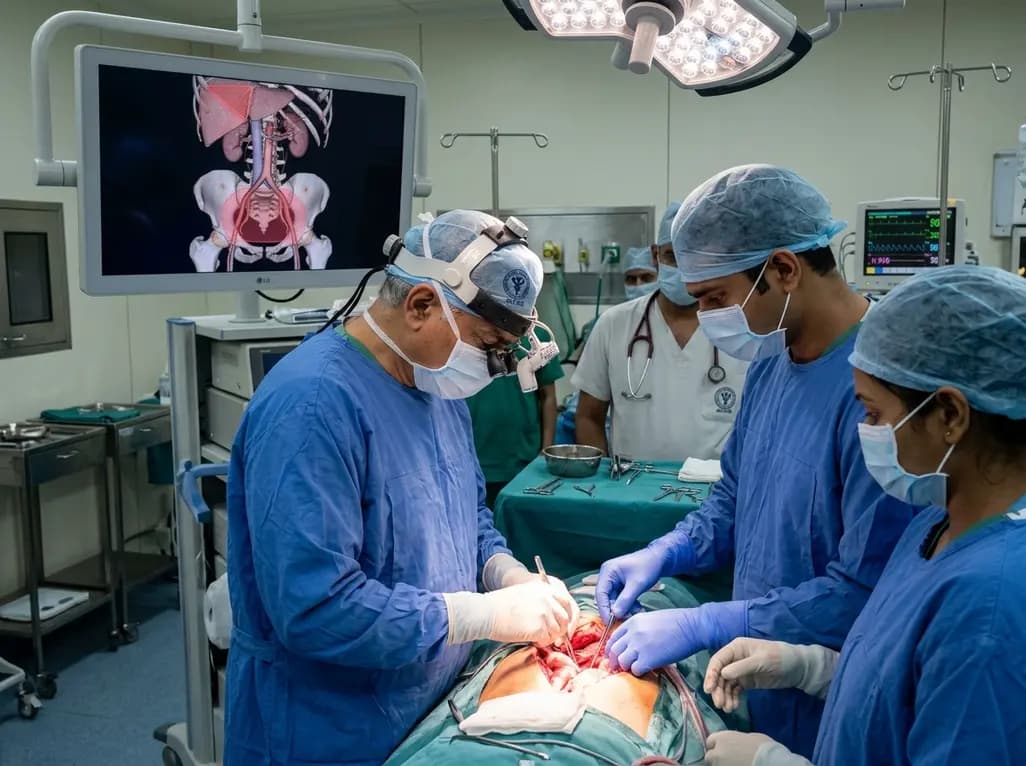
Surgical oncologists at AIIMS Delhi have mapped two critical anatomical landmarks: Ray's Zone in the deep pelvis and Ray's Hepatocaval Triangle near the liver. These predefined hazard boundaries guide dissection, dramatically reduce severe intraoperative bleeding, and preserve vital nerves and visceral organs.
Today

A study reveals that the MYLK c.4079G>A, p.(Gly1360Asp) variant is linked to high-penetrance heritable thoracic aortic disease and early-onset aortic dissection, showing a founder effect in Finnish cohorts. Findings emphasize early cascade screening and vigilant surveillance.
Today

A novel sacrificial-template technique combines FDM polymer 3D printing and micro-arc oxidation to fabricate orientation-controlled porous titanium scaffolds. These bioactive constructs offer tailored stiffness, exceptional multidirectional load resistance, and robust osseointegration for bone defect repair.
Today
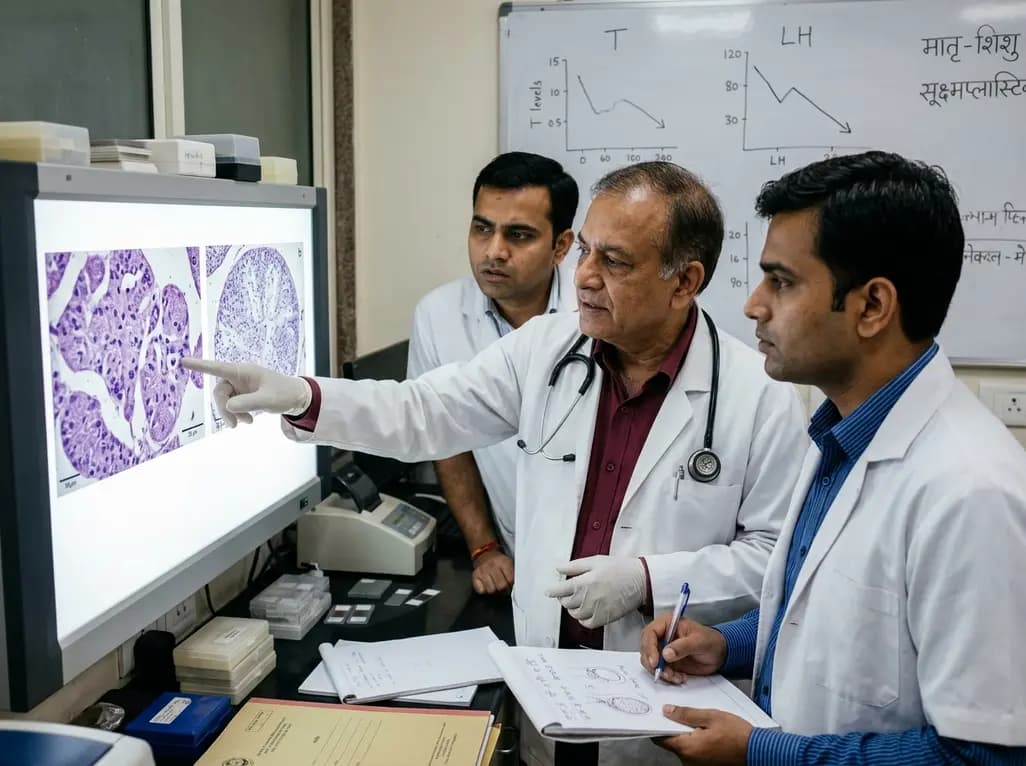
An animal model study reveals that gestational exposure to polystyrene microplastics causes persistent intrauterine growth restriction, testicular hypoplasia, Leydig cell depletion, and an atypical low-testosterone, low-LH endocrine profile in male offspring from birth into adulthood.
Today
