

Loading, please wait...
Loading, please wait...
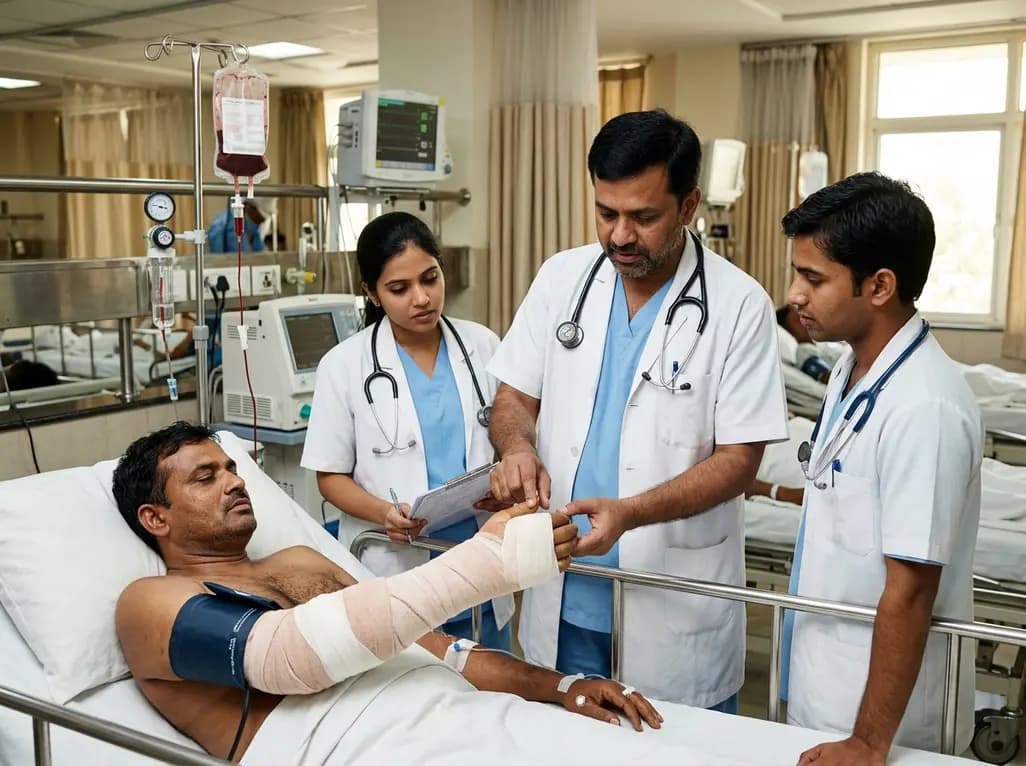
Major surgical interventions such as orthotopic liver transplantation require reliable high-flow vascular access to counteract sudden, massive haemorrhage. Rapid infusion catheters offer excellent flow rates through large-bore peripheral veins. Nevertheless, clinicians face grave hazards when rapid infusion catheter extravasation occurs under pressurized infusion systems. Because surgical drapes conceal the extremities, fluid extravasation can advance unnoticed. Inadvertent interstitial fluid delivery rapidly elevates osteofascial pressures, provoking severe tissue ischemia. Consequently, perioperative teams must maintain rigorous vigilance and recognize subtle warning signs to avert irreversible neurovascular damage.
Rapid infusion devices deliver warmed blood products and crystalloids under substantial pneumatic pressure. When a vascular injury occurs, fluid escapes the venous lumen directly into surrounding musculofascial beds. The unyielding investing fascia of the limb cannot expand to accommodate this acute volume influx. Therefore, intracompartmental pressures rise exponentially within a short timeframe. As pressures exceed normal capillary perfusion thresholds, microvascular collapse ensues. Cellular anoxia and secondary tissue edema subsequently create a destructive vicious cycle. In addition, rapid extravasation of red cells and potassium-rich fluids induces significant local chemical irritation and systemic electrolyte shifts. Untreated compartment hypertension swiftly progresses to muscle necrosis, nerve infarction, and limb loss. Hence, mechanical disruption of fragile peripheral veins under rapid flow presents extreme perioperative hazards.
Recognizing compartment syndrome in anesthetized patients remains notoriously difficult because classic neurological complaints like intense pain and paresthesia disappear under general anaesthesia. Instead, anaesthesiologists and surgeons must rely on secondary physiological clues and physical inspection. An abrupt, unexplained surge in serum potassium or lactate during massive transfusion can signal localized tissue breakdown. Furthermore, infusion pump resistance or unexpected sluggishness during fluid delivery warrants immediate inspection. When clinicians inspect the draped limb, physical examination reveals an extremely tense, non-compressible compartment. The distal extremity frequently turns cool, pale, or dusky. Meanwhile, peripheral pulses such as the radial or ulnar artery become impalpable. Cutaneous bullae, epidermolysis, and extensive ecchymosis around the insertion site further confirm acute subcutaneous extravasation. Therefore, clinicians must constantly correlate systemic biochemical anomalies with vascular access patency.
When clinicians identify acute compartment syndrome, immediate cessation of the offending infusion represents the mandatory first action. Anesthetic teams must switch fluid administration to unaffected central or peripheral lines without delay. Subsequently, emergent surgical decompression remains the definitive therapy to restore microvascular perfusion. Surgeons perform comprehensive fasciotomies of the affected arm compartments in parallel with the ongoing procedure. In upper-arm involvement, longitudinal release of the anterior muscular compartment promptly decompresses the brachial neurovascular bundle and deep tissue structures. Immediate return of distal arterial pulses and tissue pinkness validates successful mechanical release. After adequate decompression, surgical teams leave fascial edges open and apply sterile negative pressure dressings. Consequently, rapid coordinated intervention between transplant surgeons and anaesthesiologists directly averts permanent contractures or amputation.
A critical lesson from complex vascular access cases involves the management of initial cannulation failure. During line insertion, persistent resistance to guidewire advancement indicates mechanical obstruction, tortuosity, or intimal dissection. Forcing equipment through such resistance inevitably creates a venous laceration. If clinicians immediately attempt re-cannulation at the exact same anatomic site, pressurized fluids find this path of least resistance. Although ultrasound confirmation and uncomplicated saline flush may suggest an intraluminal position, high-pressure pumps force infusate across preexisting vascular wall breaches. Furthermore, subsequent arm positioning, patient movement, and draping easily dislodge large-bore catheters from marginal vessels. Therefore, anaesthesiologists must abandon traumatised venous channels entirely. Instead, selecting alternative peripheral sites or using central venous access protects patients from devastating tissue extravasation.
Operating rooms require strict surveillance protocols whenever high-flow peripheral access devices deliver fluids under pressure. Surgical draping frequently obscures the upper limbs throughout complex abdominal or thoracic procedures. Thus, visual neglect of the infusion site poses a significant threat to patient safety. Teams should maintain direct line of sight to high-flow catheters using transparent drapes whenever feasible. If complete concealment remains unavoidable, the surgical team should implement scheduled physical re-inspections every thirty to sixty minutes. Clinicians should palpate proximal tissues to ensure soft, compressible musculature. Additionally, continuous monitoring of distal limb perfusion with pulse oximetry applied to the ipsilateral fingers provides continuous surveillance. By incorporating standardized access checks into routine surgical time-outs, healthcare professionals ensure early recognition and eliminate avoidable limb-threatening complications.
Because anesthetized patients cannot verbalize ischemic pain, clinicians must detect physical and biochemical indicators. Primary physical signs include an intensely tense, woody muscular compartment, absent distal arterial pulses, and a cold, dusky extremity. Cutaneous blistering and ecchymosis often surround the insertion site. Concurrently, systemic laboratory shifts, such as unexplained increases in serum potassium and lactate levels, provide critical early warnings of occult tissue breakdown.
Guidewire resistance typically signals mechanical obstruction, anatomical tortuosity, or vascular wall perforation. Attempting forceful dilation or subsequent recannulation in the same traumatised vein substantially elevates the risk of transmural laceration. When pressurized rapid infusion devices subsequently connect to the device, fluids escape through the disrupted vessel wall into closed osteofascial compartments. Therefore, clinicians must abandon traumatised veins and seek alternative access sites.
Operating room teams should position transparent surgical drapes over high-flow peripheral access sites whenever feasible. If full draping covers the extremities, the team must institute mandatory palpation checks at predefined thirty-minute intervals to verify soft compartments. In addition, attaching a continuous pulse oximeter sensor to the ipsilateral hand offers uninterrupted surveillance of pulsatile distal perfusion during high-pressure transfusions.
Disclaimer: This content is for informational and educational purposes only and should not be considered as professional medical advice. Always consult a qualified healthcare provider for diagnosis and treatment decisions. Refer to the latest local and national guidelines for clinical practice.
References
Weinberg L et al. Upper-Limb Compartment Syndrome Following Rapid Infusion Catheter Extravasation During Orthotopic Liver Transplantation: A Case Report. Cureus. 2026 Sep undefined. doi: 10.7759/cureus.116959. PMID: 42801152.
Park C, Kim H. Acute compartment syndrome due to extravasation of peripheral intravenous blood transfusion. Saudi J Anaesth. 2020;14(2):221-223.
Barber CM, Fahrenkopf MP, Adams NS, Kelpin JP, Krebiehl JR. Compartment Syndrome of the Hand Secondary to Intravenous Extravasation. Eplasty. 2018;18:ic17.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





During liver transplantation, pressurized transfusions provide vital resuscitation. However, rapid infusion catheter extravasation can lead to severe upper-limb compartment syndrome. This report highlights key clinical indicators, surgical decompression, and vigilant access protocols to prevent tissue ischemia.
Today

Ceftriaxone therapy can lead to biliary sludge and gallstone formation due to calcium-ceftriaxone precipitation. A recent cohort study shows that the noninvasive Fibrosis-4 (FIB-4) index, alongside treatment duration, independently predicts lithogenesis, enabling proactive risk stratification.
Today

A multiparametric MRI approach combining quantitative T2 shading, apparent diffusion coefficient (ADC) measurements, and morphological signs provides superior diagnostic accuracy over subjective evaluation to differentiate ovarian endometriomas from benign hemorrhagic cysts.
Today
A landmark case report reveals a donor heart beating for a century in a 63-year-old recipient, challenging conventional age limits in cardiac transplantation and offering critical lessons on organ longevity, donor selection, and long-term graft survival.
Today
CT-guided pulsed radiofrequency ablation of the obturator nerve delivers durable pain relief up to 12 months in mild-to-moderate hip osteoarthritis, while offering a safe short-term palliative bridge for severe grade 4 disease without procedural complications.
Today

New research reveals that M1 macrophage-derived exosomes aggravate diabetic nephropathy by transferring WTAP to stabilize S1PR2 mRNA. Silencing WTAP in these vesicles attenuates endothelial injury and renal fibrosis, pointing toward innovative nanomedicine therapies.
Yesterday
