

Loading, please wait...
Loading, please wait...
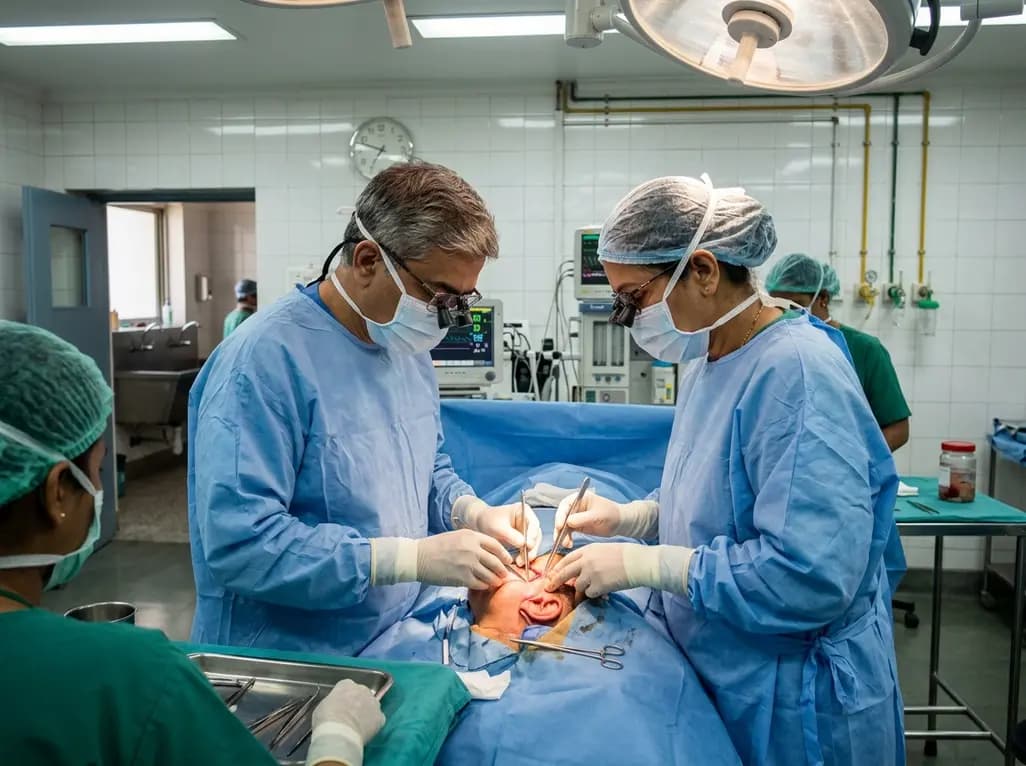
Surgical decision-making for salivary gland malignancies requires balancing complete disease clearance with long-term functional preservation. Traditionally, total parotidectomy was favored to ensure complete microscopic disease clearance and removal of intraparotid lymph nodes. However, growing evidence indicates that less-than-total parotidectomy provides comparable oncologic control for localized low-grade tumors. When planning parotid cancer surgery, head and neck surgeons must carefully evaluate tumor extent, histological grade, and potential operative morbidity to select the most appropriate surgical strategy for each individual patient.
Parotid gland malignancies account for the majority of primary salivary gland tumors and present unique anatomical challenges due to their close proximity to the facial nerve. Low-grade parotid cancers, including low-grade mucoepidermoid carcinoma and acinic cell carcinoma, generally exhibit indolent biological growth and low regional metastatic potential. Consequently, the necessity of radical total gland removal for early-stage (T1-2) disease is increasingly questioned by surgical oncologists. Extended resections often cause significant surgical morbidity, such as facial nerve paralysis, Frey syndrome, soft tissue depression, and facial asymmetry. Modern surgical oncology aims to minimize unnecessary tissue removal while maintaining clear surgical margins. Understanding the distinct biological behavior of low-grade tumors allows surgeons to tailor operative extent safely. Thus, re-evaluating traditional radical paradigms helps optimize patient outcomes without compromising cancer control in early-stage disease.
Surgical management of parotid malignancies includes total parotidectomy and conservative less-than-total parotidectomy. Total parotidectomy involves complete removal of both superficial and deep gland tissue, requiring extensive facial nerve dissection. Proponents argue that total removal ensures maximum local disease clearance and eliminates occult intraparotid lymph nodes. Conversely, less-than-total parotidectomy encompasses superficial parotidectomy or partial resections, removing the primary tumor with an adequate healthy margin while preserving normal gland tissue. Limited approaches significantly reduce facial nerve manipulation and overall operative trauma. In early-stage cases, conservative surgery offers shorter operative times, lower complication rates, and improved cosmetic outcomes. However, surgeons must ensure that limited resections achieve negative microscopic margins without tumor spillage. Procedure selection depends on preoperative imaging, tumor size, anatomical location within the gland, and fine-needle biopsy results.
Evaluating long-term survival is critical when considering limited resection for malignant salivary gland tumors. Systematic reviews and meta-analyses comparing less-than-total parotidectomy with total parotidectomy in T1-2 low-grade parotid cancers demonstrate equivalent oncologic safety. Pooled clinical data show no statistically significant difference in overall survival between conservative resection and total gland removal. Similarly, recurrence-free survival rates remain comparable across both surgical approaches, confirming that limited resection does not heighten local recurrence risk. Furthermore, minimal statistical heterogeneity reinforces these clinical findings across published cohorts. Because low-grade early-stage tumors confined to the superficial lobe rarely involve deep tissue or regional lymph nodes, aggressive total resection yields no additional survival benefit. Consequently, conservative surgery offers an oncologically sound alternative for appropriately selected patients, supporting a shift toward function-sparing operations.
Functional preservation remains a major clinical advantage of less-than-total parotidectomy. Extensive facial nerve dissection during total gland extirpation carries a substantial risk of transient or permanent facial nerve weakness. Limited resections reduce nerve manipulation, resulting in significantly lower rates of postoperative neuropraxia and faster functional recovery. Additionally, preserving uninvolved parotid parenchyma maintains normal salivary secretion and minimizes post-operative xerostomia. Conservative techniques also significantly decrease the incidence of Frey syndrome, a distressing condition caused by aberrant nerve regeneration. Furthermore, maintaining gland volume avoids deep facial contour defects, leading to superior cosmetic outcomes. Preserving facial nerve function, salivary capacity, and cosmetic integrity directly enhances postoperative quality of life. Therefore, function-sparing surgery should be prioritized when oncologic control is fully maintained.
Despite encouraging outcomes, current evidence supporting conservative parotidectomy relies primarily on retrospective cohort studies. Retrospective data introduce potential selection bias, as smaller exophytic tumors are more frequently chosen for limited resections. Furthermore, variable definitions of partial parotidectomy and unstandardized functional outcome measures limit definitive conclusions. Surgical decision-making must therefore remain individualized and cautious. Surgeons should perform high-resolution imaging and cytological evaluation to confirm tumor location and grade before surgery. Obtaining negative microscopic margins remains mandatory regardless of surgical extent. If intraoperative findings demonstrate unexpected deep extension, close margins, or high-grade features, surgeons must adapt their plan to a broader resection. Multidisciplinary discussion ensures optimal treatment tailored to individual clinical characteristics and tumor risk profiles.
Current research indicates that less-than-total parotidectomy offers overall survival and recurrence-free survival outcomes similar to total parotidectomy in selected early-stage T1-2 low-grade tumors. However, surgical candidates must present with lesions confined to the superficial lobe without deep lobe extension or nodal involvement. Surgeons must carefully assess individual tumor characteristics, ensure clear surgical margins, and consider patient risk factors before selecting a conservative surgical approach in daily clinical practice.
Conservative surgical techniques significantly reduce operative trauma to surrounding facial structures. Consequently, patients undergoing less-than-total resection experience lower rates of transient or permanent facial nerve weakness, reduced incidence of Frey syndrome, and better preservation of salivary function. Furthermore, these conservative approaches usually minimize post-operative cosmetic deformities along the facial contour, leading to improved overall quality of life and higher long-term patient satisfaction compared to total gland removal.
Achieving negative microscopic margins is the primary determinant of local disease control in salivary gland malignancies. Even when performing conservative operations, surgeons must prioritize complete tumor extirpation over functional preservation if margins are compromised. Positive or close margins significantly increase local recurrence risk, often requiring adjuvant radiation therapy or revision surgery. Therefore, intraoperative frozen section analysis and precise surgical technique remain mandatory during limited parotid resections.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice. Healthcare professionals should rely on clinical judgment and individualized patient assessment when making treatment decisions. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A systematic review evaluating total versus less-than-total parotidectomy for T1-2 low-grade parotid malignancies shows comparable survival and recurrence outcomes while offering potential functional advantages.
2 months ago

A breakthrough LC-MS/MS technique provides rapid, green quantification of polar pesticide residues like glyphosate across 13 foods. Dietary risk assessment shows negligible toxicity, while discarding initial tea infusions removes up to 99.2% of chemical traces.
Today

Delhi is undergoing a major healthcare overhaul with enhanced Ayushman Bharat insurance up to ₹10 lakh, increased MBBS and PG medical training seats, expanded primary network mandirs, new tertiary neuro-ICUs, and public-private reproductive technology initiatives to build a resilient, preventative healthcare model.
Today

Aon forecasts India's healthcare inflation will ease to 10.1% in 2027 from 11.5% in 2026. Despite moderation, healthcare expenses continue to outpace general inflation, propelled by non-communicable diseases, advanced medical therapeutics, and expanding utilization patterns across diverse patient populations.
Today

Non-union fractures occur in 2-5% of cases, causing significant disability and cost. Conservative modalities such as LIPUS, PEMF, and focused ESWT offer non-surgical healing options for defects up to 5-10 mm when adequate mechanical stability exists without infection.
Yesterday

A crossover trial reveals that acute resistance exercise at 80% 1RM markedly reduces circulating asprosin, enhances insulin sensitivity, and blunts appetite in women with and without obesity, establishing high-intensity lifting as an effective non-pharmacological metabolic therapy.
Today
