

Loading, please wait...
Loading, please wait...
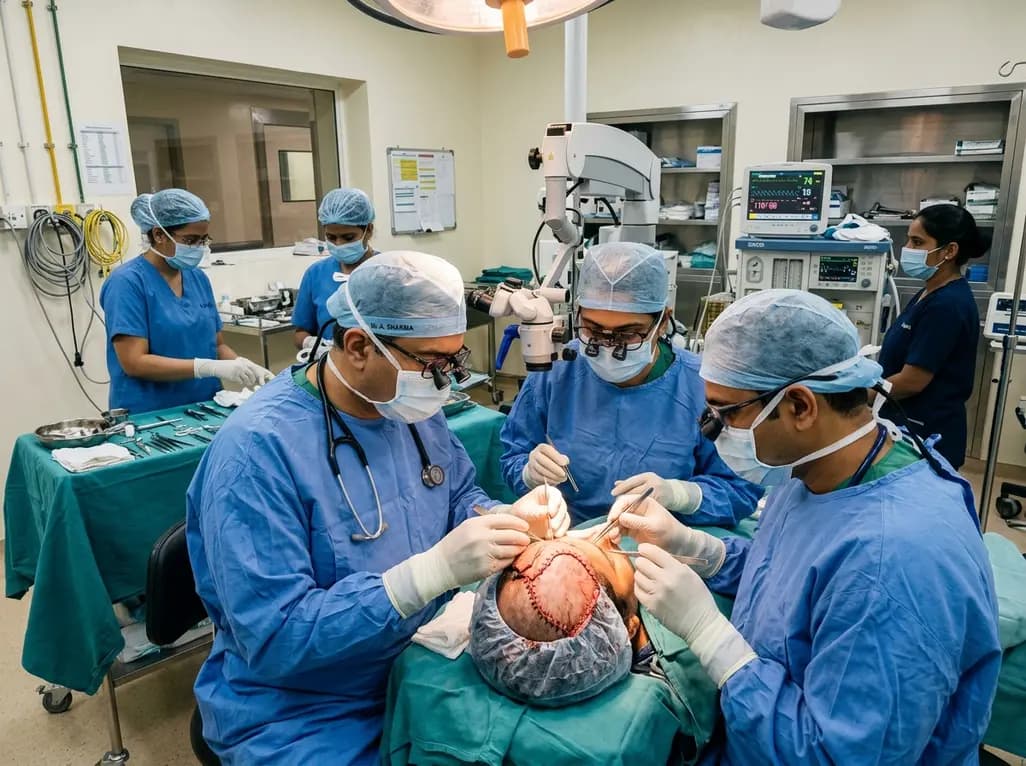
Surgical resection of aggressive cutaneous malignancies on the scalp frequently results in extensive full-thickness soft tissue defects. Reconstructing these cranial defects demands pliable tissue that resists radiation injury and provides acceptable cosmetic contours without excessive bulk. In this setting, the thin TDAP free flap has emerged as a reliable, versatile solution for oncologic scalp resurfacing. Traditional free flaps, such as the conventional latissimus dorsi musculocutaneous flap, frequently cause prominent contour deformities and noticeable donor site morbidity. In contrast, perforator-based free flaps allow surgeons to harvest thin cutaneous paddles while preserving underlying latissimus dorsi muscle architecture. Consequently, reconstructive surgeons can achieve durable soft-tissue coverage that matches the convex curvature of the human cranium. Clinical interest in perforator flap designs has surged among surgical oncologists and head and neck microsurgeons. Recent clinical evidence demonstrates that microvascular scalp reconstruction can combine high oncologic radicality with prompt aesthetic rehabilitation.
Extensive scalp defects involving the calvarium present distinct anatomical challenges because the scalp has minimal native skin laxity. Local advancement flaps cannot bridge large defects without excessive tension or extensive secondary alopecia. Therefore, surgeons must rely on free tissue transfer to ensure tension-free coverage over exposed periosteum or bare bone. While the anterolateral thigh flap provides ample tissue volume, it often proves excessively bulky in non-obese individuals unless surgeons perform secondary thinning procedures. Similarly, radial forearm free flaps offer adequate pliability, but harvest creates a conspicuous donor defect requiring split-thickness skin grafting. Perforator flaps from the back overcome these challenges by combining generous surface area with a concealed donor site. Furthermore, careful intraoperative thinning during elevation produces a supple skin paddle that conforms smoothly across the calvarial vault. Thus, surgical teams achieve stable wound closure and prevent devastating complications like hardware exposure, calvarial osteomyelitis, or persistent cerebrospinal fluid leaks.
Surgeons execute flap elevation through meticulous identification of musculocutaneous or septocutaneous perforators originating from the descending branch of the thoracodorsal vessels. Preoperative color Doppler ultrasonography assists in mapping reliable cutaneous perforators along the anterior border of the latissimus dorsi muscle. During surgical dissection, operators preserve the integrity of the thoracodorsal nerve and the bulk of the latissimus dorsi muscle, which protects shoulder adduction and internal rotation. The thin TDAP free flap can yield a substantial skin paddle exceeding ninety square centimeters alongside a generous vascular pedicle measuring approximately ten centimeters. This lengthy pedicle easily reaches recipient vessels in the head and neck without demanding interpositional vein grafts. For scalp resurfacing, surgeons commonly select the superficial temporal artery and vein as primary recipient targets. In addition, end-to-end microvascular anastomosis under high-magnification microscopes secures stable arterial inflow and unimpeded venous outflow, minimizing operative times and postoperative microvascular crises.
A recent cohort study evaluated fourteen consecutive patients undergoing scalp reconstruction after wide local excision of aggressive malignancies, including squamous cell carcinoma, basal cell carcinoma, basosquamous carcinoma, and cutaneous angiosarcoma. TDAP elevation was successfully completed in 87.5% of surgical attempts. However, in two patients, exploratory dissection revealed no dependable cutaneous perforators, requiring prompt conversion to a standard latissimus dorsi muscle flap. This surgical fallback option represents a critical safety advantage of the thoracodorsal donor territory. If anatomical perforator variations compromise cutaneous harvest, the surgeon immediately elevates the underlying muscle without repositioning the patient or prepping a second operative site. Operative efficiency remained excellent, with an average operative duration of 134 minutes encompassing tumor extirpation, flap harvest, and microvascular anastomoses. Consequently, elderly patients with significant medical comorbidities benefit from reduced general anesthetic exposure and swift hemodynamic stabilization.
Microvascular flap survival depends on rigorous postoperative clinical monitoring and timely management of vascular compromise. In the reported cohort, every transferred flap survived completely to discharge. One flap suffered an acute venous thrombosis, but urgent surgical re-exploration and thrombectomy successfully salvaged the reconstruction. Another flap exhibited transient venous congestion that resolved spontaneously without secondary interventions. Furthermore, preserving the latissimus dorsi muscle fibers dramatically mitigates long-term donor site functional deficits. Patients retain excellent active shoulder motion and return rapidly to daily functional routines. Primary closure of the back harvest site remains achievable in the vast majority of cases, leaving a well-hidden linear scar along the posterior axillary line. Seroma formation, which historically plagued conventional latissimus dorsi muscle harvests, occurs far less frequently because surgeons minimize intramuscular dead space. Consequently, this refined microvascular approach optimizes both systemic safety and long-term functional autonomy.
Managing malignant scalp neoplasms requires balanced coordination between complete oncologic margins and prompt functional reconstruction. Aggressive skin cancers frequently demand adjuvant radiation therapy, which can compromise poorly vascularized graft beds and fragile local flaps. Perforator free flaps deliver robust, autologous microvascular perfusion that tolerates high-dose postoperative radiotherapy without tissue breakdown. In long-term surveillance across seventeen months, patients demonstrated durable calvarial resurfacing with natural aesthetic contours. Only one individual diagnosed with angiosarcoma experienced distant systemic metastasis, whereas none developed local recurrence beneath the reconstructive paddle. Therefore, reconstructive microsurgeons should incorporate this procedure into standard surgical algorithms for extensive calvarial defects. By combining low donor morbidity, high surgical adaptability, and expedited operative efficiency, this perforator flap establishes an invaluable benchmark in modern head and neck onco-reconstruction.
Surgeons localize thoracodorsal artery perforators along the anterior border of the latissimus dorsi muscle. Preoperative Doppler ultrasonography maps cutaneous vessels usually located eight to twelve centimeters below the axillary apex and two to three centimeters posterior to the muscular margin. Intraoperative direct visualization ensures safe pedicle dissection through muscular fibers while preserving thoracodorsal nerve branches, maintaining robust microvascular flow to the thinned cutaneous paddle.
When surgical exploration reveals inadequate or absent cutaneous perforators, the operative team executes an immediate conversion to a conventional latissimus dorsi muscle flap. Because both flaps share the identical vascular axis, surgeons accomplish this transition without repositioning the patient or prepping an alternate donor site. The harvested muscle is then transferred and resurfaced with a split-thickness skin graft, ensuring reliable reconstructive completion.
The superficial temporal artery and vein provide outstanding caliber match and proximity for scalp defects, avoiding extensive neck dissection. Their superficial location immediately anterior to the tragus allows rapid vascular preparation and direct microvascular end-to-end anastomosis. Utilizing these vessels shortens total operative duration, minimizes recipient site morbidity, and prevents hemodynamic compromise associated with deeper cervical vessel dissections.
Disclaimer: This content is for informational and educational purposes only and should not be considered as professional medical advice. Always consult a qualified healthcare provider for specific clinical queries. Refer to the latest local and national guidelines for clinical practice.
References
Kang D et al. Thin Thoracodorsal Artery Perforator Free Flap for Scalp Resurfacing After Malignant Skin Tumor Excision. Head Neck. 2026 Sep 27. doi: 10.1002/hed.70490. PMID: 42802094.
Lee SH, Lee KT. Reconstruction of extensive scalp defects of oncologic origin using thoracodorsal artery perforator free flaps. Arch Hand Microsurg. 2023;28(4):255-263. doi: 10.12790/ahm.23.0025.
Sood J, et al. Free Thoracodorsal Artery Perforator Flap for Head and Neck Reconstruction: An Indian Experience. Indian J Plast Surg. 2021;54(3):305-312. doi: 10.1055/s-0041-1736270.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A retrospective study highlights the thin thoracodorsal artery perforator (TDAP) free flap as an efficient, reliable option for scalp resurfacing after malignant skin tumor excision. The approach achieves high flap survival, excellent contour restoration, and minimal donor morbidity.
Today

A recent qualitative synthesis highlights how physical labour, dignity preservation, and weight stigma intersect when caring for larger-bodied patients in acute care. Overcoming these challenges requires ergonomic equipment, adequate staffing, flexible workflows, and size-inclusive institutional policies.
Today
Novel preclinical research demonstrates that antisense oligonucleotides targeting essential genes such as DARS1, DYNC1I2, and EIF2S3 selectively induce apoptosis in ovarian and lung cancer cells. Conditional biomarker activation provides a viable strategy to spare normal tissue while overcoming therapy resistance.
Today

This clinical analysis examines heparin-free versus heparin-containing Impella purge solutions in patients receiving concomitant ECMO support (ECPELLA). Evidence suggests anticoagulant-free purges maintain device patency while reducing bleeding risks, offering a viable strategy alongside systemic anticoagulation.
Today

A 10-year Markov state-transition model shows minimally invasive tubular decompression dominates open laminectomy for pure lumbar spinal stenosis, yielding 5.95 vs 5.91 QALYs and saving $4,167 per patient through reduced complications and lower index costs.
Today

A preclinical study demonstrates that naringin-loaded phytosomes significantly enhance oral bioavailability and provide neuroprotective efficacy in diabetic neuropathy by dampening inflammation, reducing oxidative stress, and relieving neuropathic pain.
Today
