

Loading, please wait...
Loading, please wait...

Acute ischemic stroke caused by combined proximal and peripheral lesions represents a complex clinical challenge. Consequently, managing a tandem occlusion stroke requires clinicians to address an internal carotid artery occlusion alongside downstream intracranial obstruction. While proximal middle cerebral artery blockages have received extensive research, concurrent occlusions involving distal cortical branches remain poorly understood. Therefore, a comprehensive stroke registry study provides crucial real-world insights into the clinical presentation, management pathways, and recovery outcomes for these patients.
Tandem cerebrovascular lesions traditionally involve high-grade internal carotid artery occlusion paired with intracranial large vessel occlusions. However, clinicians occasionally encounter simultaneous carotid occlusion and distal middle cerebral artery occlusion in cortical branches. Specifically, these peripheral blockages involve the M3 or M4 anatomical segments. Pathophysiologically, friable atheromatous plaques or arterial dissections often release microemboli that travel distally into branch vessels. In a comprehensive stroke registry evaluating 100 consecutive patients with internal carotid artery occlusion, 28 individuals demonstrated this distal tandem pattern. Thus, distal tandem involvement constitutes a substantial portion of complex stroke presentations. Early identification through rapid computed tomography angiography remains paramount for effective decision-making. In addition, robust collateral flow through the circle of Willis significantly influences ischemic tissue viability. Because leptomeningeal channels provide variable hemodynamic compensation, neurological deficits fluctuate widely among affected individuals. Consequently, neurovascular teams must thoroughly assess tissue viability before selecting an intervention.
Patients presenting with tandem lesions demonstrate diverse clinical features depending on ischemic burden and collateral recruitment. In the registry cohort, researchers observed distinct clinical differences between actively treated patients and conservatively managed individuals. Specifically, treated patients presented with markedly higher neurological deficits upon emergency admission. The median baseline National Institutes of Health Stroke Scale score reached 9 in the treated cohort. In contrast, non-treated patients presented with a median score of only 4. This noticeable difference highlights that emergency teams prioritize acute interventions for individuals experiencing severe functional impairment. Conversely, clinicians often choose conservative medical therapy for patients displaying mild or non-disabling symptoms to prevent procedural injury. Nevertheless, patients with seemingly minor deficits face persistent risks of secondary neurological deterioration. Therefore, vigilant neurological monitoring remains vital throughout the acute hospitalization phase. Furthermore, quantitative perfusion imaging provides critical data regarding tissue at risk, supporting objective therapeutic selection.
Optimal management for distal tandem pathology requires customized revascularization strategies. Among the 28 patients identified with distal tandem occlusions, 11 individuals received active reperfusion or revascularization therapies. Clinicians implemented diverse procedural combinations reflecting individualized anatomical and physiological factors. Five patients received intravenous thrombolysis alone, successfully avoiding mechanical catheter manipulation in delicate distal branches. Meanwhile, two patients underwent isolated mechanical thrombectomy. Additionally, interventional teams combined therapies to address both proximal and distal lesions simultaneously. For instance, one patient received thrombolysis, mechanical thrombectomy, and emergent carotid artery stenting. Another patient received thrombectomy coupled with percutaneous transluminal angioplasty. Furthermore, surgical carotid endarterectomy served as the revascularization method in two cases, including one patient who also received thrombolysis. Consequently, clinical practice demonstrates significant procedural variability rather than a uniform therapeutic standard. Neurovascular specialists must carefully balance systemic pharmacotherapy against endovascular or surgical interventions to maximize reperfusion while minimizing procedural harm.
Evaluating functional recovery provides essential insight into the true effectiveness of acute revascularization. In this study, investigators assessed three-month outcomes using the modified Rankin Scale. Despite presenting with substantially higher initial stroke scores, treated patients achieved favorable clinical recovery. Active revascularization effectively mitigated extensive tissue infarction and stabilized fragile cerebral perfusion. However, functional trajectories reflected the complex nature of severe neurovascular disease. Patients undergoing active treatment overcame marked initial deficits to regain functional independence. Conversely, non-treated individuals often maintained favorable functional status due to their milder baseline neurological presentation. Nonetheless, relying solely on medical management carries substantial recurrent stroke risk if carotid instability persists. Therefore, long-term secondary prevention and delayed revascularization warrant careful consideration in non-emergent cases. Moreover, structured functional evaluations emphasize that aggressive recanalization can salvage critical brain tissue. Consequently, multidisciplinary teams must weigh acute recovery potential rather than relying solely on arbitrary symptom thresholds.
Performing endovascular thrombectomy in distal middle cerebral artery branches poses substantial technical hurdles. While modern devices excel in proximal M1 segments, entering M3 and M4 branches requires extreme caution. Distal arteries feature narrow diameters, tortuous trajectories, and fragile vascular walls. As a result, microcatheter navigation carries heightened risks of arterial dissection, vasospasm, and fatal vessel perforation. Furthermore, treating the proximal carotid occlusion introduces tactical dilemmas. Deploying a carotid stent requires immediate dual antiplatelet therapy, which elevates intracerebral hemorrhage risks following distal reperfusion. Alternatively, prioritizing intracranial thrombectomy first may leave an unstable carotid lesion prone to acute re-occlusion. Balloon angioplasty provides a temporary lumen, but elastic recoil may restrict downstream flow. Consequently, neurointerventionalists must select miniaturized stent retrievers or low-profile aspiration catheters specifically engineered for peripheral anatomy. Thus, comprehensive technical expertise remains essential for achieving recanalization while preventing procedural complications.
These registry findings offer practical insights for optimizing institutional stroke protocols. First, clinicians should maintain high clinical suspicion for distal branch blockages whenever acute internal carotid occlusion is detected. Multiphase computed tomography angiography reliably identifies peripheral vascular dropouts that standard imaging might miss. Second, acute stroke teams should not dismiss patients with distal occlusions simply due to peripheral location. When baseline neurological deficits are pronounced, timely recanalization offers substantial functional benefits. Third, hospital networks must establish flexible treatment algorithms that support individualized therapeutic choices. Whether clinicians utilize intravenous thrombolysis, mechanical thrombectomy, acute stenting, or surgical endarterectomy, rapid collaborative decision-making is indispensable. In addition, neurologists, interventionalists, and vascular surgeons must coordinate closely to expedite reperfusion workflows. Furthermore, future multicenter prospective trials remain necessary to define standardized revascularization protocols for distal tandem pathology. Until definitive trial data emerge, individualized hemodynamic assessment remains the cornerstone of effective acute management.
A tandem occlusion involves a concurrent proximal internal carotid artery occlusion alongside an intracranial occlusion located in the distal middle cerebral artery branches, specifically the M3 or M4 cortical segments. This rare condition disrupts both proximal inflow and peripheral cerebral perfusion, creating substantial diagnostic and therapeutic challenges.
Stroke severity strongly guides clinical decision-making. Patients presenting with higher baseline neurological deficits, indicated by elevated National Institutes of Health Stroke Scale scores, more frequently receive aggressive revascularization therapies. Conversely, clinicians often manage patients with mild baseline symptoms conservatively to prevent potential procedural complications in delicate distal intracranial arteries.
Navigating distal M3 and M4 branches requires traversing diminutive, tortuous vessels with fragile arterial walls. Standard thrombectomy devices carry elevated risks of arterial dissection, vasospasm, and vessel perforation in these peripheral locations. Consequently, neurointerventionalists must carefully select low-profile microcatheters and weigh procedural hazards against expected clinical benefits.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A registry analysis evaluates clinical characteristics and 3-month functional outcomes in acute ischemic stroke patients presenting with rare tandem lesions involving internal carotid artery occlusion and distal middle cerebral artery occlusion.
Today
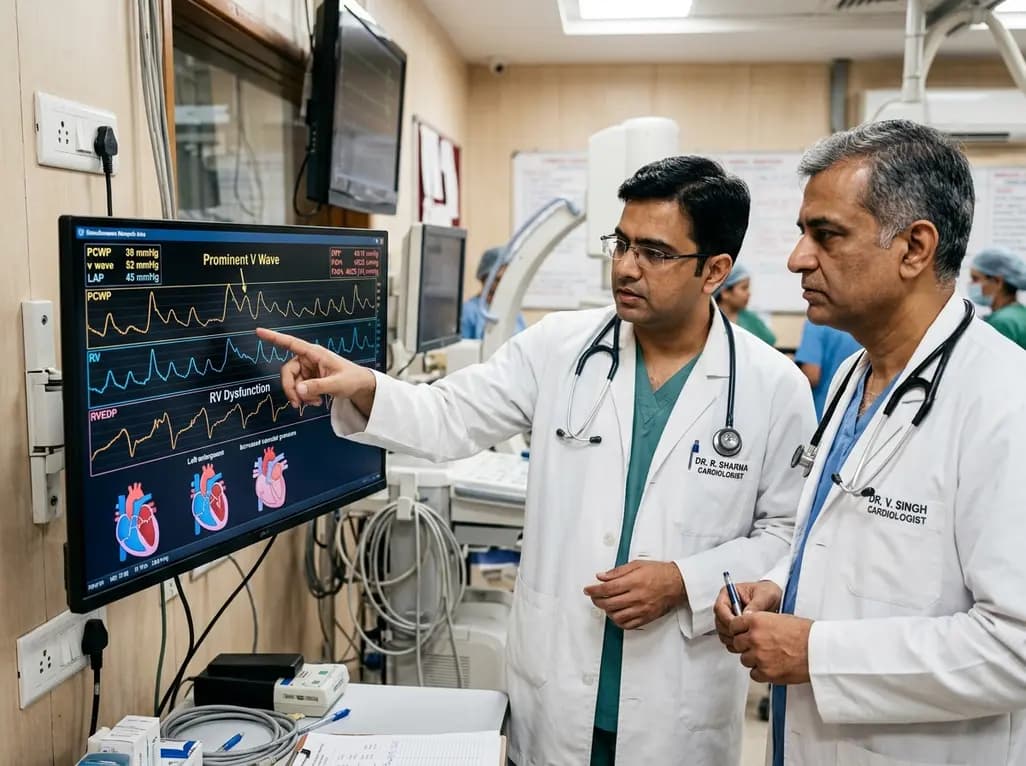
Left atrial stiffening generates prominent V waves that pressurize the pulmonary circulation and augment right ventricular afterload independently of intrinsic pulmonary vascular disease in patients with heart failure with preserved ejection fraction.
Today

A meta-analysis demonstrates that secondhand smoke exposure significantly elevates fetal loss risk by 21% among nonsmoking pregnant women. Clinicians must implement household screening and family-centered cessation interventions to prevent avoidable miscarriages and stillbirths.
Today

Preclinical validation demonstrates that a novel contact force-integrated pulsed field quantization index accurately predicts lesion depth in real time, achieving 100% durable pulmonary vein isolation without collateral injury.
Today
A new cross-sectional evaluation reveals how regional lean mass and bone mineral content interact in resistance-trained men, showing that whole-body size and allometric scaling explain shared musculoskeletal phenotypes and strength relationships.
Today

Explore the emerging role of glucose metabolic reprogramming in exercise-attenuated osteoporosis, examining how physical activity influences osteoblast glycolysis, osteoclast bioenergetics, and skeletal remodeling pathways to improve bone mineral density.
Today
