

Loading, please wait...
Loading, please wait...

Acute ischaemic stroke due to large vessel occlusion demands rapid endovascular reperfusion to salvage viable brain tissue. However, mechanical thrombectomy outcomes often differ markedly among patient cohorts despite technically successful recanalisation. Emerging clinical research shows that underlying socioeconomic status plays a major role in long-term neurological recovery. While endovascular interventions restore cerebral perfusion, the social determinants of health dictate systemic vascular resilience, baseline comorbid illness, and subsequent access to rehabilitation. Consequently, clinicians must recognize that procedural success does not automatically guarantee optimal functional recovery.
Recently, clinical investigators evaluated whether neighborhood-level socioeconomic disparities influence post-thrombectomy recovery in urban settings. Even within universal healthcare environments offering equal bedside access, social disadvantage creates hidden barriers. For example, chronic stress, nutritional deficits, and poorly controlled vascular risk factors impair microvascular integrity over decades. In addition, lower health literacy often delays emergency medical presentation, thereby narrowing salvageable penumbral volume. Therefore, modern stroke networks must examine how socioeconomic vulnerability undermines interventional gains. Understanding these complex disparities allows healthcare professionals to anticipate post-procedure complications and optimize personalized multidisciplinary care pathways.
A recent multicentre study in London examined 1,219 patients who underwent emergency endovascular therapy for anterior circulation large vessel occlusion. Specifically, investigators gathered clinical data from three comprehensive stroke centres between 2021 and 2023. They measured socioeconomic status using the English Index of Multiple Deprivation. This validated metric combines income, employment, education, housing, crime rates, and living environment into a composite score. Researchers categorized patients into more deprived and less deprived cohorts based on national quintiles. Notably, among the cohort, 533 individuals resided in more deprived areas, whereas 686 lived in less deprived neighborhoods.
To prevent selection bias, the researchers applied inverse probability weighting to balance baseline demographics and medical variables. Furthermore, they measured primary clinical outcomes at 90 days using the modified Rankin Scale. In particular, functional independence required achieving a score of zero to two. Secondary endpoints included successful arterial recanalisation, early neurological change, all-cause 90-day mortality, symptomatic intracerebral haemorrhage, and any haemorrhagic transformation. Additionally, investigators employed LASSO regression and receiver operating characteristic analyses to evaluate how accurately deprivation metrics predict functional outcomes alongside age, baseline neurological deficits, and systemic vascular comorbidities.
The study results revealed stark differences between socioeconomic tiers despite comparable arterial recanalisation rates across all centres. Notably, socioeconomically deprived patients exhibited significantly lower rates of functional independence at 90 days, with a relative risk of 0.79. Furthermore, shift analysis on the modified Rankin Scale demonstrated worse overall disability trajectories among disadvantaged individuals. Deprived patients experienced an odds ratio of 1.29 for shifting toward greater disability. Thus, equitable catheter-based revascularisation did not translate into equivalent functional survival.
Even more concerningly, secondary safety endpoints showed pronounced disparities in post-procedural cerebral bleeding. Disadvantaged patients suffered more than double the risk of symptomatic intracerebral haemorrhage, displaying a relative risk of 2.07. Similarly, their risk for any haemorrhagic transformation rose substantially, reaching a relative risk of 1.47. In addition, subgroup analyses highlighted that socioeconomic deprivation exerted an especially pronounced negative impact among Asian and mixed ethnicity cohorts. Ultimately, a multivariate predictive model combining deprivation rank, patient age, biological sex, hypertension history, and initial stroke severity yielded an area under the curve of 0.656 for functional independence.
Clinicians must evaluate why socioeconomic disadvantage causes increased reperfusion injury and worse neurological outcomes. First, chronic poverty accelerates vascular aging through prolonged neuroendocrine stress, systemic inflammation, and microvascular rarefaction. Consequently, chronically diseased cerebral vessels fail to autoregulate effectively once interventional radiologists re-establish arterial blood flow. This sudden hyperperfusion damages fragile capillary beds, precipitating symptomatic intracerebral haemorrhage. Moreover, baseline endothelial dysfunction impairs the integrity of the blood-brain barrier before the patient ever arrives in the angiosuite.
In addition, unmeasured social determinants severely impair the post-acute recovery trajectory. Economically disadvantaged patients frequently struggle with medication adherence due to prescription costs or transport limitations. Furthermore, they encounter major structural hurdles when attempting to access intensive outpatient physiotherapy and occupational rehabilitation. Malnutrition, overcrowded living spaces, and limited social support networks also amplify secondary medical complications such as aspiration pneumonia and venous thromboembolism. Therefore, the physiological vulnerability established by lifelong deprivation continues to harm patients long after acute recanalisation concludes.
These findings hold profound relevance for clinicians managing acute ischaemic stroke within India's highly fragmented healthcare landscape. In India, socioeconomic disparities are stark, and out-of-pocket expenditure funds most emergency endovascular procedures. Although major metropolitan tertiary centres possess world-class thrombectomy capabilities, pre-hospital transport delays remain pervasive among underprivileged communities. Consequently, socioeconomically disadvantaged stroke patients often present outside standard therapeutic time windows with larger ischemic core volumes. Furthermore, untreated hypertension and uncontrolled diabetes occur at high rates across lower socioeconomic groups in South Asia.
Accordingly, Indian stroke centres must implement comprehensive risk mitigation strategies immediately after performing endovascular procedures. Interventional teams should maintain stringent blood pressure control protocols to protect fragile microvessels against reperfusion haemorrhage. Moreover, hospital administrators must establish subsidized neurorehabilitation programs and institutional patient-assistance pathways for vulnerable families. Dedicated stroke navigators should monitor outpatient drug compliance, dietary modification, and secondary preventive therapies. Ultimately, addressing structural inequalities alongside acute catheter intervention remains essential to achieving true clinical equity across diverse patient demographics.
Socioeconomically disadvantaged patients face higher chronic disease burdens, prolonged pre-hospital transport delays, and impaired microvascular reserve. Furthermore, chronic vascular inflammation and blunted autoregulation increase ischemic vulnerability. Following acute recanalisation, reduced access to structured neurorehabilitation, financial barriers to secondary preventive medications, and limited community social support further restrict long-term functional recovery.
Chronic deprivation associates with persistent untreated hypertension and systemic endothelial dysfunction, which severely compromise the blood-brain barrier. Consequently, when endovascular therapy re-establishes intracranial blood flow, fragile microvessels cannot tolerate sudden arterial reperfusion pressures. This microvascular fragility triggers hemorrhagic transformation and symptomatic bleeding significantly more often than in affluent cohorts.
Stroke teams should implement strict post-procedural hemodynamic monitoring to curb reperfusion hemorrhage in vulnerable patients. Additionally, institutions must establish dedicated social work coordination to secure subsidized secondary preventive medications. Clinicians should also connect disadvantaged individuals with community-based physical rehabilitation, ensuring comprehensive long-term recovery support regardless of personal socioeconomic position.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A London multicentre study reveals that socioeconomic deprivation significantly reduces 90-day functional independence and doubles symptomatic intracranial hemorrhage risks following mechanical thrombectomy for acute ischaemic stroke, highlighting critical disparities in acute stroke care systems.
Today
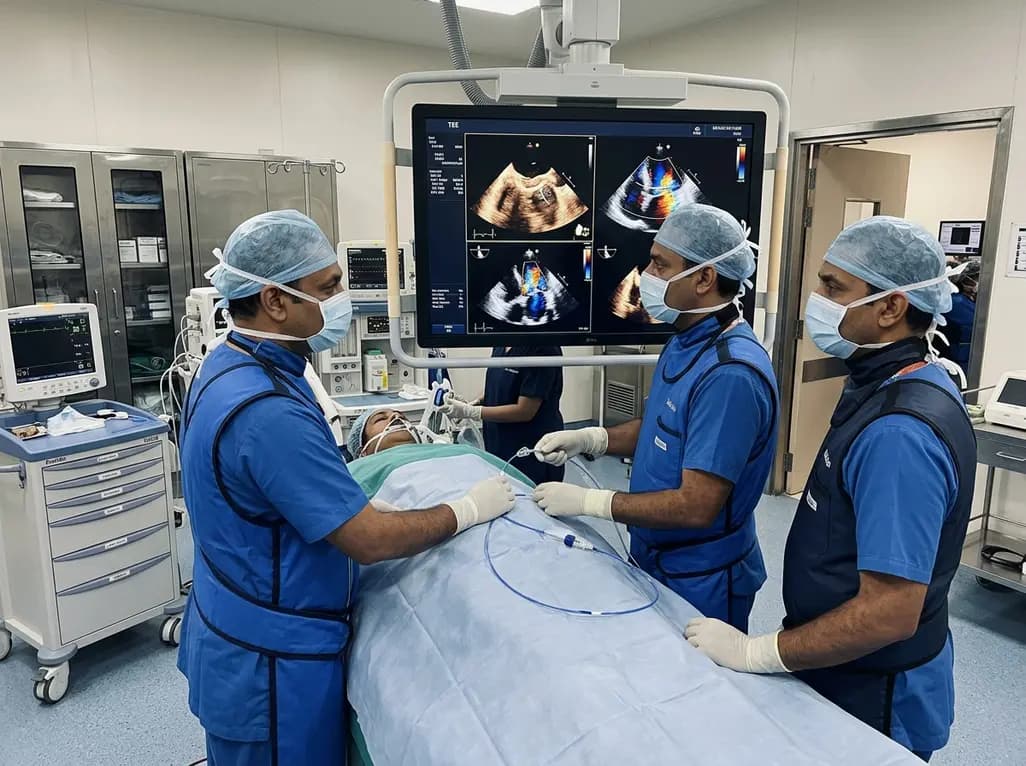
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today
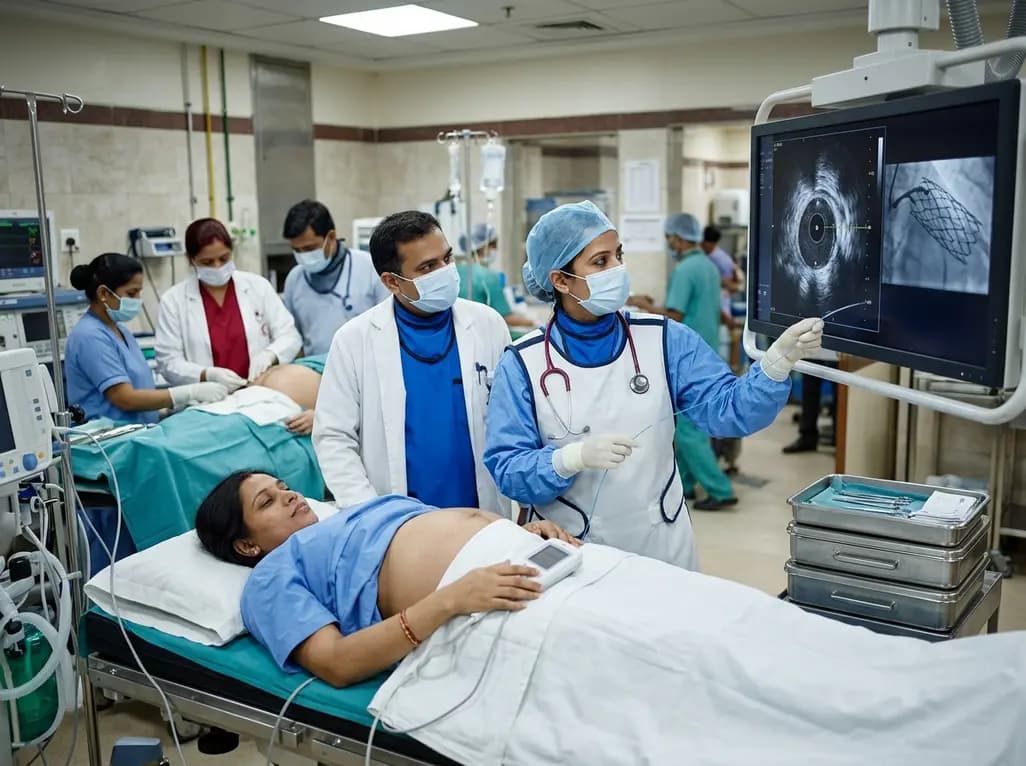
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday
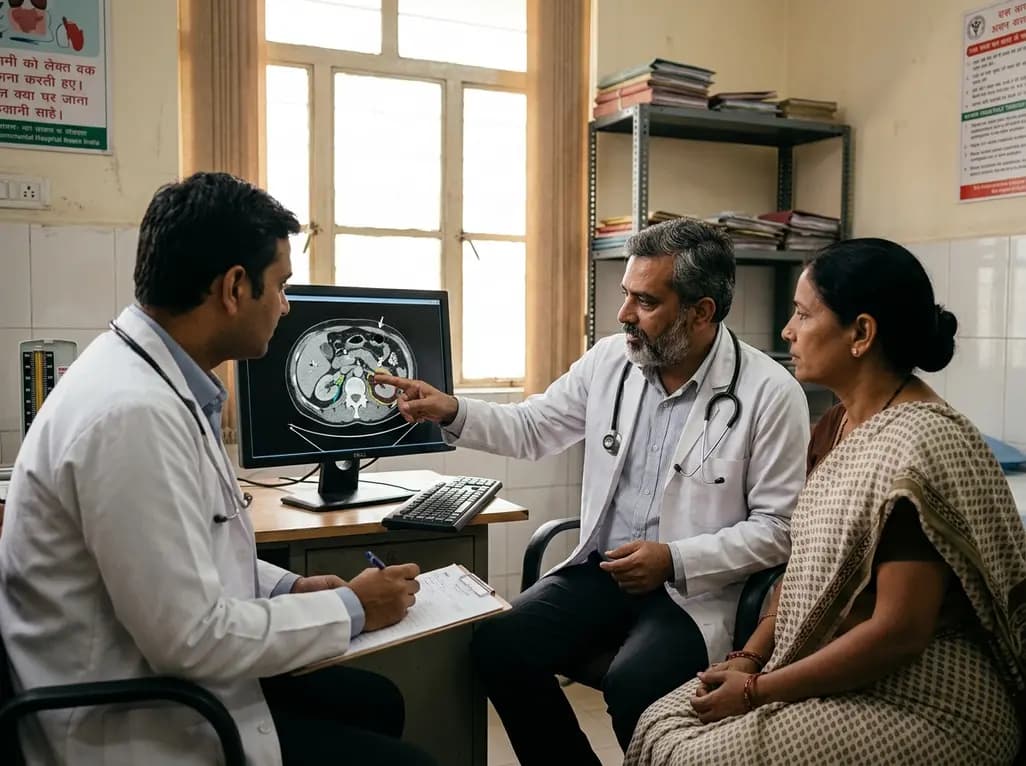
New ADIPO-CKD study findings demonstrate that both GLP-1 receptor agonists and SGLT2 inhibitors significantly reduce perirenal adipose tissue thickness in chronic kidney disease patients, with GLP-1 therapy achieving greater reductions, highlighting a novel mechanism for cardiorenal metabolic protection.
Today
