

Loading, please wait...
Loading, please wait...

Maternal healthcare professionals face substantial hurdles in addressing late maternal morbidity, particularly when substance use arises after hospital discharge. Clinical evidence demonstrates that postpartum opioid readmissions present a severe threat to maternal safety during the critical 180-day window following childbirth. Although overall national discharge trends indicate modest declines in substance-related hospitalizations, vulnerable patient cohorts continue to encounter elevated risks. Clinicians must recognize that maternal substance use frequently emerges in individuals without any prior documented history of opioid misuse during antenatal care or delivery. Consequently, identifying subtle social determinants of health offers obstetricians and primary care clinicians a crucial opportunity to intervene before catastrophic events unfold.
Peripartum substance use disorders contribute dramatically to preventable maternal mortality worldwide. Recent epidemiological data evaluating over ten million delivery hospitalizations reveals that approximately 3.0 per 10,000 postpartum individuals experience an unexpected readmission linked to newly documented opioid misuse within six months of delivery. Fortunately, the incidence of these readmissions decreased from 3.7 to 2.2 per 10,000 deliveries between 2016 and 2021, representing an average annual percent decline of over ten percent. However, this statistical reduction masks persistent disparities among socioeconomically disadvantaged women. Many mothers without prior diagnostic codes for opioid dependence develop severe complications after discharge, which underscores significant gaps in transitional postpartum surveillance. Therefore, clinicians must re-examine systemic vulnerabilities that expose new mothers to prescription exposure, self-medication, and unregulated opioid consumption during recovery.
Among various adverse social circumstances, physical environmental barriers exert an overwhelming influence on maternal outcomes. Multivariable analyses indicate that patients experiencing adverse physical environments, unstable housing, or severe economic distress carry a nearly five-fold greater risk of readmission for opioid misuse compared to stably housed peers. While unadjusted evaluations initially implicated educational and employment deficits, these associations diminished after adjusting for broader clinical and demographic covariates. Consequently, living conditions emerge as the primary social driver of substance-related hospital returns. Unstable housing creates chronic physiological stress, disrupts routine infant care, and severely impairs access to scheduled outpatient evaluations. Furthermore, individuals lacking secure shelter often reside in neighborhoods with easy access to illicit substances and minimal community-level mental health resources, which drastically accelerates vulnerability.
A notable finding from contemporary readmission studies is the occurrence of severe opioid-related events among women with entirely negative prenatal substance histories. Historically, perinatal addiction protocols focused almost exclusively on patients with active substance use disorders recognized during antenatal visits. However, postpartum pain management, surgical trauma from cesarean deliveries, and acute psychological distress can trigger opioid misuse in opioid-naive individuals. When structural hardships compound these clinical stressors, patients rapidly encounter adverse trajectories. Moreover, post-discharge pain regimens occasionally provide excess opioid tablets without structured tapering plans, inadvertently creating risk. Healthcare teams must therefore avoid assuming that an uneventful delivery hospitalization guarantees long-term safety, especially when adverse living conditions jeopardize patient stability.
Mitigating the burden of late postpartum readmissions demands structured and empathetic screening protocols. Clinical teams should integrate standardized screening tools for social determinants of health directly into prenatal, intrapartum, and discharge assessments. Specifically, physicians should screen for unstable living arrangements, food insecurity, and interpersonal safety alongside routine obstetric parameters. When clinical teams identify housing insecurity or environmental hazards, they must mobilize medical social workers and care navigators immediately. In addition, providing comprehensive discharge planning that connects patients with municipal housing assistance, community doulas, and behavioral health specialists can buffer against downstream crises. Transitioning from isolated clinical encounters to connected social support frameworks represents an essential defense against late maternal morbidity.
Obstetricians, family physicians, and community nurses must adopt multimodal pain strategies to limit unnecessary outpatient opioid exposure. Utilizing scheduled nonsteroidal anti-inflammatory drugs and acetaminophen provides effective analgesia while reducing dependency on outpatient opioid scripts. Furthermore, maternity units should establish close follow-up intervals, scheduling telehealth check-ins or home health nursing visits within the first two weeks postpartum rather than delaying until the conventional six-week visit. Clinicians should also educate families regarding safe medication storage, proper disposal methods, and naloxone administration. By actively coordinating medical interventions with local social welfare systems, healthcare providers can protect postpartum individuals from the devastating intersection of environmental instability and substance-related harm.
Adverse physical environments and housing instability serve as the strongest independent drivers of late readmissions. When individuals navigate chaotic living conditions, severe financial strain, and inadequate social safety nets, unmanaged postpartum pain or emergent mental health stressors can rapidly escalate into opioid misuse, even without prior substance history.
Clinical data highlights that significant vulnerability persists across the entire 180-day window following delivery. While traditional postpartum obstetric care concludes at six weeks, environmental stressors and untreated behavioral health needs often compound months later, emphasizing the necessity of extending continuous maternal coverage and clinical follow-up for a full year.
Healthcare teams should employ multimodal, opioid-sparing postpartum analgesia protocols, screen universally for housing and social needs, and coordinate early outpatient visits. Connecting vulnerable mothers directly to medical social work, community health workers, and supportive housing resources prior to discharge substantially minimizes the danger of subsequent readmission.
Disclaimer: This content is for informational and educational purposes only. It is not intended to replace professional medical advice, diagnosis, or treatment. Always consult a qualified physician or healthcare provider regarding any clinical situation or medical condition. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





New clinical research demonstrates that adverse physical environments and housing instability strongly increase the risk of postpartum opioid readmissions within 180 days after delivery, highlighting the urgent need for comprehensive screening and supportive maternal community interventions.
Today
A randomized controlled trial demonstrates that a 12-week Tai Chi program significantly reduces post-transplant fatigue, enhances sleep quality, and increases 6-minute walk distance in renal transplant recipients, providing a safe and effective non-pharmacological rehabilitative exercise therapy.
Today

A study shows that the aggregate index of systemic inflammation (AISI) significantly associates with elevated myocardial injury markers, including cardiac troponin T and CK-MB, in patients with coronary heart disease, highlighting its potential utility for cardiovascular risk stratification.
Today
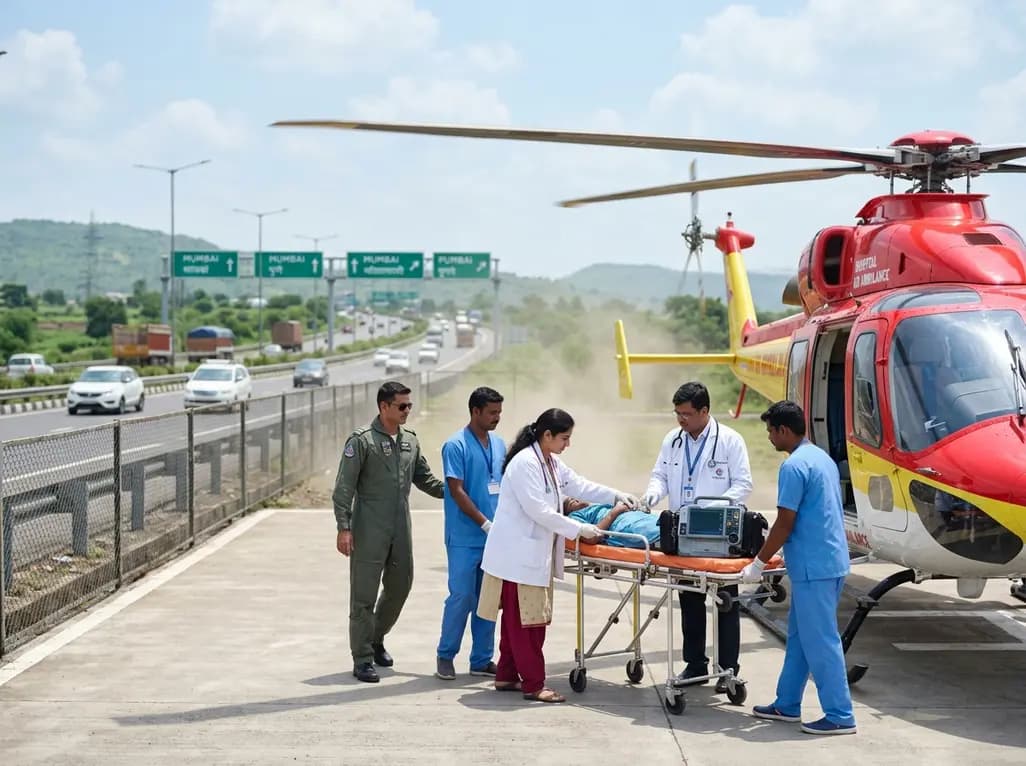
The state government is deploying helicopter emergency medical services across the Mumbai-Pune Expressway, Samruddhi Mahamarg, and Mumbai-Goa Highway. This initiative establishes unified standard operating procedures to enable rapid triage, advanced prehospital resuscitation, and seamless trauma care transfers.
Today
A systematic review of 66 preclinical studies reveals that GLP-1 mono-agonists modulate central reward processing. These findings demonstrate significant reductions in palatable food intake, substance self-administration, and compulsive behaviors, offering novel neurobiological targets for neuropsychiatry.
Today
