

Loading, please wait...
Loading, please wait...

Surgeons, intensivists, and neurologists frequently confront complex dilemmas when treating traumatic brain injury (TBI) patients in prolonged coma or vegetative states. Historically, many healthcare providers presumed that patients who survive disorders of consciousness would inevitably endure devastating psychological distress and profound subjective suffering. Consequently, this persistent therapeutic nihilism has influenced early decisions surrounding the withdrawal of life-sustaining measures. However, landmark longitudinal data now challenge these pessimistic assumptions, revealing surprisingly positive subjective wellbeing among survivors.
Clinicians often equate severe neurological impairment with an unacceptable quality of life. Therefore, when patients emerge from a minimally conscious state with residual physical limitations, teams may worry that these individuals suffer persistently. Furthermore, proxy respondents like family members frequently project their own existential distress onto the patient. In reality, modern evidence demonstrates a pronounced divergence between external disability assessments and internal life satisfaction. This phenomenon, often termed the disability paradox, highlights that individuals adapt remarkably well to altered functional baselines. When evaluating individuals recovering from severe head trauma, physicians must distinguish between functional dependence and psychological distress. While motor impairments and cognitive slowdowns may persist, emotional adaptation frequently outpaces physical recovery. As a result, early nihilistic pronouncements often fail to reflect the true trajectory of personal wellbeing. Intensive neurorehabilitation programs continually show that consciousness recovery can occur over prolonged intervals. Consequently, clinical teams should avoid assuming that severe initial trauma precludes a fulfilling subjective recovery. Recognizing this psychological resilience is vital for guiding realistic and compassionate discussions with families during acute neurocritical care.
To investigate these outcomes empirically, researchers analyzed prospective data from the multisite Traumatic Brain Injury Model Systems program. Specifically, the study cohort enrolled 887 individuals who entered inpatient rehabilitation with severe disorders of consciousness, defined rigorously by an absence of command-following. The participant population comprised primarily younger adult males with a mean age of approximately 37 years. Additionally, these patients entered rehabilitation an average of 34 days following initial trauma, reflecting profound acute-phase injury severity. By the one-year follow-up, exactly 50% of these patients had successfully regained the capacity to provide reliable self-reported psychological measures. This emergence of communicative ability represents a monumental recovery milestone after severe trauma. Moreover, the investigators systematically tracked subjective wellbeing using standardized psychometric instruments. Rather than relying on surrogate reports, the protocol prioritized authentic direct patient voices. Consequently, the findings provide unprecedented clarity regarding the internal emotional lives of survivors. These observational results directly challenge older prognostic models that viewed prolonged unconsciousness as an irreversible dead end.
The investigators evaluated subjective recovery using three well-validated clinical tools: the Satisfaction With Life Scale, the Generalized Anxiety Disorder-7, and the Patient Health Questionnaire-9. Remarkably, the cohort demonstrated a mean Satisfaction With Life score of 20.38, indicating an average rating of average-to-high life satisfaction. Furthermore, the mean anxiety score registered at 4.00, while the mean depression score remained low at 5.22. Most notably, only 15% of respondents endorsed dissatisfaction with life, and merely 9% reported extreme dissatisfaction. Similarly, clinically significant symptoms of generalized anxiety and major depression appeared in only 14% and 16% of the survivors, respectively. These psychological morbidity rates closely mirror those observed in cohorts with mild or moderate traumatic brain injury. Furthermore, these figures compare favorably with baseline prevalence rates observed across the general non-injured population. Therefore, physical dependence does not inherently breed mental illness or existential despair in this clinical group. Instead, survivors display substantial cognitive and emotional adjustment despite lingering physical restrictions. These objective findings provide robust data to refute pervasive clinical pessimism.
Longitudinal follow-up provides crucial perspective on whether initial optimism wanes as survivors confront chronic physical disability. Importantly, the researchers extended their evaluation to two-year and five-year intervals after the initial traumatic insult. The empirical findings demonstrated that the favorable psychological outcomes remained stable throughout the five-year observation period. Over time, rates of anxiety, depression, and life dissatisfaction did not escalate despite persistent long-term challenges with community reintegration and physical independence. Thus, the psychological adjustment observed at one year represents a durable state rather than transient euphoria. Neuroplastic changes, adaptive coping mechanisms, and personalized social support networks likely underpin this long-term emotional equilibrium. Moreover, patients often recalibrate their internal expectations and redefine meaningful goals following catastrophic injury. Consequently, clinicians can reassure families that subjective wellbeing does not inevitably degrade over prolonged survivorship. These long-term observations substantiate the critical value of durable community support and continuous outpatient neurorehabilitation programs. Even when complete physical independence remains unattainable, survivors can sustain fulfilling, joyful, and emotionally stable lives across decades.
These insights carry profound ethical and practical implications for intensivist teams and neurosurgeons managing acute traumatic coma. Frequently, clinicians consider withdrawal of life-sustaining therapy during the first two weeks of hospitalization based on predicted poor quality of life. However, these premature clinical assumptions often rely on flawed perceptions of what constitutes an acceptable existence. Because physicians routinely overestimate the misery associated with chronic physical disability, they may inadvertently guide surrogate decision-makers toward premature withdrawal. In contrast, the current evidence mandates cautious, patient prognostic stewardship during acute care. Multidisciplinary teams must afford patients sufficient time to emerge and benefit from comprehensive neurorehabilitation protocols. Additionally, clinicians should educate surrogate decision-makers about the high likelihood of emotional adaptation and life satisfaction among survivors. When families understand that residual physical dependency does not preclude happiness, their perspectives on goals of care often transform. Therefore, delaying irreversible decisions allows patients the opportunity to achieve meaningful long-term cognitive and emotional outcomes.
Achieving these favorable long-term outcomes requires structured, continuous, and specialized neurorehabilitation pathways. Early rehabilitation must prioritize sensory stimulation, active medical management of post-traumatic complications, and targeted neuropharmacological interventions. For instance, medications such as amantadine can accelerate cognitive emergence and motor responsiveness during the post-acute phase. Furthermore, speech-language pathologists, physical therapists, and neuropsychologists play pivotal roles in establishing functional communication systems. Facilitating any reliable mode of communication empowers individuals to express preferences, pain levels, and personal goals. Simultaneously, rehabilitation teams must provide comprehensive education and emotional counseling for caregivers throughout the transition home. Because caregiver burnout can undermine the recovery environment, sustaining caregiver mental health directly preserves patient wellbeing. In addition, health systems must bridge acute care with long-term community services to maintain functional gains over time. By combining scientific optimism with aggressive rehabilitative support, modern clinicians can guide patients from profound coma to fulfilling survivorship.
Yes, long-term studies reveal that most survivors who recover consciousness report favorable quality of life. Longitudinal data demonstrate that fewer than one-fourth report life dissatisfaction. Most patients achieve psychological wellbeing comparable to individuals with mild injuries or the general population, showing that residual disability does not prevent personal fulfillment.
Clinically significant psychological distress occurs in only a minority of recovered patients. Approximately 14% report significant anxiety symptoms, and roughly 16% experience major depression. These rates align closely with figures seen in mild traumatic brain injuries and the uninjured population, challenging traditional assumptions of severe post-recovery psychiatric morbidity.
These findings urge neurocritical care teams to exercise caution before withdrawing life-sustaining therapy prematurely. Because healthcare providers often overestimate the psychological burden of physical disability, they may convey excessively pessimistic prognoses. Recognizing that survivors frequently achieve meaningful life satisfaction justifies giving patients sufficient time to emerge and access comprehensive neurorehabilitation.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals should exercise their independent clinical judgment when making treatment decisions. Patient care should be individualized based on specific clinical presentations, comorbidities, and available medical resources. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A landmark TBI Model Systems study demonstrates that patients recovering from disorders of consciousness experience high life satisfaction and low depression rates up to five years post-injury, challenging nihilistic prognostic beliefs and informing critical care decisions.
Today
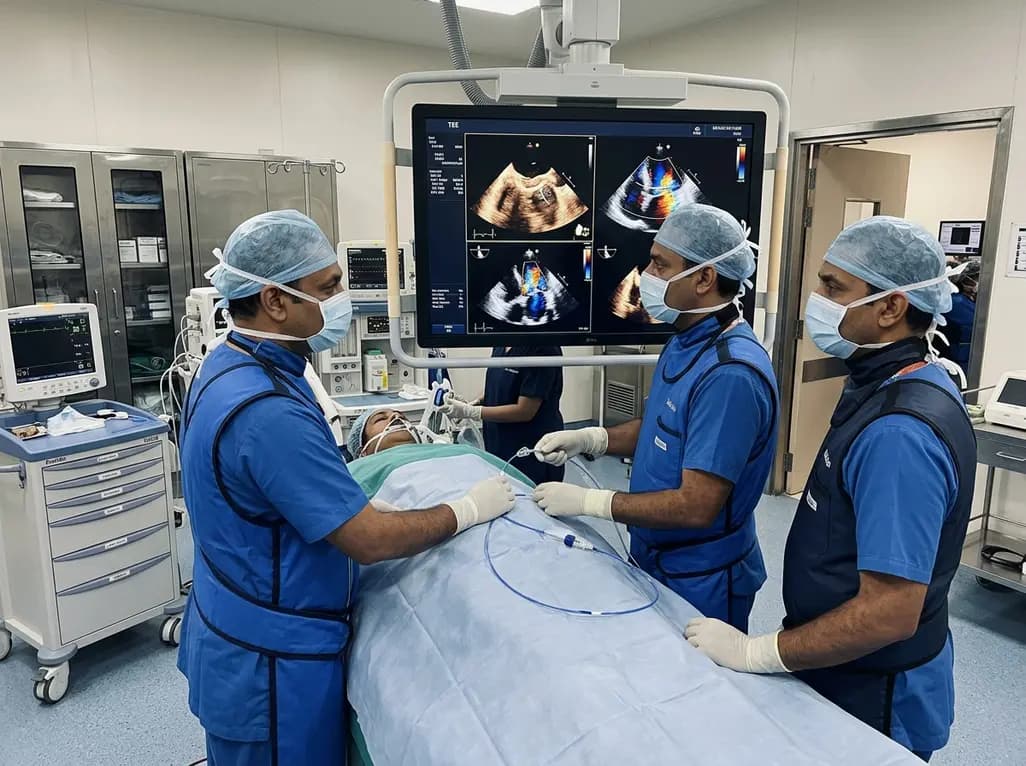
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today
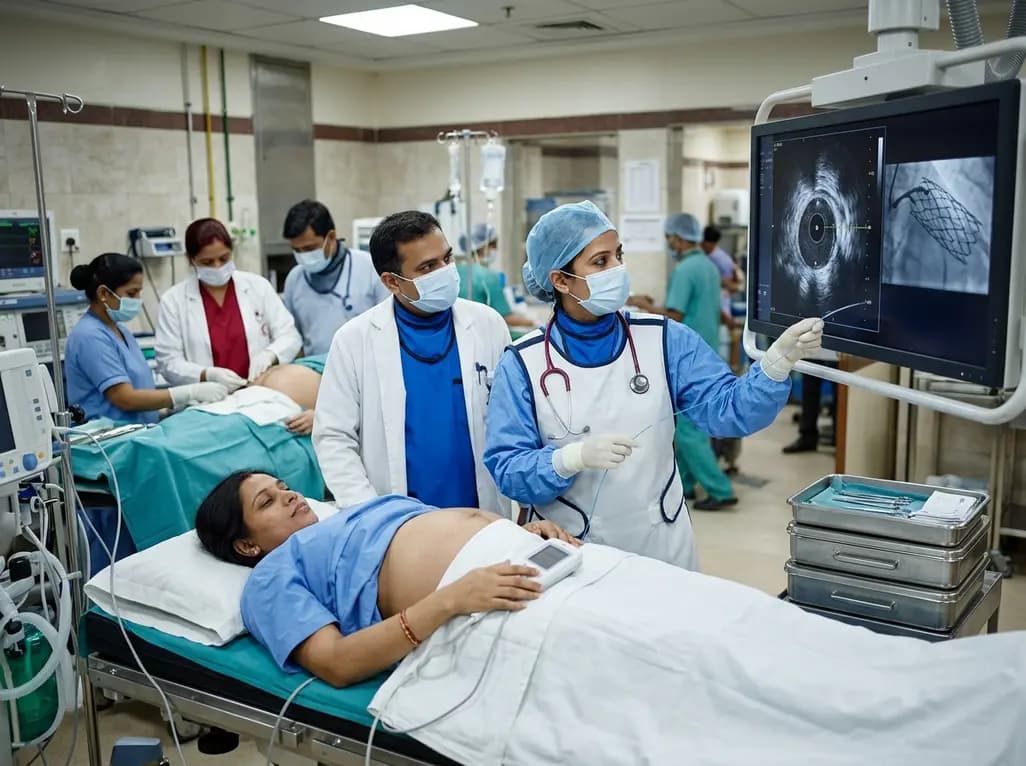
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday
New ADIPO-CKD study findings demonstrate that both GLP-1 receptor agonists and SGLT2 inhibitors significantly reduce perirenal adipose tissue thickness in chronic kidney disease patients, with GLP-1 therapy achieving greater reductions, highlighting a novel mechanism for cardiorenal metabolic protection.
Today
