

Loading, please wait...
Loading, please wait...

Managing intrahepatic cholestasis of pregnancy remains a critical clinical challenge for obstetricians and hepatologists worldwide. In clinical practice, maternal bile acid accumulation directly threatens fetal well-being while causing debilitating maternal pruritus. However, recent clinical investigations reveal that gestational age at disease presentation profoundly influences metabolic severity and therapeutic responsiveness. A newly published retrospective study highlights the therapeutic benefits of combining the Qingre Lishi formula with standard Western pharmacotherapy. This novel integrative approach offers meaningful clinical improvements in maternal hepatic biochemistry across distinct gestational cohorts.
Obstetric clinicians traditionally classify cholestatic disorders based on clinical presentation and gestational timing. Specifically, early-onset disease emerges before twenty-eight weeks of gestation, whereas late-onset manifestations typically arise during the late third trimester. This developmental divergence reflects different underlying pathological mechanisms. Women presenting early often carry genetic variations in hepatobiliary transport proteins, including ABCB4 and ATP8B1. Consequently, these early-onset patients encounter severe canalicular dysfunction much earlier in their pregnancies.
Furthermore, surging placental hormone levels, such as estrogen and progesterone metabolites, compound this pre-existing genetic vulnerability. As a result, bile acids progressively accumulate within maternal serum and hepatic parenchyma. In contrast, late-onset cholestasis often correlates directly with peak hormonal suppression of bile export pumps rather than deeply penetrant hereditary mutations. Therefore, early identification of gestational timing allows clinicians to stratify fetal risk profiles accurately. Moreover, recognizing these distinct biological patterns helps maternal-fetal medicine teams customize monitoring intervals and therapeutic intensities. Ultimately, timely chronological categorization empowers obstetricians to initiate targeted biochemical interventions before hazardous maternal-fetal complications occur.
The retrospective study evaluated clinical data from patients categorized into early-onset and late-onset cohorts. Interestingly, baseline biochemical assessments revealed distinct metabolic profiles between the two gestational groups. Patients presenting before twenty-eight weeks demonstrated significantly higher baseline total bile acid concentrations than those presenting after twenty-eight weeks. This striking difference underscores the pronounced metabolic burden endured by early-onset patients during critical stages of fetal development.
However, despite the marked divergence in circulating bile acids, baseline liver transaminases exhibited no statistically significant differences between groups. Both alanine aminotransferase and aspartate aminotransferase levels showed comparable hepatocellular leakage at the time of initial presentation. This clinical dissociation is noteworthy. Specifically, it demonstrates that serum transaminase levels alone cannot accurately quantify gestational disease severity or metabolic risk. Therefore, healthcare providers must prioritize serum total bile acid quantification over standard transaminase panels during clinical staging. Consequently, identifying this biochemical profile enables clinicians to anticipate elevated fetal risks even when maternal transaminase elevations appear modest.
The Qingre Lishi formula originates from traditional medical principles designed to clear damp-heat and enhance gallbladder function. In modern hepatology, botanical formulas often provide synergistic hepatoprotective and choleretic properties. Key herbal components typically include Artemisia capillaris, Gardenia jasminoides, and Scutellaria baicalensis. Pharmacological researchers have demonstrated that active constituents from these herbs stimulate hepatocyte bile acid export systems. Specifically, they upregulate canalicular transporters while dampening nuclear factor kappa B signaling pathways.
Additionally, these botanical extracts exhibit robust antioxidant activity that directly neutralizes reactive oxygen species in damaged liver tissue. Furthermore, the formula reduces toxic hydrophobic bile acid pools, effectively mitigating cellular injury in maternal hepatocytes. When clinicians combine this botanical prescription with conventional Western agents like ursodeoxycholic acid, the therapeutic synergy enhances bile secretion and alleviates maternal pruritus. Thus, the integrative protocol directly addresses both the underlying inflammatory cascade and the mechanical stagnation of bile flow. As a result, patients achieve improved liver function stability throughout the vulnerable phases of gestation.
Following intervention with the integrated protocol, both gestational groups achieved significant clinical and biochemical improvement. Notably, serum total bile acid levels decreased remarkably across all treated patients. However, the reduction in total bile acids proved substantially more pronounced in the early-onset group. Because early-onset patients presented with significantly elevated baseline bile acid levels, this dramatic decrease effectively narrowed the metabolic disparity between the early-onset and late-onset cohorts.
Moreover, both patient groups exhibited profound decreases in serum alanine aminotransferase and aspartate aminotransferase following treatment. This dual enzyme reduction indicates substantial resolution of hepatocellular inflammation and membrane stabilization. Furthermore, narrowing the bile acid gap between cohorts carries vital clinical significance. It suggests that integrative herbal therapy successfully overcomes the physiological inertia of early canalicular obstruction. Consequently, early-onset patients who typically face worse obstetric prognoses can achieve biochemical parameters approaching those of late-onset disease. Therefore, adding this herbal formula to standard care provides consistent, reproducible therapeutic efficacy across diverse gestational stages.
These biochemical findings offer vital practical insights for contemporary obstetricians, hepatologists, and integrative medical practitioners. First, clinicians must maintain high clinical suspicion for cholestasis when evaluating pruritus before twenty-eight weeks of gestation. Because early presentation portends severe bile acid elevation, immediate laboratory quantification of total bile acids is indispensable. Obstetricians should avoid relying solely on liver enzyme screens, as transaminases frequently underestimate early metabolic severity.
Second, combining targeted herbal therapy with Western medications represents an effective treatment paradigm for refractory or aggressive cholestasis. When healthcare teams implement this integrative strategy, they effectively lower toxic maternal bile acid pools and stabilize liver function. Consequently, this biochemical improvement may help reduce adverse perinatal outcomes, including spontaneous preterm labor, meconium-stained amniotic fluid, and sudden fetal death. Furthermore, multidisciplinary care models that unite obstetricians and hepatologists ensure comprehensive maternal-fetal surveillance. Clinicians should nevertheless monitor liver enzymes and bile acids biweekly until delivery, adjusting pharmacotherapy as gestational demands evolve.
Early-onset disease develops before twenty-eight weeks of gestation and typically features significantly higher baseline total bile acid concentrations. Consequently, these women face increased risks of maternal pruritus severity and adverse fetal outcomes. In contrast, late-onset disease manifests during the third trimester with comparatively lower initial bile acid elevations. Clinicians therefore consider early-onset presentations as metabolically aggressive phenotypes that require prompt laboratory stratification, intensive fetal surveillance, and targeted multi-agent therapeutic intervention.
Traditional Chinese and integrative medicine utilizes Qingre Lishi formulations to clear damp-heat and promote canalicular bile secretion. Modern pharmacological studies indicate that active botanical constituents stimulate biliary transport mechanisms, such as the bile salt export pump. Furthermore, these herbal compounds attenuate inflammatory cytokines, counteract oxidative stress, and protect hepatocytes from toxic bile acid accumulation. Consequently, patients exhibit improved enzymatic clearance, reduced serum transaminases, and substantial stabilization of hepatic functional parameters during gestation.
Serum total bile acid levels represent the primary biomarker for evaluating fetal hazard in gestational cholestasis. Specifically, maternal bile acids freely cross the placenta and can induce fetal cardiac dysrhythmias, placental chorionic vasoconstriction, or sudden intrauterine death. Moreover, concentrations exceeding forty to one hundred micromoles per liter directly correlate with spontaneous preterm delivery and meconium aspiration. Routine maternal serological tracking therefore guides clinicians in timing pharmacotherapy, planning delivery schedules, and mitigating perinatal morbidity.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Xue D et al. Differential effects of Qingre Lishi formula on serum total bile acid and liver function markers in early- and late-onset intrahepatic cholestasis of pregnancy. Afr J Reprod Health. 2026 Oct 14. doi: undefined. PMID: 42871076.
Ovadia C, Seed PT, Sklavounos A, et al. Association of adverse perinatal outcomes of intrahepatic cholestasis of pregnancy with biochemical markers: results of aggregate and individual patient data meta-analyses. Lancet. 2019;393(10174):899-909.
Chappell LC, Bell JL, Smith A, et al. Ursodeoxycholic acid versus placebo in women with intrahepatic cholestasis of pregnancy (PITCHES): a randomised controlled trial. Lancet. 2019;394(10201):849-860.
Bicocca MJ, Sperling JD, Chauhan SP. Intrahepatic cholestasis of pregnancy: review of diagnosis and management. Eur J Obstet Gynecol Reprod Biol. 2018;231:180-187.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A retrospective clinical study reveals that combining Qingre Lishi formula with Western medicine substantially decreases serum total bile acid levels in patients with intrahepatic cholestasis of pregnancy, demonstrating particularly pronounced metabolic benefits in early-onset presentations before 28 weeks.
Today

A randomized controlled trial demonstrates that a 12-week Tai Chi program significantly reduces post-transplant fatigue, enhances sleep quality, and increases 6-minute walk distance in renal transplant recipients, providing a safe and effective non-pharmacological rehabilitative exercise therapy.
Today

A study shows that the aggregate index of systemic inflammation (AISI) significantly associates with elevated myocardial injury markers, including cardiac troponin T and CK-MB, in patients with coronary heart disease, highlighting its potential utility for cardiovascular risk stratification.
Today
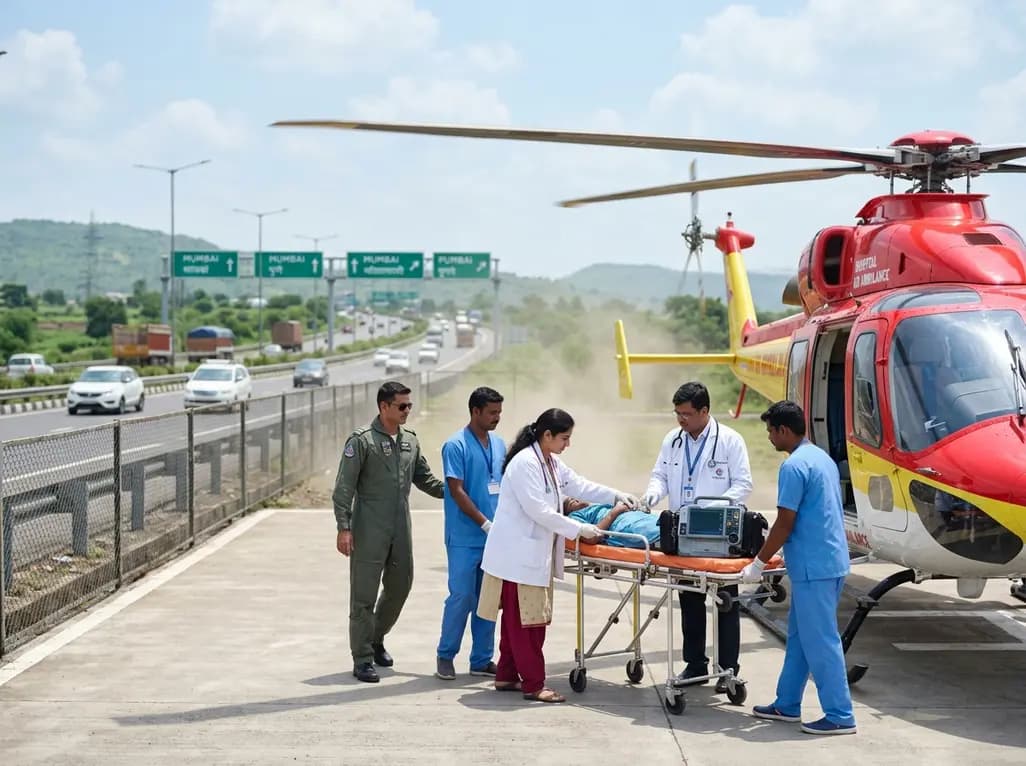
The state government is deploying helicopter emergency medical services across the Mumbai-Pune Expressway, Samruddhi Mahamarg, and Mumbai-Goa Highway. This initiative establishes unified standard operating procedures to enable rapid triage, advanced prehospital resuscitation, and seamless trauma care transfers.
Today

Calcimimetic therapy for primary hyperparathyroidism can induce profound tumor fibrosis, necrosis, and reduced vascularity. These changes alter ultrasound and 4D-CT imaging and cause dense recurrent laryngeal nerve adhesions, requiring heightened surgical vigilance during definitive parathyroidectomy.
Today
