

Loading, please wait...
Loading, please wait...

Gestation triggers profound physiological adaptations across virtually every maternal organ system. Many expectant mothers notice throat tightness, breath exhaustion, or altered pitch as their pregnancy progresses. Consequently, clinicians must recognize normal voice changes during pregnancy to avoid unwarranted invasive interventions. A rigorous scoping review recently synthesized laryngeal and vocal outcomes across diverse clinical domains. Therefore, this article examines how gestational hormones, altered biomechanics, and fluid retention reshape phonation. Ultimately, healthcare professionals can use these insights to reassure patients and optimize care.
Gestation introduces massive elevations in circulating estrogen and progesterone. Consequently, these hormonal surges alter vascular permeability and stimulate mucosal microstructures throughout the upper respiratory tract. Although classical teaching suggests dramatic acoustic disruption, empirical evidence reveals a nuanced reality. Objective acoustic parameters such as fundamental frequency, jitter, and shimmer generally remain stable across all trimesters. However, patients frequently perceive substantial vocal deterioration and effort during regular conversation. In addition, aerodynamic assessments consistently show a pronounced decline in maximum phonation time. This discrepancy occurs because maternal vocal cords experience increased tissue mass while the enlarging uterus simultaneously restricts diaphragmatic excursion. Therefore, pregnant individuals must exert greater muscular effort to sustain airflow across the glottis. Clinicians must recognize that self-reported vocal strain reflects true mechanical inefficiency rather than psychosomatic distress. Moreover, these aerodynamic deficits intensify during the third trimester as intra-abdominal pressure peaks. When obstetricians and otolaryngologists understand these combined respiratory and laryngeal constraints, they can properly guide symptomatic mothers. Thus, thorough clinical history taking remains the cornerstone of addressing these pervasive functional phonatory challenges.
Hormonal fluctuations during pregnancy induce systemic fluid retention that directly affects delicate phonatory tissue. Specifically, high estrogen levels increase vascular engorgement and tissue water content within the vocal fold lamina propria. Furthermore, elevated progesterone alters microvascular permeability and promotes localized mucosal congestion. Mechanistic animal models demonstrate marked thickening of the lamina propria alongside altered distribution of glycosaminoglycans. Notably, researchers have identified degranulating mast cells within cordal tissues, which further accelerates fluid extravasation. Direct laryngeal examinations in human cohorts corroborate these findings by revealing pronounced vocal fold edema. Consequently, the true vocal folds display reduced motility and sluggish mucosal wave dynamics during phonation. Clinicians observe that these structural alterations reach peak prominence during the late second and third trimesters. Additionally, gastroesophageal reflux disease, which affects over half of pregnant women, exacerbates posterior glottic inflammation. Stomach acid irritates already edematous tissues, causing vocal fatigue, throat clearing, and persistent hoarseness. Therefore, physicians must view gestational vocal symptoms through both an endocrine and gastroenterological lens. By identifying laryngeal edema early, doctors can prevent secondary vocal fold trauma.
Objective acoustic analysis provides fascinating insights into the maternal voice during pregnancy. Interestingly, standardized laboratory measures such as mean fundamental frequency rarely show permanent shifts in healthy cohorts. Clinicians might expect that swollen vocal folds would inevitably lower vocal pitch. However, compensatory muscular adjustments in the thyroarytenoid and cricothyroid complexes often maintain baseline acoustic frequency during conversational tasks. Conversely, aerodynamic performance shows significant and persistent physiological compromises across gestation. Multiple clinical studies consistently report a notable reduction in maximum phonation time among third-trimester patients. This functional limitation stems directly from diminished pulmonary vital capacity and higher subglottic pressure requirements. As the gravid uterus elevates the diaphragm, functional residual capacity drops substantially. Consequently, expectant mothers possess less usable air volume to sustain prolonged phonation. In addition, the increased mass and stiffness of edematous vocal folds demand higher phonation threshold pressure. Thus, speakers run out of breath rapidly while articulating sentences of ordinary length. Recognizing this physiological mismatch between preserved acoustic pitch and compromised airflow prevents unnecessary laryngeal imaging or aggressive therapeutic interventions.
While ordinary conversational speakers may experience only mild throat dryness, professional voice users face substantial occupational challenges. For example, classically trained singers frequently report a significant reduction in their upper vocal register during late pregnancy. Furthermore, many vocalists describe noticeable shifts in vocal timbre, loss of brightness, and accelerated vocal fatigue. Elevated mucosal mass dampens high-frequency vibratory modes, preventing effortless access to high pitch registers. In addition, vascular dilation makes superficial vocal fold capillaries markedly more fragile during pregnancy. High collision forces during strenuous singing can provoke vocal fold micro-hematomas or hemorrhagic polyps. Therefore, laryngologists strongly caution pregnant performers against forcing their upper register to meet pre-pregnancy standards. Moreover, postural alterations caused by abdominal enlargement alter musculoskeletal support mechanisms and breath management. As a result, vocal stability deteriorates unless performers adapt their technique appropriately. Otolaryngologists should counsel professional voice users to adopt rigorous vocal hygiene and schedule frequent periods of vocal rest. Finally, clinicians can reassure anxious vocalists that these restrictive adaptations usually resolve spontaneously following delivery.
When pregnant patients present with persistent dysphonia, physicians must conduct a methodical clinical assessment. First, clinicians should take a comprehensive history covering gestational age, vocal demands, and reflux symptoms. Furthermore, flexible fiberoptic laryngoscopy allows safe in-office visualization of the vocal folds without posing risks to the fetus. Examination typically identifies bilateral vocal cord edema, erythema, and sluggish mucosal waves. However, clinicians must carefully rule out acute phonotraumatic lesions such as vocal cord hematomas. Because most gestational vocal alterations stem from reversible physiological shifts, conservative management represents the primary treatment strategy. Specifically, physicians should emphasize aggressive systemic hydration, steam inhalation, and behavioral voice therapy. Moreover, practitioners should proactively treat laryngopharyngeal reflux using pregnancy-safe dietary modifications and approved antacids. In addition, speech-language pathologists can instruct patients in resonant voice techniques to reduce laryngeal impact stress. Clinicians must advise against elective phonosurgical procedures until several months postpartum. In most cases, hormonal normalization and fluid clearance after childbirth rapidly restore baseline vocal function. Thus, patient reassurance combined with structured vocal conservation delivers the best clinical outcomes.
Profound hormonal elevations in the third trimester cause significant fluid retention and vocal fold edema. Consequently, the increased vocal fold mass restricts high-frequency vibration, causing a loss of upper singing range and altered vocal timbre. In addition, diaphragmatic elevation by the growing uterus reduces pulmonary capacity and breath support. Therefore, singers experience heightened vocal fatigue and reduced breath control, necessitating conservative vocal pacing until hormonal levels normalize postpartum.
Current clinical evidence indicates that acoustic parameters, including mean fundamental frequency, jitter, and shimmer, generally remain stable during pregnancy and resolve postpartum. Although mucosal edema may cause transient subjective vocal deepening, permanent acoustic shifts rarely occur in uncomplicated pregnancies. However, persistent reflux, chronic throat clearing, or untreated vocal fold hemorrhage can cause lasting structural changes. Therefore, timely evaluation ensures that temporary physiological adaptations do not progress into permanent vocal pathology.
Clinicians should primarily manage gestational dysphonia through conservative strategies, including robust oral hydration, vocal hygiene, and voice rest. Furthermore, physicians should aggressively treat coexisting laryngopharyngeal reflux with lifestyle modifications and pregnancy-safe antacids. In addition, flexible laryngoscopy can safely rule out phonotrauma or vocal fold granulomas without harming the fetus. Clinicians should postpone elective surgical interventions until several months postpartum, as physiological edema and mucosal changes typically resolve following delivery.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A scoping review reveals how pregnancy affects phonation through laryngeal edema and reduced phonation time rather than major acoustic pitch alterations. Learn how to identify, evaluate, and manage vocal symptoms in expectant mothers.
last month

The VOCAL-AHF study reveals that most acute heart failure patients across reduced and non-reduced ejection fraction categories are eligible for in-hospital GDMT initiation. Notably, nearly two-thirds of HFrEF patients qualify for quadruple therapy, while non-reduced EF patients show high eligibility for dual therapy.
Today

Ascertainment bias in cancer case-control studies inflates odds ratios and penetrance estimates when cases are drawn from high-risk clinics. A landmark modeling study demonstrates substantial bias ranging up to 23.72, highlighting the critical need for ascertainment adjustment in genetic risk counseling.
Today
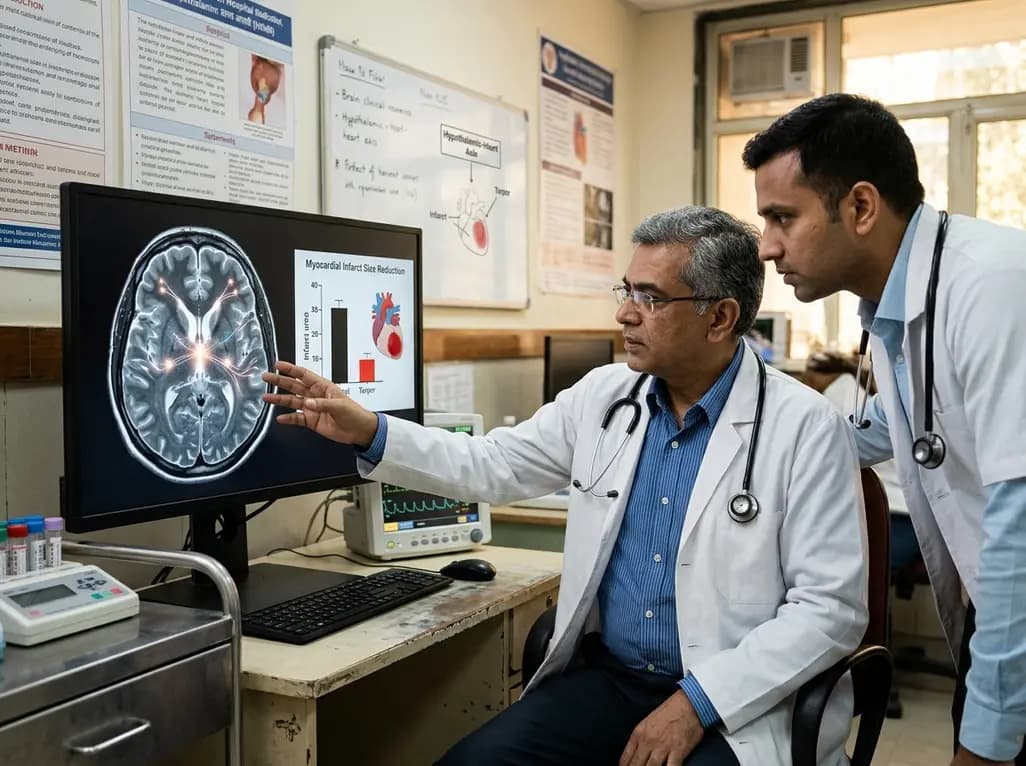
Researchers demonstrate that central induction of synthetic torpor in non-hibernating rats provides striking cardioprotection, reducing myocardial infarct size by ~40% during ischaemia-reperfusion injury through endogenous survival signaling, independent of hypothermia.
Today

A meta-analysis shows that movement representation techniques significantly enhance upper limb and wrist function in distal radius fracture rehabilitation. While effects on pain and grip strength remain inconclusive, early low-cost telerehabilitation and mirror therapy provide promising clinical benefits.
Today
A novel fluorine-functionalized near-infrared copper fluorescent probe selectively illuminates lung tissue, revealing critical links between hyperglycemia, ER stress, and pulmonary malignancy for improved early diagnosis.
Today
