

Loading, please wait...
Loading, please wait...

Major depressive disorder remains a leading contributor to global disability and healthcare burden. Clinicians frequently encounter patients who experience inadequate therapeutic responses to standard antidepressants. Consequently, researchers have sought reliable biological markers to track clinical outcomes. Brain-derived neurotrophic factor plays a pivotal role in neuronal plasticity and survival. Therefore, tracking peripheral BDNF changes has emerged as an attractive candidate during neuromodulation therapy. Interventional brain stimulation techniques provide vital relief for severe and treatment-resistant mood disorders. Understanding their underlying biological mechanisms helps optimize patient care. However, the exact relationship between peripheral growth factors and clinical recovery remains controversial.
The neurotrophic hypothesis suggests that major depression involves impaired neuroplasticity and blunted hippocampal neurogenesis. Brain-derived neurotrophic factor maintains synaptic connectivity and cellular resilience in affective brain circuits. In depressed patients, circulating concentrations of this protein often fall below healthy baseline ranges. Clinicians hypothesized that effective therapeutic interventions restore these neurotrophic levels to promote emotional recovery. Consequently, investigators examine neurotrophin fluctuations following electroconvulsive therapy and repetitive transcranial magnetic stimulation. Both therapeutic modalities stimulate neuroplastic adaptations across frontolimbic pathways. Furthermore, researchers regularly quantify these molecular responses in serum and plasma samples. However, empirical studies show complex and divergent patterns between biomarker shifts and mood improvements. While certain patients display post-treatment biomarker increases, others achieve sustained remission without any measurable shifts. Therefore, peripheral neurotrophin changes do not reliably reflect central neuroplastic reorganization. Understanding this biological gap allows clinicians to critically appraise translational psychiatry literature.
Electroconvulsive therapy remains an extraordinarily effective intervention for severe, psychotic, and treatment-resistant depressive illness. The procedure safely delivers controlled electrical currents under general anesthesia to induce generalized therapeutic seizures. Multiple clinical trials report significant increases in circulating neurotrophin concentrations following electroconvulsive treatment courses. Specifically, serum protein levels tend to rise after repeated generalized seizure inductions. Animal experiments similarly demonstrate robust seizure-induced neurogenesis within the hippocampal dentate gyrus. Nevertheless, systematic evidence reveals striking inconsistencies across published human investigations. Several well-designed clinical studies failed to observe any significant neurotrophin rise despite excellent clinical remission. In addition, some patient cohorts sustained rapid mood improvements while peripheral biomarkers remained flat. Blood collection procedures may also activate platelets, artificially inflating serum values during sampling. Consequently, circulating neurotrophin concentrations do not reliably distinguish treatment responders from non-responders. Electroconvulsive therapy continues to demonstrate unmatched efficacy in urgent psychiatric crises across diverse healthcare settings.
Repetitive transcranial magnetic stimulation provides an established non-invasive neuromodulatory treatment for depression. The technique applies pulsed magnetic fields over the dorsolateral prefrontal cortex without requiring anesthesia. Clinicians frequently offer this outpatient therapy to patients who fail conventional psychopharmacology. High-frequency stimulation typically increases cortical excitability and enhances synaptic neuroplasticity within target circuits. However, current clinical literature demonstrates inconsistent peripheral neurotrophin responses following magnetic stimulation protocols. Several prospective trials showed no significant growth factor alterations despite substantial depressive symptom relief. Furthermore, existing studies utilize widely divergent stimulation intensities, coil designs, and pulse frequencies. Standard ten-hertz protocols and modern theta-burst regimens produce varying biological effects across patient cohorts. Consequently, systematic evidence fails to establish a dependable association between molecular changes and clinical response. Most clinical responders achieve remissions without showing parallel shifts in circulating neurotrophins. Clinicians value this non-invasive approach for its favorable cognitive profile and high patient acceptability.
Profound methodological heterogeneity across clinical trials explains the conflicting results in the psychiatric literature. Investigators frequently analyze disparate biological matrices, including serum and platelet-poor plasma. Platelets sequester the majority of circulating neurotrophins, releasing variable quantities during clotting processes. Consequently, differences in centrifugation speeds, clotting duration, and storage temperatures produce massive laboratory variations. In addition, commercial enzyme-linked immunosorbent assay kits exhibit variable analytical sensitivity and antibody specificity. Many standard commercial assays fail to distinguish precursor pro-neurotrophins from mature, biologically active molecules. This distinction is critical because pro-forms promote apoptotic pathways, whereas mature proteins facilitate neuroplasticity. Moreover, phlebotomy timing differs dramatically across published study designs. Some researchers draw blood immediately after stimulation, while others collect samples weeks later. Baseline patient characteristics, such as age, concurrent psychotropics, and metabolic health, further complicate laboratory interpretations. Establishing reproducible laboratory benchmarks will remain critical for translating neurotrophic research into routine diagnostics.
These systematic findings carry immediate practical significance for psychiatrists and mental health practitioners. Clinicians should not order peripheral neurotrophin tests to make therapeutic decisions or track recovery. Currently, no regulatory organization approves circulating growth factors for diagnostic or monitoring purposes in mood disorders. Instead, doctors must rely on validated clinical scales, including the Hamilton Depression Rating Scale. Serial psychometric evaluations remain the most dependable and cost-effective method to judge treatment efficacy. Furthermore, clinical teams can reassure patients that meaningful recovery occurs independently of blood marker changes. Looking ahead, future biomarker investigations must establish standardized pre-analytical blood handling protocols. Researchers should implement advanced assays capable of quantifying mature neurotrophic proteins selectively. Additionally, combining peripheral molecular markers with functional neuroimaging and electrophysiological testing may yield superior predictive models. Large prospective cohorts will help clarify whether specific patient subgroups exhibit distinct neurobiological trajectories. Until then, comprehensive clinical evaluation remains the true gold standard in psychiatric care.
Clinicians should not use circulating neurotrophin measurements to guide therapeutic selections in depression. Current clinical evidence shows inconsistent correlations between blood concentrations and clinical response following brain stimulation therapies. Additionally, standard blood assays lack validation as diagnostic or prognostic markers in routine psychiatric practice. Therefore, psychiatrists must rely on standardized clinical evaluations, symptom severity assessments, and patient history when selecting between pharmacological, psychological, or interventional treatments.
Serum and plasma measurements diverge largely due to platelet physiology. Platelets store roughly ninety percent of all circulating neurotrophic factors and release them into serum during blood clotting. Consequently, clotting time, ambient temperature, and centrifugation parameters drastically alter serum values across laboratories. Plasma samples reflect free circulating molecules but remain technically difficult to isolate without accidental platelet activation. Thus, biological matrix discrepancies create major variations across published clinical psychiatric trials.
Electroconvulsive therapy triggers generalized cerebral seizures that stimulate robust neurogenesis, frequently producing observable increases in circulating neurotrophin levels across clinical cohorts. In contrast, repetitive transcranial magnetic stimulation delivers focal cortical stimulation without seizure induction, resulting in less consistent peripheral biomarker shifts. However, clinical symptom improvements occur independently of biomarker fluctuations in both modalities. Consequently, neither modality demonstrates a reliable, reproducible correlation between circulating growth factor elevations and long-term remission.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A systematic review evaluates peripheral BDNF changes following ECT and rTMS in major depressive disorder. Findings reveal that circulating neurotrophin fluctuations do not consistently parallel clinical response, highlighting that peripheral BDNF cannot yet serve as a standalone biomarker in psychiatric practice.
Today

The PHASE framework conceptualizes cancer biology through five interacting processes: Pliability, Hybridity, Aggressivity, Sociability, and Evolutivity. This regulatory circuit offers a systems-level perspective on tumor heterogeneity, disease progression, and interaction-guided therapeutic strategies.
Today

Maternal cardiovascular risk factors such as hypertension, obesity, and diabetes significantly elevate offspring cardiovascular disease risk through placental dysfunction and fetal programming. Enhancing preconception screening and antenatal care offers clinicians a powerful strategy to protect long-term heart health.
Today
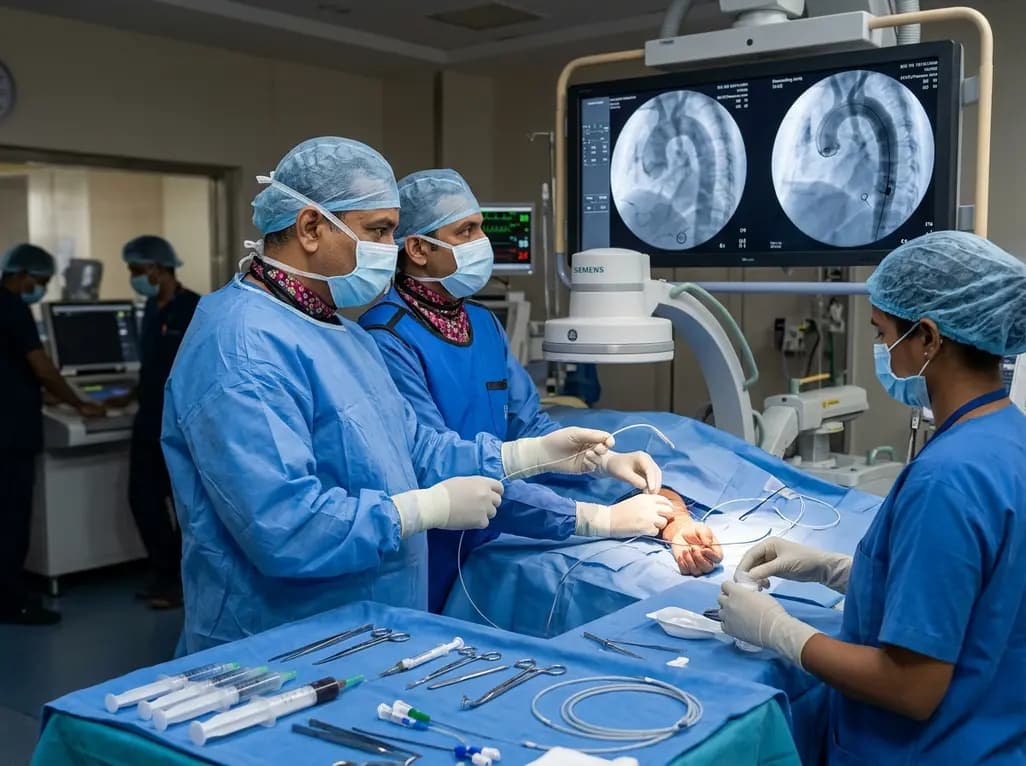
The novel CAST technique utilizes the indwelling Safari XS guidewire as a tracking rail to reposition a radial pigtail catheter into the descending aorta during minimalist TAVI, overcoming challenging vascular anatomy without requiring secondary femoral access or specialized equipment.
Today

A retrospective cohort study reveals that lumbar spine bone mineral density does not distinguish extremity long bone fracture status in adults with severe motor and intellectual disabilities. Because age drove fracture risk rather than spinal density, clinicians must adopt comprehensive assessment tools.
Yesterday

A case report details how reusing single-use insulin cartridges caused device failure and diabetic ketoacidosis in a type 1 diabetes patient using an advanced hybrid closed-loop system. The report highlights technological blindspots, mechanical degradation, and safety protocols during supply shortages.
Today
