

Loading, please wait...
Loading, please wait...
Managing pediatric drug-resistant epilepsy presents considerable clinical challenges when surgical resection poses substantial functional risks. Consequently, pediatric responsive neurostimulation has emerged as an innovative closed-loop therapeutic modality for children and adolescents facing intractable seizures. While adult trials demonstrate convincing clinical efficacy and manageable safety, pediatric safety outcomes require dedicated systematic evaluation. Clinicians must thoroughly evaluate procedural complication risks before recommending invasive intracranial neuromodulation in vulnerable pediatric populations.
Responsive neurostimulation delivers direct, closed-loop electrical pulses to epileptogenic cortex immediately upon detecting abnormal electrographic seizure activity. Although regulatory authorities initially approved this neuromodulation system for adult patients with focal refractory epilepsy, pediatric neurosurgeons and epileptologists increasingly utilize the device off-label. Many pediatric patients have seizure onset zones situated directly within eloquent cortex or distributed across bilateral hemispheric networks. In such challenging clinical scenarios, traditional surgical resections or functional hemispherectomies carry unacceptable risks of causing permanent motor, sensory, or speech impairments. Therefore, intracranial closed-loop neuromodulation offers an invaluable tissue-sparing alternative for preserving neurodevelopmental potential.
Furthermore, closed-loop neurostimulators continuously sample and store chronic intracranial electrocorticography data. This capability provides treating neurologists with unprecedented objective insights into seizure frequency, diurnal patterns, and electrographic responses to medication adjustments. However, pediatric cranial anatomy introduces distinct technical hurdles during device implantation. Younger pediatric patients have thinner cranial vaults and dynamic skull growth, which complicates standard cranial recessed generator placement. Consequently, pediatric surgical teams often adapt technical approaches, utilizing customized cranial contouring or subgaleal placement strategies. Because these anatomic considerations can influence surgical morbidity, meticulous appraisal of adverse events remains essential for clinical decision-making.
To define the surgical safety profile of closed-loop neurostimulation in young populations, researchers conducted a comprehensive PRISMA-guided systematic review and meta-analysis. The investigators searched major biomedical databases, including PubMed, Embase, Web of Science, and the Cochrane Library, from their inception through August 2025. Specifically, the review encompassed observational studies and clinical series reporting surgical outcomes in patients aged 21 years or younger at implantation. Two independent reviewers rigorously screened candidate articles, extracted clinical data, and evaluated potential methodological bias.
The systematic screening identified thirty-five eligible clinical studies, representing an aggregate cohort of 358 pediatric and young adult patients who received responsive neurostimulation. Retrospective case series constituted the majority of published literature at 62.9%, followed by individual case reports at 25.7% and prospective cohort studies at 11.4%. Notably, every included investigation originated from comprehensive tertiary epilepsy centers located within the United States. Across all reporting cohorts, the mean patient age at surgical implantation was 14.8 years, and the mean duration of postoperative clinical follow-up was 20.3 months. Because published experience remains concentrated in high-volume American centers, these findings underscore both rapid technical adoption and the ongoing need for broader geographic data.
The primary outcome of the meta-analysis focused on the proportion of pediatric patients experiencing at least one postoperative complication. Across the cumulative cohort of 358 patients, thirty-eight individuals experienced at least one adverse event during the postoperative observation period. Utilizing a random-effects meta-analytic model, the investigators calculated a pooled overall complication proportion of 10.3%, with a 95% confidence interval ranging from 7.0% to 14.9%. Remarkably, statistical heterogeneity across the included studies was absent, demonstrating an inconsistency index of zero percent. This remarkable statistical consistency enhances confidence in the overall safety estimate across varied surgical institutions.
Moreover, the investigators performed a preplanned sensitivity analysis restricted exclusively to pediatric patients aged 18 years or younger. This pediatric sub-cohort encompassed thirty-one distinct studies comprising 203 patients. In this younger population, the pooled complication proportion was 8.0%, with a 95% confidence interval spanning 4.0% to 16.0%. Importantly, these adverse event rates align closely with complication rates historically reported for pediatric vagus nerve stimulation and deep brain stimulation. Consequently, the procedural safety profile appears favorable and manageable when skilled multidisciplinary teams perform the implantation.
A granular examination of specific complications provides indispensable guidance for pre-surgical family discussions and clinical risk mitigation. Among the documented adverse events, surgical site and hardware infections occurred most frequently, affecting 3.4% of patients. Additionally, transient neurological deficits arose in 3.1% of cases, though these symptoms typically resolved promptly with supportive medical management or stimulation adjustments. Unplanned returns to the operating room occurred in 2.2% of patients, while complete hardware explantation was necessary in 2.0% of individuals due to recalcitrant infection or mechanical failure.
Furthermore, less common complications included stimulation-induced sensations or neuropsychiatric symptoms in 1.4% of patients and cerebrospinal fluid collections or leaks in 1.1%. Mechanical device malfunction and wound dehiscence each occurred in 0.6% of treated patients. Most infectious episodes necessitated antibiotic therapy combined with surgical revision or staged hardware replacement. Similarly, careful surgical flap design and multilayer closure help prevent skin breakdown over the cranial device. Treating neurologists can routinely manage stimulation-induced symptoms by non-invasively altering detection parameters, stimulation amplitudes, and pulse widths during standard outpatient follow-up.
These pooled findings offer valuable reassurance for pediatric neurologists, neurosurgeons, and families navigating difficult treatment decisions for intractable epilepsy. When surgical resection is precluded due to eloquent cortex involvement, responsive neurostimulation delivers meaningful seizure control alongside an acceptable procedural safety profile. Nevertheless, clinicians must interpret these results within the context of several inherent evidentiary limitations. The existing medical literature consists primarily of retrospective, single-center observational reports characterized by variable complication definitions and moderate risk of reporting bias.
Therefore, the international pediatric neurology community must establish prospective, multicenter patient registries with standardized adverse event reporting criteria. Prospective longitudinal registries will provide crucial insights into long-term battery longevity, hardware survival across adolescent cranial growth, and objective neuropsychological outcomes. For developing healthcare ecosystems, including tertiary epilepsy centers in India, adopting responsive neurostimulation requires substantial investment in intracranial monitoring infrastructure and multidisciplinary epilepsy teams. By establishing rigorous clinical selection protocols and standardized postoperative care pathways, specialized centers can safely implement responsive neurostimulation to enhance developmental outcomes in medically intractable pediatric epilepsy.
Responsive neurostimulation provides closed-loop electrical therapy delivered directly to identified epileptogenic foci when abnormal electrocorticographic patterns appear. In contrast, vagus nerve stimulation delivers extracranial, open-loop stimulation to the left cervical vagus nerve on a predetermined duty cycle. Consequently, responsive stimulation records continuous intracranial brain activity, enabling clinicians to tailor therapy to patient-specific neural electrophysiology while avoiding systemic adverse effects.
The most common complications observed in pediatric cohorts include surgical site infections and transient neurological deficits. In addition, small subsets of patients require surgical reoperation or device explantation due to wound breakdown, infection, or lead repositioning. Less frequent adverse events involve cerebrospinal fluid leaks, stimulation-related side effects, and minor hardware malfunctions. Fortunately, permanent neurological deficits remain exceptionally rare across published pediatric series.
Regulatory authorities such as the United States Food and Drug Administration originally approved responsive neurostimulation for adults aged eighteen and older. Therefore, its clinical application in pediatric patients remains largely off-label. Nevertheless, specialized pediatric epilepsy centers increasingly utilize this technology for refractory focal epilepsy when surgical resection carries prohibitive functional risks, supported by growing institutional safety and efficacy evidence.
Disclaimer: This content is for informational and educational purposes only. It is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A systematic review and meta-analysis of 358 pediatric patients shows that responsive neurostimulation for drug-resistant epilepsy has a pooled complication rate of 10.3%, primarily comprising infections and transient deficits, supporting its safety as an off-label therapeutic option.
Today
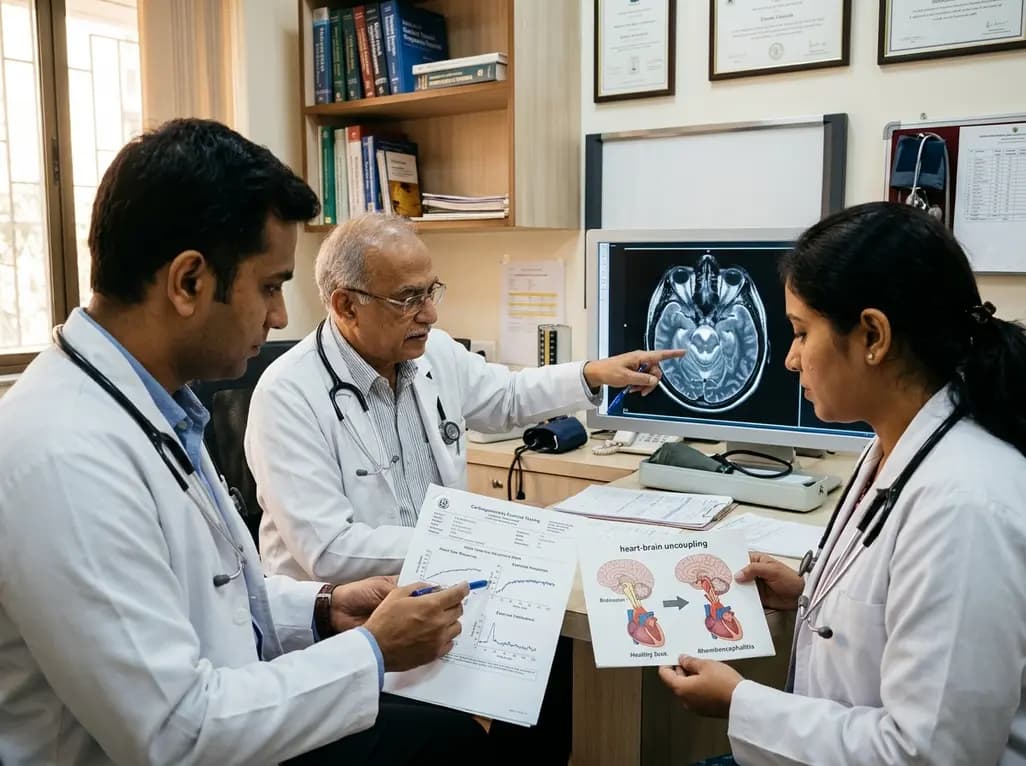
Central chronotropic incompetence is an underrecognized sequela of rhombencephalitis causing exertional dyspnea despite normal resting cardiac function. Cardiopulmonary exercise testing unmasks this heart-brain uncoupling, guiding rate-responsive pacing and targeted rehabilitation.
Today

A landmark study reveals that lipid-rich malignant ascites alters the T-cell metabolic transcriptome, causing cholesterol efflux and impaired fatty acid oxidation. This suppresses TCR signalling and blocks BiTE immunotherapy, while lipid depletion restores antitumour cytotoxicity in ovarian cancer.
Today
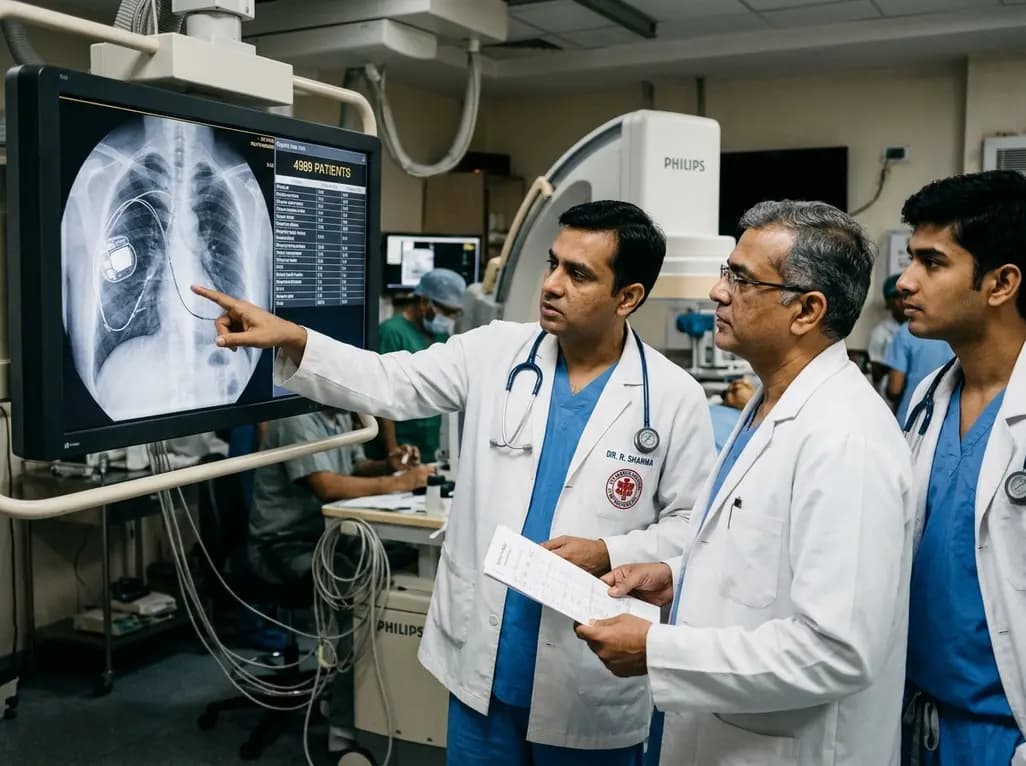
A registry study of 4,989 patients evaluates transvenous lead extraction for right-sided cardiac devices. Despite longer dwell times and older leads, right-sided extractions achieve high procedural success and comparable safety to left-sided approaches.
Today

Recent crash analyses demonstrate significant variations in traffic injury severity across vehicle seating positions. Electric vehicle passengers face disproportionately higher trauma risks than drivers, particularly during airbag deployments, demanding adapted emergency assessment and clinical vigilance.
Today

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
