

Loading, please wait...
Loading, please wait...

Pediatric rheumatologists frequently observe that childhood-onset systemic lupus erythematosus exhibits substantial clinical heterogeneity. Consequently, researchers have intensified efforts to understand how social determinants of health influence pediatric lupus outcomes. Historically, non-medical factors such as racial background, household income, and neighborhood disadvantage correlated with severe lupus nephritis and higher overall disease activity. Furthermore, these adverse social determinants often prevent young patients from reaching the low lupus disease activity state. Nevertheless, clinicians previously lacked robust evidence regarding whether these same disparities directly worsen patient-reported outcomes over time. To address this critical knowledge gap, investigators analyzed longitudinal data from the Childhood Arthritis and Rheumatology Research Alliance Registry. This comprehensive multicenter network captures demographic information, clinical trajectories, and patient-centered metrics across North America. Specifically, the study evaluated whether area-level deprivation, race, and health insurance status negatively impacted functional capacity and subjective well-being. By focusing directly on self-reported and parent-reported instruments, the researchers sought to illuminate the lived experience of pediatric lupus. Ultimately, identifying non-biological drivers of disability empowers clinicians to design targeted supportive interventions for high-risk children.
The investigators conducted a robust cohort analysis examining 540 children diagnosed with childhood-onset systemic lupus erythematosus enrolled in the CARRA Registry. Researchers evaluated key social determinants of health, including self-reported race and ethnicity, insurance coverage type, and the Area Deprivation Index. The Area Deprivation Index integrates multiple socioeconomic metrics, such as regional poverty levels, housing conditions, and parental education status. Additionally, the team tracked two primary patient-reported outcomes across longitudinal follow-up visits. First, they measured functional disability using the Childhood Health Assessment Questionnaire, defining impairment as any score above zero. Second, they evaluated general health status using the Patient-Reported Outcomes Measurement Information System Global Health-7 instrument. To assess these complex relationships accurately, statisticians performed multivariable regression models. Moreover, the analytic models carefully adjusted for important confounders, including patient age, sex, baseline disease activity, and cumulative organ damage. Registry personnel systematically collected standardized data at initial enrollment and subsequent clinical encounters. Therefore, this methodological design provided sufficient statistical power to detect independent associations between environmental deprivation and patient-reported impairment.
The initial findings revealed a striking burden of chronic physical and emotional impairment across the entire pediatric lupus cohort. Specifically, 86 percent of the 540 participating children completed the functional assessment questionnaire at enrollment. Among these youth, approximately 46 percent reported baseline functional disability, demonstrating that physical limitations remain widespread. Moreover, 74 percent of eligible participants successfully completed the baseline Global Health-7 survey. The median Global Health T-score stood at 38.8, which falls more than one standard deviation below normative population averages. Consequently, young patients experience substantial detriments in vitality, emotional resilience, and general physical functioning early in their disease course. In addition, persistent joint discomfort, chronic fatigue, and cognitive dysfunction frequently undermine academic performance and social engagement. Although modern therapeutic regimens have substantially lowered lupus-related mortality, these survey results emphasize that functional morbidity remains unacceptably common. Therefore, treating physicians must recognize that biological remission does not automatically restore normal daily functioning. Comprehensive pediatric care requires active screening for physical restrictions, psychosocial stress, and diminished self-efficacy during regular clinic visits.
Interestingly, the multivariable regression analyses yielded unexpected results regarding the influence of external social factors. Neither race, ethnicity, public insurance coverage, nor neighborhood deprivation scores demonstrated statistically significant associations with longitudinal functional disability. Similarly, these social variables did not predict lower overall health scores on multivariable assessment across follow-up. Thus, these findings contrast sharply with prior studies linking neighborhood poverty to biological lupus nephritis flares and corticosteroid exposure. However, clinicians must interpret these results with thoughtful nuance rather than dismissing structural inequities. Because all participants received regular care at academic pediatric rheumatology centers, comprehensive subspecialty management may mitigate some adverse effects of poverty. Furthermore, standardized access to multidisciplinary teams, clinical coordinators, and aggressive immunosuppressive protocols may partially shield patients from socioeconomic disadvantages. In addition, the universal burden of systemic inflammation and treatment toxicity might simply exert a far greater influence on daily physical function than postal code metrics. Consequently, medical therapy and individualized patient support remain vital determinants of physical rehabilitation.
Although social deprivation did not directly predict disability scores, the researchers uncovered another critical disparity within the data. Specifically, completion rates for the global health questionnaire differed significantly across diverse racial and ethnic groups. Minority children completed longitudinal patient-reported outcome measures less consistently than their White peers throughout the study period. Consequently, non-random missing data may introduce subtle selection bias and mask underlying health inequities in observational cohorts. In addition, language barriers, limited digital access, low health literacy, and time constraints often prevent underprivileged families from completing detailed surveys. When marginalized populations face barriers to questionnaire completion, health systems risk overlooking their unique symptom burdens and treatment-related challenges. Therefore, healthcare teams must actively eliminate administrative friction to ensure representative patient feedback across all clinical settings. For example, clinics can implement multilingual surveys, integrate digital tools into routine waiting rooms, and provide dedicated staff support. Ultimately, achieving equitable healthcare delivery requires measuring patient outcomes systematically across every demographic stratum.
These registry findings hold profound clinical relevance for rheumatologists and pediatricians managing pediatric lupus across India. In Indian healthcare settings, children with systemic lupus face substantial challenges, including delayed diagnoses, limited public insurance, and out-of-pocket medication expenses. Moreover, intense socioeconomic strain frequently impedes clinic attendance, adherence to immunosuppressive drugs, and laboratory monitoring. Consequently, Indian clinicians must integrate formal functional assessments, such as the Childhood Health Assessment Questionnaire, into regular outpatient workflows. Relying solely on laboratory biomarkers like complement levels or proteinuria often obscures severe fatigue and emotional distress. Furthermore, Indian centers must develop culturally tailored, linguistically accessible patient-reported outcome tools to ensure complete participation. By tracking patient-reported outcomes alongside biological disease activity, clinicians can identify unaddressed functional limitations and mental health burdens early. Additionally, dedicated social workers and patient navigators can connect vulnerable families with charitable medication programs and educational resources. Thus, combining aggressive disease control with patient-centered holistic care represents the best pathway to maximize long-term vitality for young patients.
Functional disability occurs frequently in pediatric lupus cohorts. In the CARRA registry investigation, approximately 46 percent of pediatric lupus patients exhibited functional disability at enrollment. Furthermore, their median global health score remained significantly below general population averages. Therefore, clinicians must routinely assess daily physical function, pain interference, and school attendance alongside standard inflammatory markers to detect hidden physical limitations and provide timely rehabilitative support.
Surprisingly, neither racial background, insurance status, nor neighborhood deprivation scores showed significant associations with functional disability or overall health scores across follow-up. While neighborhood poverty frequently correlates with biological organ damage and lupus flares, subspecialty rheumatology care may help buffer these effects. Consequently, high disease activity and medication side effects appear to drive functional impairment more directly than socioeconomic variables in this cohort.
Completion rates for patient-reported outcome surveys varied significantly by race and ethnicity, highlighting systematic engagement barriers. Underprivileged families often encounter substantial obstacles, including language differences, limited digital connectivity, low health literacy, and strict work schedules. Consequently, these logistical barriers hinder consistent survey completion during clinic appointments. Healthcare systems must therefore implement multilingual, accessible assessment tools to capture symptom burdens equitably across all patient populations.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Soulsby WD et al. The impact of non-medical determinants of health on patient-reported outcomes in pediatric lupus: A CARRA registry study. Lupus. 2026 Oct 15. doi: 10.1177/09612033261498255. PMID: 42876432.
Borgia RE, et al. Race, ethnicity and patient-reported outcomes in childhood-onset systemic lupus erythematosus. Clin Exp Rheumatol. 2023;41(4):948-956.
Chang JC, et al. Racial Disparities and Achievement of the Low Lupus Disease Activity State: A CARRA Registry Study. Arthritis Care Res (Hoboken). 2024;76(7):982-991.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A CARRA Registry study evaluated non-medical determinants in 540 children with cSLE. While functional disability was high and quality of life reduced, race, insurance, and area deprivation index were not linked to CHAQ or PROMIS outcomes, though survey completion rates varied.
Today

Novel biomimetic flexible polypyrrole sensors integrate mechanical hemodynamics with exhaled ammonia detection, offering noninvasive monitoring for chronic kidney disease and remote clinical care.
Today

Maharashtra has initiated the appointment of two dedicated special public prosecutors in every district alongside a joint police-health SOP to fast-track PCPNDT and MTP cases. Medical imaging centers, radiologists, and obstetricians must strengthen statutory documentation and audit preparedness.
Today
A prospective study evaluates percutaneous renal denervation in high-risk patients with resistant hypertension, demonstrating significant short-term blood pressure reduction alongside notable procedural considerations.
Today
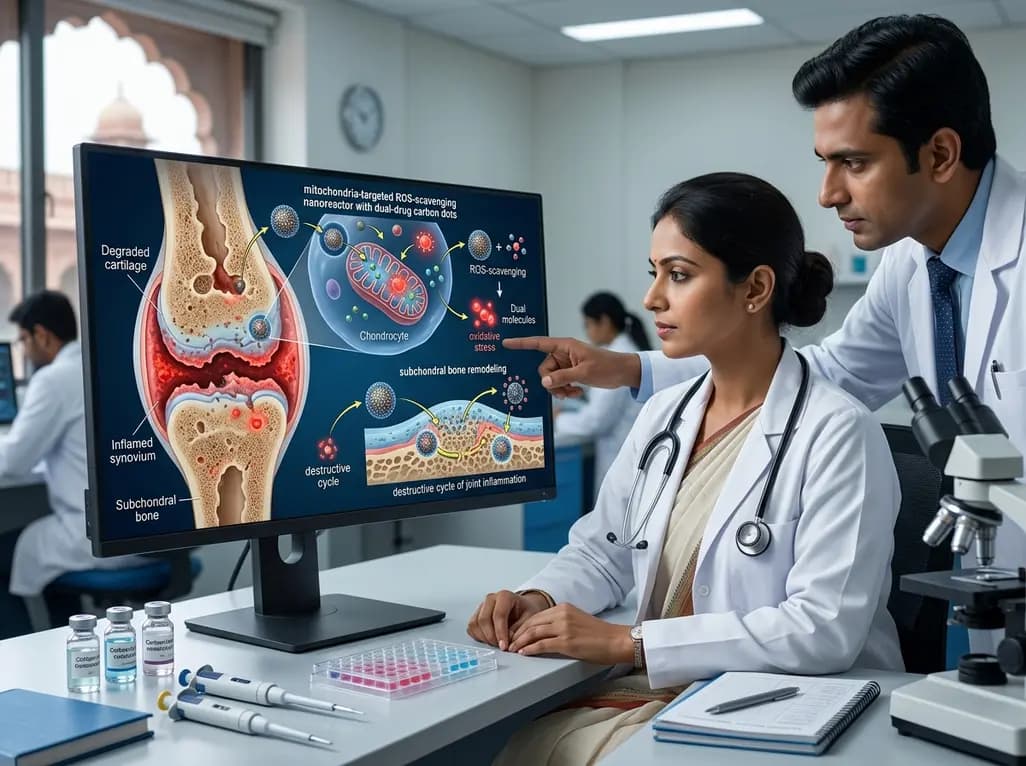
A novel mitochondria-targeted ROS-scavenging nanoreactor with dual-drug carbon dots provides a multi-mechanism strategy for osteoarthritis therapy. By neutralizing oxidative stress and remodeling subchondral bone, this platform breaks the destructive cycle of chronic joint inflammation and cartilage degeneration.
Today

A modified Delphi study identified crucial clinical and research priorities for older transgender adults. Key findings emphasize provider education, screening for social isolation, navigation of community resources, and long-term evaluation of gender-affirming hormone therapy safety during the aging process.
Today
