

Loading, please wait...
Loading, please wait...
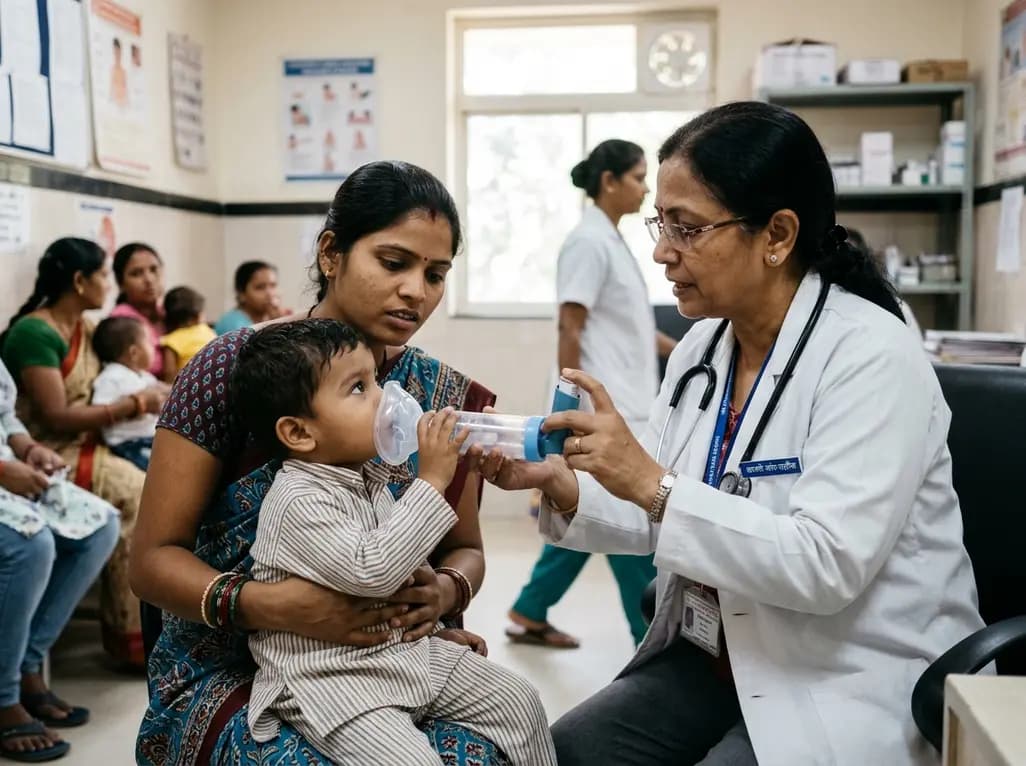
Administering inhaled medications to young children represents a persistent clinical challenge in asthma management. Most pediatric protocols rely on pressurized metered-dose inhalers paired with valved holding chambers and face masks. However, therapeutic success requires precise technique. Caregivers must maintain an airtight facial seal, coordinate actuation, observe correct device orientation, and ensure effective tidal breathing. Unfortunately, parents cannot easily assess these subtle physical parameters during daily administration. This invisible margin of error frequently leads to silent drug under-delivery and sub-optimal symptom control. Introducing reliable pediatric inhaler feedback addresses this gap directly by evaluating crucial handling variables at the point of care. Real-time digital sensing provides immediate objective verification, which reassures caregivers and safeguards drug delivery.
Recent research from the University of Calgary underscores the emotional and practical difficulties families experience during inhalation therapy. In semistructured concept-elicitation sessions involving 27 caregivers, persistent uncertainty emerged as the dominant lived experience. Nearly three-quarters of participants reported chronic doubts regarding whether their child inhaled the full medication dose. Current passive visual indicators, such as chamber flutter valves, often fail to provide definitive clarity. Consequently, caregivers overwhelmingly supported digital concepts that offer direct confirmation. Real-time pediatric inhaler feedback bridges the divide between parental intention and therapeutic success. By capturing subtle flow and seal dynamics, connected sensing tools turn invisible delivery mechanics into clear, actionable clinical signals.
Although caregivers enthusiastically welcome digital assistance, their support remains strictly conditional on system accuracy. In the qualitative evaluation, parents identified false reassurance as a catastrophic failure mode. A premature green light or positive chime when an improper seal exists can deceive parents into withholding necessary rescue doses. Therefore, systems must not classify poor drug delivery as successful administration. To address this risk, researchers proposed a robust three-tier data evaluation architecture. This framework separates sensor inputs from the user interface through an intermediate data-quality gate. When sensor signals remain indeterminate, the device displays an explicit uncertain state rather than guessing. This conservative approach preserves parental vigilance and prevents dangerous therapeutic oversights.
Pediatric respiratory emergencies require rapid, instinctive action without technological interference. During acute bronchospasms, caregivers manage distressed children under immense emotional stress. Consequently, study participants emphasized that connected inhalers must deliver immediate on-device feedback independently of mobile phone applications. Fumbling with smartphone pairing, software updates, or touchscreens during an acute asthma attack introduces hazardous delays. Clip-on sensor attachments must maintain a lightweight form factor and preserve standard inhaler ergonomics. Furthermore, bulky add-ons that alter actuation resistance or disrupt mask contour can compromise drug delivery. Connected devices must streamline emergency drug delivery rather than complicate it, ensuring seamless usability during critical events.
Beyond acute crisis management, connected health platforms offer valuable opportunities for ongoing respiratory education. Caregivers expressed varied preferences regarding gamification, longitudinal dashboards, and data sharing. While older children often benefit from interactive breathing games, parents frequently prefer clean, analytical interfaces for routine tracking. Therefore, software architects should treat digital engagement modules as configurable secondary features. Routine daily tracking provides invaluable objective adherence data for outpatient follow-up visits. Clinicians can review technique fidelity alongside dispensing records to diagnose therapy failure accurately. When healthcare providers combine real-time physical sensing with tailored educational support, families achieve superior long-term disease management and sustained clinical control.
Real-time sensing monitors essential physical variables during inhalation, including inspiratory flow, mask seal integrity, device orientation, and actuation timing. These parameters are often invisible to the naked eye. By providing immediate sensory confirmation, the device verifies proper technique instantly. This ensures that the aerosolized medication reaches the lower airways effectively rather than depositing in the spacer chamber or oropharynx.
A false positive signal occurs when a device displays a green or successful status despite improper inhalation technique or an incomplete seal. This error provides false reassurance to caregivers, leading them to believe the child received the full dose. In an acute asthma flare, this misconception can dangerously delay essential rescue therapy, increasing the risk of severe exacerbations and emergency hospitalization.
Yes, safety-focused clinical designs prioritize app-independent functionality. While mobile applications offer helpful longitudinal tracking and technique coaching, the primary feedback mechanism must operate directly on the physical device. During acute respiratory distress, caregivers need instant, standalone audiovisual cues without unlocking phones, troubleshooting Bluetooth connections, or waiting for mobile applications to sync.
Disclaimer: This content is for informational and educational purposes only and should not be considered medical advice. Always consult a qualified healthcare provider for diagnosis and treatment recommendations tailored to individual patient needs. Refer to the latest local and national guidelines for clinical practice.
References
Musa N et al. Caregiver-Informed Safety and System Requirements for Real-Time Feedback During Pediatric Inhaler Use: Qualitative Concept-Elicitation Study. J Med Internet Res. 2026 Nov 19. doi: 10.2196/109180. PMID: 43056716.
Gupta RS, Fierstein JL, Boon K, et al. Sensor-based inhaler monitoring for pediatric asthma: A randomized controlled trial. Pediatrics. 2021;147(4):e2020024467.
Global Initiative for Asthma. Global Strategy for Asthma Management and Prevention. 2025 update. Available from: ginasthma.org.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A new qualitative study reveals key caregiver-informed safety requirements for real-time pediatric inhaler feedback. Explore how device design, fail-safe mechanisms, and technique tracking can eliminate parental uncertainty, avoid false reassurance, and improve aerosol medication delivery.
Today

A clinical decision-support framework using health checkup data from 231,683 adults predicts incident obesity with high discrimination (AUROC 0.918). The system integrates temporal survival analysis and risk-factor explanations to prioritize individualized preventive interventions.
Today

A large cohort study demonstrates that fetal growth restriction in a first pregnancy raises maternal cardiovascular risk within five years postpartum, including elevated rates of heart failure, stroke, and myocardial infarction. Clinicians must initiate proactive postpartum screening and cardiovascular prevention.
Yesterday

A multicenter observational study evaluated an 8-week digital health monitoring platform using wearable sensors in ambulatory heart failure. While participants achieved high daily wear-time of 11.7 hours and 80% completion, initial recruitment revealed significant technology-related onboarding barriers.
Today

A paired cadaveric study compared triple and quintuple percutaneous Achilles tendon lengthening. While quintuple hemisection showed numerically greater elongation, differences were not statistically significant.
Yesterday
Diabetic retinopathy remains a leading cause of preventable visual impairment. This review outlines key strategies for screening, systemic risk factor control, advanced diagnostic imaging, and timely specialist referrals within primary and multidisciplinary care models.
Today
