

Loading, please wait...
Loading, please wait...

Venous and arterial thromboembolism represents a major complication in children undergoing complex cardiac interventions or intensive care monitoring. Clinicians frequently prescribe low-molecular-weight heparin, particularly enoxaparin, to manage these life-threatening thrombotic events. However, optimizing pediatric enoxaparin dosing remains an enduring challenge for pediatric intensivists and cardiologists. Neonates and young infants possess distinct developmental physiology that alters drug handling. Consequently, standard guideline doses often fail to achieve target anticoagulation promptly. A recent study investigated enoxaparin requirements in paediatric cardiology patients across distinct age groups. Their findings illuminate significant discrepancies between historical dosing guidelines and the actual requirements of critically ill infants.
Low-molecular-weight heparins exert their anticoagulant effect primarily through antithrombin-dependent inhibition of activated factor Xa. Nevertheless, pediatric enoxaparin dosing cannot mirror adult regimens due to distinct developmental pharmacokinetics. Infants possess a substantially larger total body water volume and extracellular fluid compartment relative to weight. Therefore, hydrophilic molecules like enoxaparin distribute into a vastly larger physiological space. In addition, healthy neonates and infants display higher glomerular filtration rates normalized to surface area after the initial weeks of life. This accelerated renal clearance rapidly eliminates enoxaparin from the bloodstream. Furthermore, physiological developmental hemostasis plays an important role. Infants naturally possess lower baseline plasma concentrations of antithrombin III, which attenuates anticoagulant response. Consequently, administering standard doses results in persistent subtherapeutic anti-factor Xa levels. Clinicians must recognize these physiological differences when managing infants who face thrombotic complications. Without accounting for expanded distribution volumes and rapid excretion, medical teams risk delaying therapeutic anticoagulation during critical post-surgical recovery periods.
The retrospective chart review evaluated 71 patients aged 0 to 18 years admitted to the cardiac intensive care unit or cardiac stepdown unit. All included patients achieved therapeutic anti-factor Xa concentrations between 0.5 and 1.0 units/mL. The investigators stratified the cohort into four distinct age categories: infants 2 months or younger, infants older than 2 to 6 months, infants older than 6 to 12 months, and children older than 12 months. Notably, the study revealed statistically significant differences in median enoxaparin requirements across these age brackets. Patients aged 2 months or younger required a median therapeutic dose of 2.13 mg/kg/dose. Similarly, patients aged 2 to 6 months needed a median dose of 1.81 mg/kg/dose. In contrast, infants aged 6 to 12 months achieved target levels at 1.44 mg/kg/dose. Finally, children older than 12 months required only 1.16 mg/kg/dose. These findings demonstrate an inverse relationship between age and required enoxaparin weight-based dosage, confirming that the youngest cardiac infants demand significantly higher drug exposure.
Achieving rapid therapeutic anticoagulation is crucial for preventing thrombus progression and preserving life-saving vascular access. However, the study uncovered that the gap between initial empiric doses and ultimate therapeutic maintenance doses was significantly wider in younger cohorts. Consequently, patients aged 6 months or younger underwent substantially more frequent dosage adjustments. Furthermore, these infants experienced significantly longer times to achieve therapeutic anti-factor Xa levels compared to older children. This lag occurred despite clinicians initiating therapy at higher baseline doses in the youngest cohorts. Therefore, standard starting recommendations remain inadequate for bridging cardiac infants to rapid therapeutic safety. Each dose titration requires a subsequent waiting period to achieve steady state before laboratory reassessment. During this prolonged titration window, patients remain vulnerable to ongoing clot formation or vascular occlusions. These data highlight that current empiric protocols fail to account for the true magnitude of clearance in critically ill infants, ultimately prolonging the period of subtherapeutic anticoagulation.
Children admitted to cardiac intensive care units carry an elevated baseline risk for thromboembolic disease. Many of these infants have surgically placed systemic-to-pulmonary shunts, central venous access devices, extracorporeal support cannulas, or prosthetic valves. In these fragile hemodynamic settings, an undetected or expanding thrombus can provoke catastrophic graft failure, pulmonary hypoperfusion, or acute stroke. In addition, cardiac surgery often causes systemic inflammation, altered vascular permeability, and fluctuating renal perfusion. These clinical variables further disrupt drug bioavailability and clearance mechanisms. Because standard initial doses leave most infants subtherapeutic, relying on conservative titration schedules places post-operative cardiac infants in jeopardy. Clinical pharmacists and cardiac intensivists must therefore adopt more aggressive, individualized dosing strategies upon treatment initiation. Recognizing that infants younger than 2 months frequently require more than 2 mg/kg per dose enables clinicians to shorten the interval to target anticoagulation. By anticipating higher dose requirements early, care teams can safeguard patency of critical cardiovascular repairs and improve overall patient outcomes.
Because of substantial pharmacokinetic variability, routine laboratory monitoring remains mandatory during pediatric enoxaparin therapy. Clinical teams must measure plasma anti-factor Xa concentrations four hours after subcutaneous administration, typically following the third or fourth dose when steady-state concentration occurs. The widely accepted therapeutic target for active thrombosis treatment ranges between 0.5 and 1.0 units/mL. If the initial post-dose level falls below 0.5 units/mL, clinicians must promptly increase the dosage by 10% to 25% according to validated titration nomograms. However, escalating doses in critically ill infants necessitates vigilant monitoring for potential adverse bleeding events. Care teams should regularly assess hemoglobin, hematocrit, platelet counts, and clinical sites for overt or occult bleeding. Moreover, clinicians must carefully evaluate renal function, because acute kidney injury can impair enoxaparin elimination and cause drug accumulation. Multidisciplinary coordination between pediatric cardiologists, hematologists, and clinical pharmacists ensures that necessary dose escalations achieve therapeutic efficacy without compromising patient safety.
Infants under two months possess an expanded extracellular fluid volume and an increased volume of distribution relative to older individuals. In addition, their rapid renal clearance eliminates low-molecular-weight heparin quickly from the circulation. Furthermore, neonates have lower baseline antithrombin III levels, which limits the drug's co-factor activity. Consequently, these physiological factors necessitate higher milligram-per-kilogram doses to achieve therapeutic anti-factor Xa concentrations between 0.5 and 1.0 units/mL.
Clinicians should draw blood samples to measure anti-factor Xa levels exactly four hours after a subcutaneous enoxaparin injection. This timing captures peak drug activity. Moreover, healthcare teams should obtain the test after the third or fourth consecutive dose to ensure the drug reaches steady-state concentrations. If teams adjust the dosage, they must repeat the anti-factor Xa assay four hours after the subsequent adjusted dose until values remain stable.
Current clinical evidence demonstrates that appropriately titrated enoxaparin escalations do not significantly increase major bleeding complications in neonates. Because infants clear the drug more rapidly and require higher doses to reach identical target anti-factor Xa ranges, higher milligram-per-kilogram doses achieve therapeutic equivalence rather than drug excess. However, clinical teams must continually monitor renal function, coagulation parameters, and physical signs of bleeding to ensure continued patient safety during treatment.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study in pediatric cardiology reveals that infants under two months require median enoxaparin doses of 2.13 mg/kg/dose, alongside more dose titrations and longer times to reach target anti-Xa levels compared to older children, underscoring the need for tailored dosing and aggressive monitoring.
Today
Healthcare resource cutbacks create severe organizational conditions that constrain moral agency, triggering moral distress across frontline clinicians and healthcare leaders. Addressing this crisis requires ethical leadership, relational solidarity, and transparent resource allocation frameworks.
Today

Maharashtra has initiated the appointment of two dedicated special public prosecutors in every district alongside a joint police-health SOP to fast-track PCPNDT and MTP cases. Medical imaging centers, radiologists, and obstetricians must strengthen statutory documentation and audit preparedness.
Today
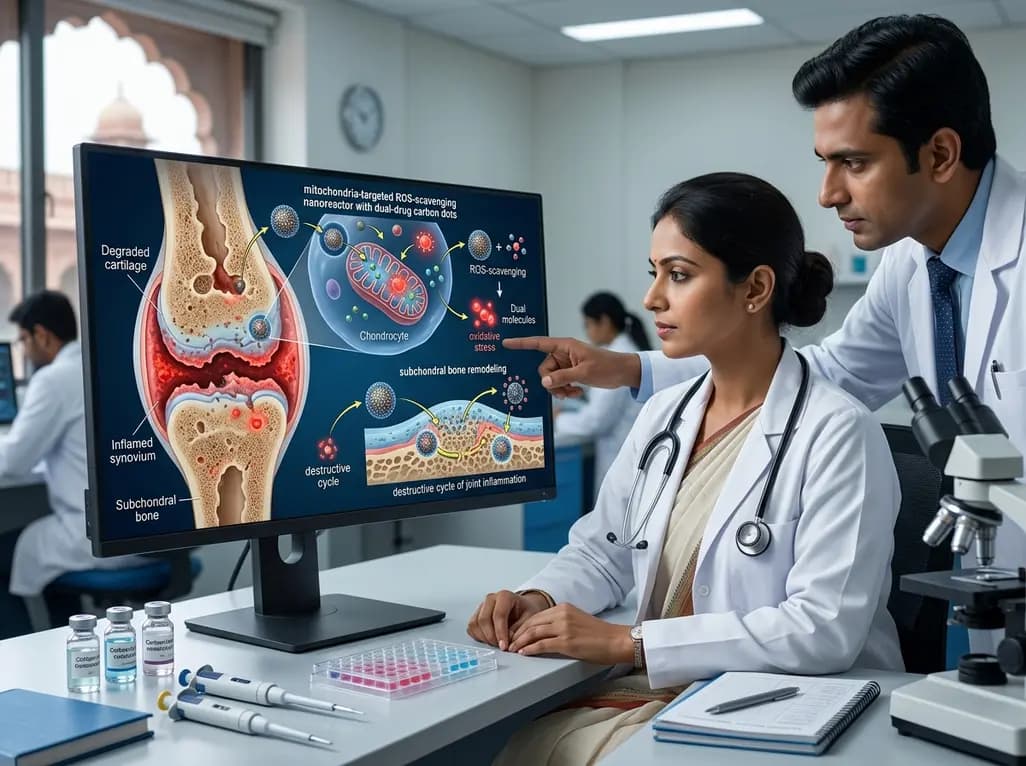
A novel mitochondria-targeted ROS-scavenging nanoreactor with dual-drug carbon dots provides a multi-mechanism strategy for osteoarthritis therapy. By neutralizing oxidative stress and remodeling subchondral bone, this platform breaks the destructive cycle of chronic joint inflammation and cartilage degeneration.
Today

An exploratory pilot study evaluates metoprolol pharmacokinetics across cisgender males, cisgender females, and transgender women on gender-affirming hormone therapy. Findings reveal distinct drug disposition trends, emphasizing the critical need for genotype-stratified research in transgender cardiovascular care.
Today
