

Loading, please wait...
Loading, please wait...

Pancreatic ductal adenocarcinoma remains one of the most lethal oncological challenges worldwide because symptoms rarely manifest during initial tumor growth. However, a revolutionary pancreatic cancer blood test called PANXEON may transform current diagnostic paradigms by identifying early lesions before clinical metastasis occurs. Developed by international researchers, this liquid biopsy combines circulating epigenetic signatures with traditional serological markers to catch asymptomatic malignancies. Consequently, this innovation offers clinicians an unprecedented opportunity to intervene while curative surgical resection remains clinically viable.
Pancreatic cancer currently carries an overall five-year survival rate of only fourteen percent across global registries. Unfortunately, clinicians detect approximately ninety percent of cases after malignant cells have already invaded regional vascular structures or distant organs. This diagnostic delay occurs because early tumors generate non-specific gastrointestinal complaints such as dyspepsia, mild epigastric discomfort, or transient bloating. Therefore, primary care physicians often investigate more benign conditions before suspecting an underlying retroperitoneal neoplasm.
Furthermore, standard abdominal imaging modalities cannot reliably detect microscopic parenchymal abnormalities during routine outpatient assessments. Transabdominal ultrasonography frequently suffers from acoustic interference caused by overlying bowel gas and patient habitus. Computed tomography and magnetic resonance imaging provide superior resolution, but cost and radiation constraints prevent their broad implementation as general screening tools. Additionally, tissue biopsies carry procedural risks like pancreatitis, hemorrhage, and tumor seeding. Thus, clinicians urgently need non-invasive tools to stratify patients at the earliest stages of oncogenesis.
To overcome the sensitivity barriers of single-analyte assays, researchers developed PANXEON as a multimodal diagnostic platform. The panel simultaneously interrogates three distinct molecular compartments within peripheral blood samples. Specifically, the test quantifies five cell-free circulating microRNAs alongside five exosomal microRNAs and the validated protein biomarker CA19-9. Extracellular vesicles protect exosomal microRNAs from enzymatic degradation, thereby preserving highly stable organ-specific molecular fingerprints.
Moreover, single-marker assays like carbohydrate antigen 19-9 show high false-negative rates in Lewis-antigen negative individuals. Similarly, CA19-9 levels elevate non-specifically during benign biliary obstruction and systemic inflammation. However, PANXEON integrates all three biomarker classes into an artificial intelligence algorithm that calculates a singular composite risk score. Consequently, this algorithmic synthesis minimizes background noise while amplifying subtle neoplastic signals. The test therefore represents the first liquid biopsy platform to combine vesicle-bound microRNAs, circulating free non-coding RNAs, and serum glycoproteins.
Researchers rigorously evaluated the liquid biopsy in a large multicenter observational trial published in Nature Medicine. The prospective cohort included 1,785 participants recruited from high-volume academic institutions across the United States, Italy, Japan, and South Korea. Crucially, the diverse cohort incorporated healthy individuals, benign disease controls, and patients with confirmed pancreatic ductal adenocarcinoma. This broad international recruitment confirmed that the assay maintains robust analytical validity across diverse geographic and genetic backgrounds.
Remarkably, the blood panel demonstrated an 86.8 percent sensitivity for detecting stage I and stage II pancreatic malignancies. Furthermore, the test maintained outstanding specificity, showing a low false-positive rate of merely 3.2 percent in standard low-risk control populations. In high-risk cohorts with inflammatory conditions like chronic pancreatitis, the false-positive rate measured 15.6 percent. Notably, serial monitoring in a surgical sub-cohort demonstrated that biomarker levels declined following surgical resection and rose before radiographic recurrence. Thus, the assay may also assist in monitoring post-treatment therapeutic response.
Beyond detecting invasive adenocarcinoma, the assay demonstrated remarkable efficacy in intercepting precancerous pathologies. Specifically, PANXEON identified high-grade dysplasia within high-risk pancreatic mucinous cysts in 64.3 percent of evaluated cases. High-grade dysplasia, often designated as stage zero pancreatic disease, represents the ultimate biological window for curative preventative intervention. Consequently, identifying this cellular transition allows surgical teams to excise premalignant tissue before invasive basement membrane penetration occurs.
Currently, clinicians rely on guidelines such as the Fukuoka or Sendai criteria to manage intraductal papillary mucinous neoplasms. However, conventional imaging parameters often fail to differentiate benign indolent cysts from lesions harboring severe cellular atypia. Consequently, many patients undergo complex pancreaticoduodenectomy procedures unnecessarily, while others experience unexpected malignant progression during watchful waiting. Therefore, adding a liquid biomarker score to cyst surveillance protocols provides objective molecular stratification. As a result, surgical teams can recommend resection with far greater confidence.
Investigators emphasize that the liquid biopsy serves to enrich high-risk screening rather than eliminate cross-sectional imaging. Primary care clinicians and gastroenterologists can deploy the blood panel as an initial triage tool for individuals with elevated lifetime risk. This vulnerable population includes patients carrying germline mutations like BRCA2, CDKN2A, or ATM, as well as individuals with family cancer clusters. Furthermore, older adults presenting with sudden-onset type 2 diabetes or unexplained weight loss could benefit from prompt molecular risk assessment.
Patients who receive an elevated risk score would immediately undergo targeted contrast-enhanced pancreatic protocol imaging and endoscopic ultrasound. Conversely, individuals demonstrating reassuring biomarker profiles can avoid invasive biopsy procedures and repeated radiation exposure. Ultimately, integrating blood-based molecular screening into everyday workflows can truncate the diagnostic interval. Consequently, oncology teams can initiate systemic or surgical therapies while tumors remain localized and operable.
Q1: What biological markers does the PANXEON test measure?
The test evaluates three distinct molecular components from a single peripheral blood sample. Specifically, it quantifies circulating cell-free microRNAs, exosome-encapsulated microRNAs, and the serum protein marker CA19-9. Artificial intelligence algorithms subsequently analyze these combined measurements to generate a unified risk score. This multi-analyte approach captures multiple biological signals, improving overall diagnostic accuracy over conventional single-marker laboratory assays.
Q2: Can this liquid biopsy replace abdominal imaging examinations?
No, the liquid biopsy complements existing diagnostic imaging rather than replacing computed tomography or magnetic resonance scans. Clinicians will utilize the blood assay as an initial non-invasive screening and triage mechanism. Patients who exhibit elevated risk scores will proceed to targeted endoscopic ultrasound and contrast-enhanced imaging. Therefore, this test streamlines clinical workflows by identifying high-risk individuals who require urgent radiological evaluation.
Q3: How does the test assist in managing pancreatic cysts?
The assay successfully identified high-grade dysplasia in 64.3 percent of high-risk pancreatic cysts during clinical evaluations. High-grade dysplasia represents an advanced precancerous state that precedes invasive malignancy. By detecting these cellular alterations early, the blood test helps surgeons determine which cysts require immediate operative removal and which cysts can undergo routine surveillance. Consequently, this prevents unnecessary surgeries while protecting vulnerable patients.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A breakthrough multi-analyte liquid biopsy combining microRNAs and CA19-9 with artificial intelligence shows 87% sensitivity for early-stage pancreatic cancer detection, identifying resectable disease and high-grade dysplasia.
Today

Meghalaya recorded a historic 55% reduction in maternal deaths, dropping from 244 to 107 over five years. Through the MOTHER app, dedicated transit homes, and expanded infrastructure like the 150-bed Tura Maternity Hospital with its first public NICU, the state demonstrates an effective public health model.
Today

Explore modern perioperative management protocols for clinical xenotransplantation. Learn how costimulation blockade, anti-inflammatory perfusion, and coagulopathy rescue overcome interspecies hurdles.
Today
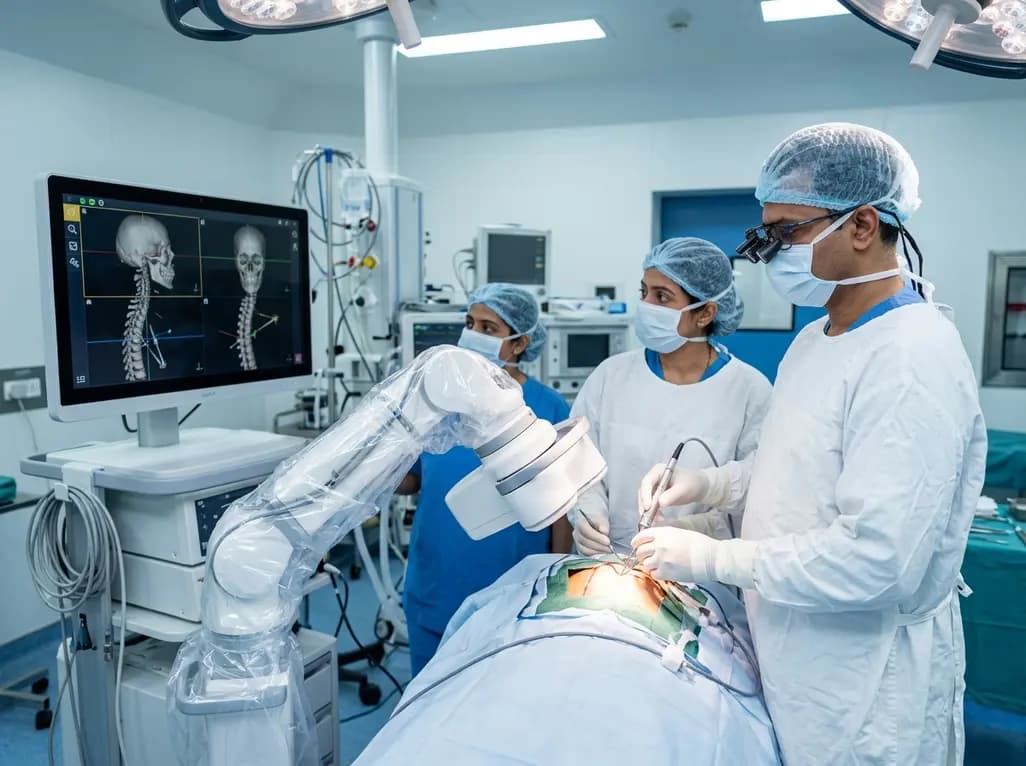
North India's first Centre of Excellence for Brain and Spine at Amrita Hospital Faridabad integrates Brainlab's Loop-X mobile robot. This landmark facility combines cone-beam computed tomography with surgical navigation to elevate precision, optimize operative workflows, and enhance specialized clinician training.
Today

At Homa CME 2026 at Hyderabad's T-Hub, healthcare leaders emphasized moving beyond routine metrics through digital calculators and precision stratification. Discover why characterizing individual insulin secretion, resistance patterns, and vascular risks transforms chronic metabolic care in India.
Today
