

Loading, please wait...
Loading, please wait...

Managing paediatric coeliac disease extends far beyond resolving classical gastrointestinal disturbances and malabsorption. Historically, clinicians focused almost exclusively on intestinal atrophy and delayed physical development. However, modern research identifies chronic autoimmune enteropathy as a systemic vascular concern. Persistent mucosal inflammation disrupts hepatic lipid regulation. Consequently, children with active enteropathy often display reduced high-density lipoprotein cholesterol and elevated atherogenic indices. Therefore, addressing nutritional compliance represents an essential cardiovascular priority. Clinical evidence reveals that strict gluten avoidance restores serum high-density lipoprotein concentrations. Furthermore, unaddressed inflammation promotes early arterial stiffness during key growth phases. Thus, primary care practitioners and gastroenterologists must evaluate cardiometabolic health alongside mucosal healing. In addition, subclinical vascular alterations develop silently without presenting obvious symptoms. Clinicians must actively monitor these surrogate risk parameters. Ultimately, adopting a preventative approach safeguards long-term cardiovascular health in affected children.
A rigorous clinical study evaluated the association between dietary adherence and atherogenic profiles in paediatric coeliac patients. The researchers retrospectively evaluated 149 children aged 3 to 18 years. To ensure accurate classification, clinicians assessed gluten-free diet adherence using clinical findings, serological antibody titres, and patient reports. Specifically, investigators classified 106 participants as diet-adherent and 43 children as diet-nonadherent. In addition, researchers collected comprehensive baseline data, including age, biological sex, and body mass index percentiles. They calculated critical atherogenic indices to quantify early cardiovascular risk accurately. Furthermore, the statistical analysis incorporated multivariable linear regression models. The authors adjusted these regression models for age, sex, and body mass index. Consequently, the study isolated dietary compliance as an independent factor influencing lipid metabolism. Therefore, this methodological approach minimized confounding variables effectively. These findings provide clinicians with clear empirical evidence regarding the metabolic consequences of dietary lapses.
The comparative analysis demonstrated marked differences in lipid parameters based on dietary compliance. Most notably, children who maintained strict adherence to a gluten-free diet exhibited significantly higher high-density lipoprotein cholesterol levels. Adherent children achieved mean high-density lipoprotein concentrations of 55.3 mg/dL, whereas non-adherent children achieved only 46 mg/dL. Moreover, multivariable linear regression confirmed that dietary adherence independently predicted high-density lipoprotein levels after controlling for age, sex, and body mass index. In contrast, non-adherent children displayed significantly worse atherogenic indices. These elevated ratios signal heightened cardiovascular vulnerability and accelerated vascular strain. Furthermore, the favorable lipid changes in adherent patients occurred consistently regardless of baseline weight. Consequently, strict gluten elimination serves a potent cardioprotective role. Thus, dietary adherence directly influences systemic lipid transport beyond simple intestinal symptom resolution. Ultimately, achieving normal high-density lipoprotein levels provides young patients with vital protection against long-term atherosclerosis.
Intricate immunological mechanisms explain how dietary adherence influences circulating lipoproteins. In untreated coeliac enteropathy, dietary gluten triggers persistent small-intestinal mucosal inflammation. Consequently, active mucosal lesions generate high concentrations of pro-inflammatory cytokines, including tumor necrosis factor-alpha and interleukin-6. These circulating inflammatory mediators suppress hepatic apolipoprotein A-I synthesis and disrupt reverse cholesterol transport. Furthermore, widespread villous blunting impairs the absorption of dietary lipids and essential fat-soluble vitamins. Therefore, active inflammation produces lower high-density lipoprotein concentrations alongside unfavorable atherogenic ratios. Conversely, strict gluten avoidance halts immune-mediated mucosal injury. As intestinal enterocytes recover, systemic cytokine levels drop dramatically. Consequently, hepatic apolipoprotein production rebounds, allowing the normal assembly of protective high-density lipoprotein particles. In addition, improved nutrient absorption supports endogenous antioxidant defenses, preventing oxidative lipid modification. Thus, intestinal mucosal healing directly repairs lipid metabolism through coupled immunologic and metabolic pathways.
These metabolic insights necessitate a shift in routine outpatient follow-up protocols. Currently, physicians monitor paediatric coeliac disease primarily through transglutaminase antibodies and growth velocity. However, relying solely on serology may overlook subtle metabolic dysregulation. Children who strictly avoid gluten may still consume commercial gluten-free alternatives packed with saturated fats and simple sugars. Consequently, patients can develop atherogenic dyslipidaemia despite normal antibody titres. Therefore, paediatricians should include fasting lipid profiles in routine periodic reviews. In addition, clinicians must collaborate with specialized paediatric dietitians to assess dietary quality comprehensively. Early identification of low high-density lipoproteins allows for prompt dietary re-education. Furthermore, counseling should promote whole foods, pulses, vegetables, and healthy unsaturated fats over ultra-processed gluten-free snacks. Healthcare teams must also address dietary adherence barriers collaboratively during adolescence. Ultimately, integrating cardiovascular assessments into regular coeliac care establishes a holistic standard of preventative medicine.
Untreated intestinal inflammation severely blunts mucosal absorption of fat-soluble vitamins and dietary lipids in young patients. Furthermore, chronic enteropathy releases circulating inflammatory cytokines that destabilize apolipoprotein synthesis in the liver. Consequently, these systemic cascades depress protective high-density lipoprotein cholesterol concentrations. When paediatric patients adopt strict dietary adherence, systemic inflammation recedes promptly. Therefore, mucosal architecture repairs rapidly, restoring physiologic hepatic apolipoprotein production and normalizing circulating protective high-density lipoprotein cholesterol particles in peripheral circulation.
Clinicians should ideally check baseline fasting lipid panels and atherogenic ratios during initial diagnostic confirmation. Subsequently, clinicians ought to repeat lipid evaluations at six to twelve months after initiating gluten elimination. This timeline allows sufficient intestinal mucosal healing and serological normalization. If dyslipidaemia or elevated atherogenic indices persist despite strict compliance, physicians should perform targeted nutritional assessments. Moreover, continued annual or biennial monitoring ensures enduring cardiometabolic safety as these children transition across critical pubertal growth phases.
Yes, ultra-processed commercial gluten-free alternatives frequently incorporate higher concentrations of saturated fats, hydrogenated palm oils, and simple carbohydrates to enhance culinary texture. Therefore, unguided substitution can paradoxically elevate low-density lipoprotein cholesterol and trigger adverse atherogenic ratios despite good serological adherence. Clinicians must advise families against relying heavily on packaged convenience products. Instead, pediatricians should emphasize naturally gluten-free whole foods, lean proteins, pulses, and heart-healthy dietary fats to maintain optimal long-term cardiovascular health.
Disclaimer: This content is for informational and educational purposes only. It is not intended to provide medical advice or to be used for diagnosing or treating a health problem or disease. Clinicians should always exercise their own independent clinical judgment and seek relevant professional guidance when formulating healthcare decisions. The views expressed herein do not necessarily reflect the official policy or position of any affiliated organizations or institutions. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Adherence to a gluten-free diet significantly increases protective HDL cholesterol and improves atherogenic indices in paediatric coeliac disease. This study highlights the essential role of strict dietary compliance in mitigating long-term cardiovascular risks in children.
Today

The randomized GLARIF trial evaluated early evening versus bedtime insulin glargine administration in type 1 diabetes during Ramadan. The study showed similar hypoglycemia rates and glycemic metrics between both regimens, highlighting the critical need for proactive monitoring and individualized dose management.
Today
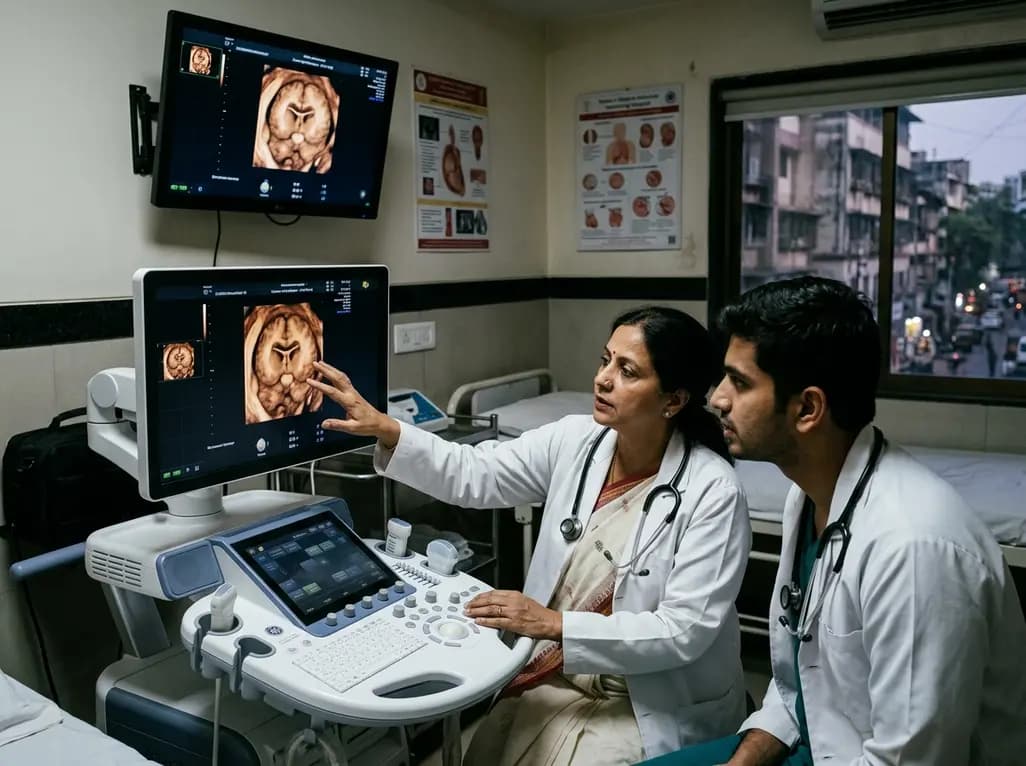
A 3D transvaginal neurosonography study shows the fetal cavum septi pellucidi develops fluid cavitation around 19 weeks and a corpus callosal length of 11.25 mm. These insights help clinicians prevent premature false-positive diagnoses of absent septum pellucidum during second-trimester anomaly scans.
Today

The STADIA-HFpEF trial evaluated whether dapagliflozin improves left ventricular distensibility in phenotypically stratified HFpEF patients without significant myocardial fibrosis. While primary diastolic endpoints were neutral, exploratory improvements in left atrial conduit strain and biomarkers emerged.
Yesterday
An 8-week integrative neuromuscular training protocol significantly improves unilateral jump symmetry, balance, and squat strength in adolescent female sprinters. By correcting lower-extremity asymmetry, this evidence-based intervention reduces injury risk while optimizing athletic sprint performance.
Today

A landmark multi-ethnic study of 40,132 participants demonstrates that risk-weighted apoB (RW-apoB) captures coronary risk beyond measured apoB. By integrating the atherogenic potency of triglyceride-rich lipoproteins and Lp(a), RW-apoB improves cardiovascular risk discrimination across diverse populations.
Yesterday
