

Loading, please wait...
Loading, please wait...

Modern psychiatric epidemiology increasingly explores how meteorological fluctuations modulate psychiatric conditions across diverse populations. Specifically, clinical researchers have long investigated how outdoor ambient temperature influences the progression and severity of mood disorders. While historical studies primarily examined seasonal affective presentations or acute psychiatric admissions during severe heatwaves, granular data on daily mood dynamics remained scarce. A groundbreaking digital health study now offers real-time longitudinal insights into this delicate relationship. By monitoring symptom trajectories alongside local thermal fluctuations, the research provides meaningful clinical guidance for physicians navigating the intersection between environmental stress and affective vulnerability.
To overcome the spatial limitations of past psychiatric research, investigators deployed ecological momentary assessment methodology. The study harnessed aggregate longitudinal data from thousands of active users of the digital health platform juli between 2021 and 2023. Specifically, the cohort comprised 4,000 adult participants tracking depressive symptoms and 2,132 participants monitoring manic symptoms. All participants carried confirmed clinical diagnoses of major depressive disorder or bipolar disorder.
Furthermore, the investigative team linked biennial self-reported symptom inventories with precise meteorological metrics. They gathered real-time mean and maximum ambient temperatures derived from smartphone geolocation grids. Subsequently, researchers utilized negative binomial mixed-effects regression models to evaluate symptom trajectories over recurring two-week windows. Crucially, the statistical framework adjusted for key demographic characteristics and meteorological covariates, including humidity and cloud cover. Additionally, researchers stratified analyses by calendar season to separate baseline seasonal cycles from acute temperature variations. Consequently, the design enabled researchers to evaluate within-person mood shifts relative to outdoor ambient temperature fluctuations. By capturing frequent assessments within natural living environments, the investigators eliminated retrospective recall bias. Thus, the findings offer rare empirical validity regarding everyday environmental exposures.
The statistical analyses revealed distinct and opposing relationships across the affective illness spectrum. Specifically, each 1 °C increase in mean daily ambient temperature over the preceding two weeks correlated with a 0.2% reduction in depressive symptom scores. Conversely, that same 1 °C temperature increment corresponded to a 0.4% increase in manic symptom severity scores. When researchers analyzed maximum daily ambient temperatures, they observed a completely congruent clinical pattern.
Moreover, these dimensional mood alterations demonstrated clear context dependency. The associations varied significantly depending on the prevailing calendar season and the individual participant's typical baseline heat exposure. For example, unseasonably warm weather during cooler seasons altered depressive trajectories differently than sustained midsummer heat. Similarly, patients accustomed to temperate climates reacted more intensely to acute thermal spikes than individuals residing in warmer zones. Therefore, ambient warmth does not exert uniform physiological pressure across all clinical populations. Instead, outdoor temperature acts as a dynamic modifier across the bipolar and depressive spectrum, nudging susceptible individuals toward activation or hypomania while mildly dampening unipolar depressive symptoms. Ultimately, these divergent responses illustrate that rising thermal energy shifts the clinical equilibrium of mood disorders. Consequently, clinicians must evaluate patient vulnerability along a continuum rather than expecting identical outcomes across diagnoses.
Several complementary neurobiological and chronobiological hypotheses help explain these divergent psychiatric responses. First, higher ambient temperatures directly perturb human circadian rhythmicity and thermoregulatory homeostatic control. Heat exposure frequently impairs slow-wave sleep and causes nocturnal awakenings. Because sleep fragmentation represents an established trigger for hypomanic and manic decompensation, nocturnal thermal strain naturally destabilizes vulnerable bipolar patients. In contrast, longer photoperiods and ambient warmth often encourage outdoor physical engagement, which may alleviate psychomotor retardation in depressive episodes.
Furthermore, thermal stress exerts potent neuroendocrine effects on the hypothalamic-pituitary-adrenal axis. Sustained hyperthermia accelerates peripheral cortisol secretion and alters central monoaminergic transmission. In particular, central serotonin synthesis and dopaminergic signaling fluctuate significantly during environmental thermal stress. These altered neurotransmitter pathways enhance central nervous system arousal, motor activity, and irritability. Consequently, elevated temperatures may tip neurochemical balances toward hyperarousal, thereby promoting hypomania. Additionally, thermal stress provokes systemic inflammatory cascades, which alter blood-brain barrier permeability and modulate emotional reactivity. Moreover, individual differences in autonomic thermoregulation further diversify these clinical trajectories. When vascular heat dissipation fails, neurochemical stress escalates rapidly, intensifying psychiatric distress across susceptible populations.
These findings carry immediate practical implications for psychiatrists, general practitioners, and family physicians worldwide. Historically, healthcare providers associated summer primarily with remission in seasonal affective disorders. However, the contemporary data highlight significant psychiatric perils linked to warmer weather, particularly for patients with bipolar disorder. Even subtle thermal increases can trigger subclinical hypomanic symptoms that may escalate into full affective episodes if left unaddressed.
Therefore, clinicians must incorporate environmental and climatic discussions into routine psychiatric consultations. For instance, doctors should counsel bipolar patients to monitor early warning signs of mania during unseasonal heatwaves or seasonal warming trends. Such indicators include reduced need for sleep, heightened irritability, and accelerated goal-directed activities. Additionally, clinicians should evaluate patient living conditions, ensuring adequate access to fans, indoor cooling, and shaded environments. Furthermore, primary care teams ought to review psychotropic drug safety during warm periods. Many psychotropics, including anticholinergics and antipsychotics, disrupt peripheral thermoregulation by reducing diaphoresis. Similarly, dehydration rapidly concentrates serum lithium concentrations, increasing the hazard of acute neurotoxicity. Ultimately, early identification of hypomanic destabilization prevents emergency hospitalizations. By pairing pharmacovigilance with behavioral heat adaptations, clinicians can safeguard vulnerable patients against environmental thermal risks.
Although this investigation provides compelling real-world evidence, clinicians must contextualize the results within several notable study limitations. First, the investigation utilized a convenience sample of individuals who voluntarily downloaded and used a smartphone application. Consequently, the study cohort may overrepresent digitally literate, health-conscious demographics, potentially limiting generalizability to socioeconomically marginalized populations. Furthermore, because researchers prioritized participant privacy through spatial aggregation, the dataset lacked granular neighborhood microclimate data and individual housing characteristics.
Additionally, the researchers could not capture several critical sociodemographic covariates and confounding factors. For example, access to domestic air conditioning, occupational heat exposure, and concurrent somatic comorbidities were not documented. These unmeasured factors could substantially modulate an individual's real thermal burden. Moreover, the study relied on self-reported clinical diagnoses and standardized symptom scoring rather than structured clinician-administered diagnostic interviews. Nevertheless, the study's impressive longitudinal scale and high-frequency ecological momentary assessments provide remarkable statistical power. In addition, future studies should incorporate wearable physiologic monitors to quantify core temperature alongside real-time affect. Such innovations will clarify the precise thresholds where environmental warmth ceases to uplift mood and begins precipitating psychiatric instability.
As global temperatures continue to rise, medical systems must prepare for shifting psychiatric disease burdens. Healthcare providers cannot view climate change solely as an ecological or pulmonary concern; it directly challenges psychiatric health. Indeed, escalating heatwave frequency and higher baseline temperatures will likely exacerbate manic destabilization and acute psychiatric emergencies across vulnerable patient populations.
To counteract these emerging hazards, mental health systems must establish proactive protocols. For example, psychiatric outpatient clinics can integrate automated weather alerts into digital care workflows, prompting timely patient check-ins ahead of projected heatwaves. Furthermore, general practitioners and community health teams should collaborate to establish cooling shelters and outreach services for socially isolated psychiatric patients. Medical educators should also integrate planetary health into psychiatric curricula, training young clinicians to recognize climate-driven mood destabilization. Additionally, community health initiatives must emphasize adequate hydration and sleep hygiene during extreme meteorological events. Through coordinated public health education and proactive clinical vigilance, healthcare teams can mitigate the psychiatric consequences of global environmental warming.
Ambient warming often accelerates circadian disruption, curtails restorative sleep, and elevates physiological stress responses. Furthermore, heat stimulates the hypothalamic-pituitary-adrenal axis and alters monoamine neurotransmission, particularly serotonin and dopamine turnover. Consequently, these combined biological mechanisms can destabilize mood regulation and trigger hypomanic or manic episodes in predisposed patients with bipolar disorder.
Primary care physicians and psychiatrists should schedule anticipatory check-ups before seasonal heatwaves begin. Additionally, practitioners ought to educate patients regarding sleep preservation, indoor cooling, and regular hydration. Moreover, clinicians must carefully track psychotropic drug levels, such as lithium, because dehydration and thermal stress can rapidly precipitate adverse medication toxicities during prolonged hot weather.
Ecological momentary assessment captures granular, real-time patient reports in natural living environments instead of relying on retrospective clinic recalls. Furthermore, linking these longitudinal symptom logs with geolocated microclimatic data enables precise tracking of subtle environmental influences. Therefore, digital health tools provide unique epidemiological insights that inform proactive, highly personalized psychiatric management strategies.
Disclaimer: This content is for informational and educational purposes only and should not be considered as medical advice. Always consult a qualified healthcare professional regarding any medical condition or treatment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A large ecological momentary assessment study reveals that rising outdoor ambient temperatures correlate with decreased depressive symptoms but increased manic symptoms, highlighting key implications for psychiatric management amidst shifting climate patterns.
Today
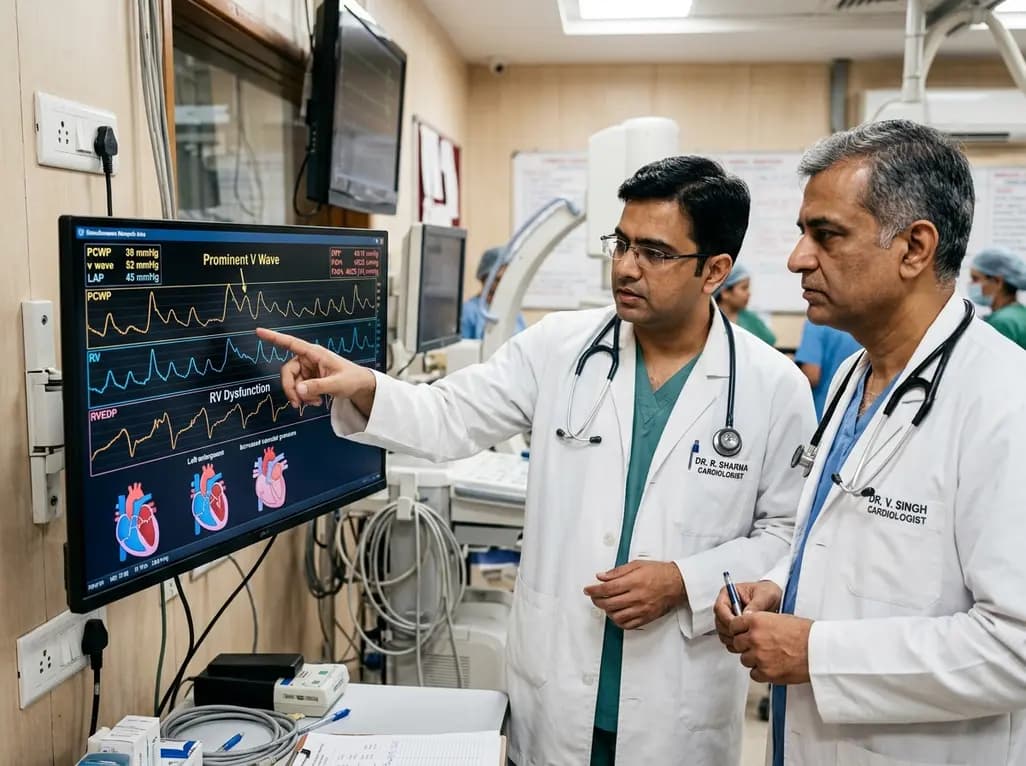
Left atrial stiffening generates prominent V waves that pressurize the pulmonary circulation and augment right ventricular afterload independently of intrinsic pulmonary vascular disease in patients with heart failure with preserved ejection fraction.
Today

A meta-analysis demonstrates that secondhand smoke exposure significantly elevates fetal loss risk by 21% among nonsmoking pregnant women. Clinicians must implement household screening and family-centered cessation interventions to prevent avoidable miscarriages and stillbirths.
Today

Preclinical validation demonstrates that a novel contact force-integrated pulsed field quantization index accurately predicts lesion depth in real time, achieving 100% durable pulmonary vein isolation without collateral injury.
Today
A new cross-sectional evaluation reveals how regional lean mass and bone mineral content interact in resistance-trained men, showing that whole-body size and allometric scaling explain shared musculoskeletal phenotypes and strength relationships.
Today

Explore the emerging role of glucose metabolic reprogramming in exercise-attenuated osteoporosis, examining how physical activity influences osteoblast glycolysis, osteoclast bioenergetics, and skeletal remodeling pathways to improve bone mineral density.
Today
