

Loading, please wait...
Loading, please wait...
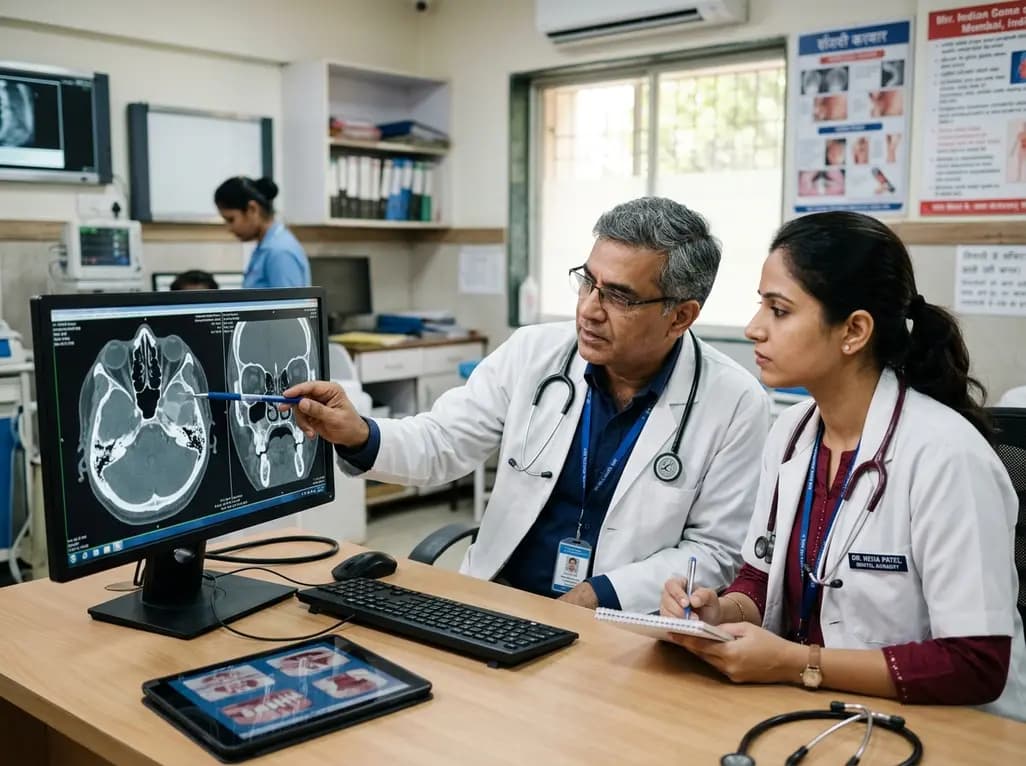
Maxillary sinus disease frequently confronts otolaryngologists, general practitioners, and dental specialists in routine clinical practice. However, clinicians often fail to identify underlying dental pathology during standard rhinosinusitis workups. Recent investigations demonstrate that odontogenic maxillary sinusitis accounts for a substantially higher proportion of sinus disease than historically assumed. When patients present with unilateral facial pressure, foul-smelling nasal discharge, or recurrent sinus opacification, clinicians must maintain a high suspicion for dentoalveolar triggers. Standard medical management often provides only temporary symptom relief because persistent dental infection continually seeds the adjacent Schneiderian membrane. Consequently, early radiographic recognition of odontogenic sources is vital to establish definitive multidisciplinary care and avoid unnecessary sinus procedures.
A recent retrospective cohort study evaluated adult patients presenting to an academic otolaryngology clinic with confirmed acute or chronic maxillary sinusitis. The investigative team analyzed sixty-five computed tomography scans, encompassing eighty-four affected maxillary sinuses, across a single calendar year. Crucially, each sinus scan underwent comprehensive multidisciplinary evaluation by an oral and maxillofacial radiologist, an attending otolaryngologist, a resident physician, and a medical student. The team evaluated the mucosal thickening of the sinus floor alongside specific dental signs indicating infectious spread.
The researchers analyzed how frequently dental pathology contributed to sinus inflammation in an ENT setting. Surprisingly, radiographic signs indicating an odontogenic etiology appeared in 59.52% of the affected maxillary sinuses, representing forty unique patients. This prevalence dramatically exceeded previous general population estimates, which traditionally cited dental involvement in only ten to twelve percent of cases. Furthermore, following multidisciplinary review, the specialists reached consensus that thirty-eight out of the forty affected patients required immediate dental referrals. These findings clearly emphasize that otolaryngologists must systematically evaluate the maxillary dentition on every sinus CT rather than focusing solely on the ostiomeatal complex.
The multidisciplinary investigation highlighted four distinct radiographic features that clinicians must identify on computed tomography to detect underlying dental disease. First, periapical pathology emerged as the most prevalent dental finding, occurring in 56% of the odontogenic sinus cases. Periapical radiolucencies signify localized bone resorption resulting from pulpal necrosis and untreated endodontic infections. Therefore, identifying lucency around posterior tooth root apices should immediately raise suspicion of sinus involvement.
Second, the investigators identified a widened periodontal ligament space in 34% of cases. Periodontal ligament widening reflects active inflammatory changes from chronic periodontitis or occlusal trauma, which can rapidly erode the thin bony sinus floor. Third, the study detected frank oroantral communication in 30% of the affected sinuses. Disruption of the cortical sinus boundary creates a direct conduit for oral microbiota to invade the sterile antral environment. Finally, large dental restorations appeared in 18% of the affected sinuses. Deep restorations and extensive crowns frequently carry subclinical marginal leakage or secondary pulpal decay. Together, these four imaging hallmarks provide clinicians with an objective roadmap to determine when sinus opacification originates from underlying dental disease.
To understand why dental pathology triggers extensive sinus disease, clinicians must examine the unique anatomical architecture of the midface. The roots of the maxillary premolars and molars lie in extremely close proximity to the floor of the maxillary antrum. In many healthy adults, the root apices of the first and second maxillary molars directly abut the sinus cortical floor. Furthermore, anatomical dehiscences frequently leave root apices covered only by the delicate Schneiderian mucosa without intervening cortical bone.
Consequently, infectious processes originating within the dental pulp or periodontal tissues encounter minimal resistance as they progress superiorly. Once bacteria penetrate the antral cavity, the sinus mucosa mounts an intense localized inflammatory response. This reaction rapidly thickens the basal Schneiderian membrane and leads to secondary ostial obstruction. Medical therapy using oral antibiotics or intranasal corticosteroids cannot eliminate pathogens residing securely within necrotic root canals or deep periodontal pockets. Therefore, clinicians must appreciate that persistent sinus symptoms often stem directly from localized dental anatomy. Treating only the sinus cavity without addressing the adjacent tooth root guarantees recurring mucosal inflammation and treatment failure.
Effective management of complex sinus pathology demands seamless cross-specialty collaboration between otolaryngologists, dentists, and radiologists. When otolaryngologists encounter unilateral maxillary sinusitis, they should deliberately review coronal and axial bone algorithm CT windows to scrutinize the posterior dentition. Similarly, general dentists and endodontists must evaluate the adjacent sinus floor when managing patients with deep dental restorations or severe periapical lucencies.
Unfortunately, fragmented care often delays effective diagnosis and prolongs patient discomfort. Patients frequently endure multiple rounds of broad-spectrum antibiotics and unsuccessful nasal decongestants before receiving a proper dental assessment. Conversely, otolaryngologists who identify periapical lucencies or oroantral bone erosion can promptly refer patients for endodontic therapy or surgical tooth extraction. Simultaneous or staged interventions—combining functional endoscopic sinus surgery with appropriate dental procedures—consistently achieve the highest rates of symptom resolution. Moreover, establishing standardized multidisciplinary communication protocols ensures that dental practitioners receive explicit radiographic details regarding sinus floor continuity. By bridging the gap between medical and dental disciplines, healthcare providers substantially reduce diagnostic delays and improve long-term patient outcomes.
The remarkable 60% prevalence of dental-associated findings in this cohort carries profound implications for day-to-day diagnostic protocols in rhinology clinics. Clinicians must recognize that patients with dental-driven sinusitis frequently do not experience local tooth pain. Because pulpal necrosis destroys sensory nerve fibers, patients often present exclusively with nasal obstruction, purulent rhinorrhea, or cacosmia. Therefore, the absence of dental pain should never dissuade clinicians from suspecting an odontogenic etiology.
Furthermore, medical institutions should adapt their standard sinus CT reporting templates to mandate dedicated assessment of the alveolar process and maxillary dentition. Radiologists should explicitly describe periapical bone integrity, periodontal ligament widths, and cortical continuity near posterior tooth apices. When diagnostic ambiguity persists on conventional sinus CT, clinicians can order targeted dental cone-beam computed tomography to acquire high-resolution details of individual root canals. Adopting these proactive diagnostic habits empowers clinicians to intercept disease early, eliminate infectious reservoirs, and prevent severe orbital or intracranial infectious extensions.
Patients frequently experience no localized dental symptoms because chronic endodontic infections often cause complete pulpal necrosis. When the dental pulp dies, sensory nerve conduction ceases entirely within that tooth. Consequently, bacteria continue multiplying silently inside the root canal system without triggering local odontogenic pain. The infection then extends superiorly through the root apex into the maxillary antrum, producing sinus symptoms rather than toothaches.
The maxillary first and second molars are most frequently implicated in odontogenic sinus infections because their root apices lie closest to the antral floor. The maxillary second premolars and third molars can also trigger sinus inflammation when anatomical roots project into the sinus cavity. Clinicians should systematically inspect these specific posterior teeth on every sinus CT scan for subtle periapical radiolucency or bone loss.
Successful treatment requires addressing both the dental source and the secondary sinus inflammation concurrently. Medical management alone cannot clear bacteria residing inside non-vital root canals. Therefore, patients require definitive dental therapy, such as endodontic treatment or tooth extraction, combined with targeted antimicrobial coverage. In patients with severe ostial obstruction or fungal elements, otolaryngologists perform functional endoscopic sinus surgery alongside dental care to restore natural sinus drainage.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A recent ENT cohort study reveals that nearly 60% of maxillary sinusitis cases show dental etiology on CT. Learn four radiographic findings prompting dental evaluation.
Today

Therapeutic resistance and metastatic spread remain formidable barriers in oncology. By targeting the dysregulated ion transportome—including aberrant ion channels, pumps, and solute carriers—clinicians may unlock novel therapeutic strategies to sensitise refractory solid tumours.
Today
A scoping review maps conservative physiotherapy resources in lipedema, highlighting complex decongestive therapy, compression garments, and structured exercise. While multimodal therapy alleviates edema and pain, high-quality randomized clinical trials remain necessary to confirm definitive therapeutic efficacy.
Today

A study reveals that the MYLK c.4079G>A, p.(Gly1360Asp) variant is linked to high-penetrance heritable thoracic aortic disease and early-onset aortic dissection, showing a founder effect in Finnish cohorts. Findings emphasize early cascade screening and vigilant surveillance.
Today

A cross-sectional study reveals that reduced upper extremity exercise capacity measured by the 6-minute pegboard and ring test significantly correlates with higher disability in non-specific chronic low back pain, highlighting the necessity of assessing whole-body functional chains in rehabilitation.
Today
An animal model study reveals that gestational exposure to polystyrene microplastics causes persistent intrauterine growth restriction, testicular hypoplasia, Leydig cell depletion, and an atypical low-testosterone, low-LH endocrine profile in male offspring from birth into adulthood.
Today
