

Loading, please wait...
Loading, please wait...
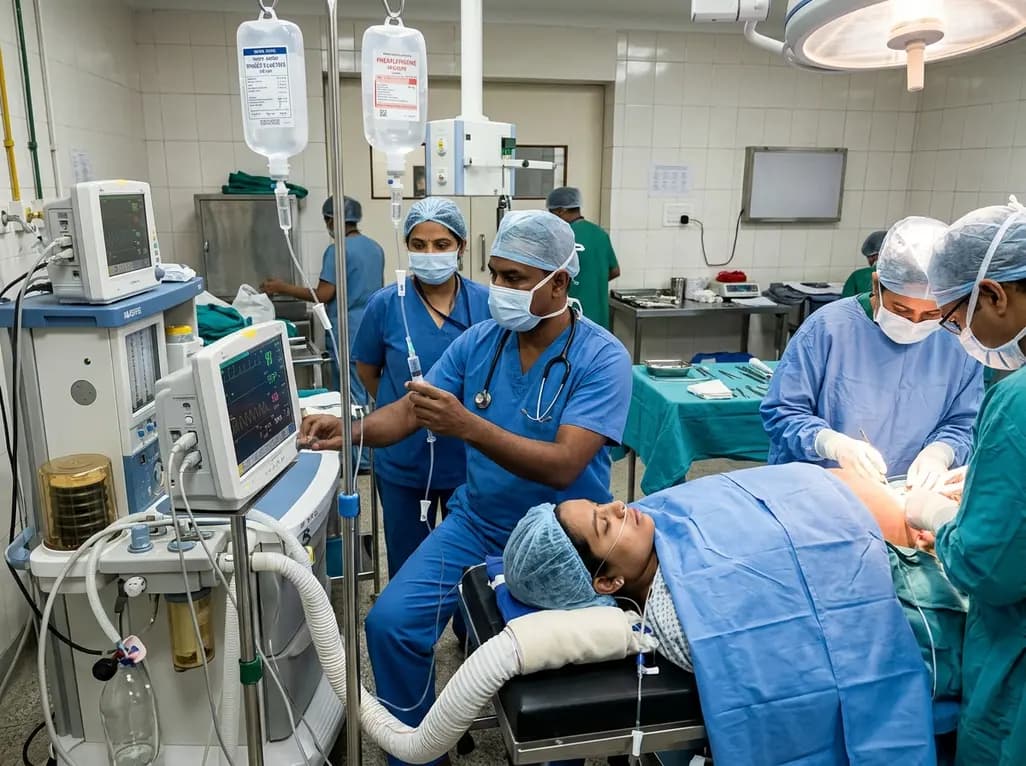
Modern perioperative care in maternal medicine relies heavily on clinical standardisation to maintain safety during operative delivery. Standardised protocols for obstetric anesthesia best practices aim to minimize preventable intraoperative complications, reduce surgical infection risks, optimize postoperative pain management, and limit general anesthesia usage. However, real-world adherence to these established clinical practice guidelines varies significantly across different healthcare centers. To quantify this compliance gap, researchers analyzed data from the Multicenter Perioperative Outcomes Group (MPOG) database, evaluating 289,047 cesarean delivery cases from 2015 to 2022. The study measured institutional adherence to seven key practice guidelines and identified patient-, case-, and hospital-level factors driving protocol variation. Consequently, this vast multicenter cohort provides unprecedented insight into contemporary obstetric anesthesia practices, revealing strengths while highlighting critical targets for systemic quality improvement.
The comprehensive analysis revealed notable compliance variation across the seven evaluated evidence-based clinical practices. High adherence was demonstrated in several fundamental areas, reflecting strong clinical adoption. Avoidance of general anesthesia achieved the highest compliance at 97.0%, demonstrating widespread practitioner preference for neuraxial techniques. Similarly, post-spinal systolic blood pressure maintenance above 90 mmHg reached 96.7% adherence, showing consistent hemodynamic vigilance. Spinal needle selection using 25-gauge or smaller needles achieved 89.0% compliance, effectively mitigating post-dural puncture headache risks. Timely prophylactic antibiotic administration occurred in 86.2% of cases, while low-dose neuraxial morphine was utilized in 74.2% of deliveries. Conversely, post-spinal vasopressor infusions showed the lowest adherence at 55.4%. Furthermore, active prevention of perioperative hypothermia reached only 56.7%. Therefore, while core procedural techniques are well-maintained, supportive physiological protocols require substantial clinical enhancement.
Fluctuations in protocol adherence stem from a complex interplay of patient, operational, and institutional factors. The study revealed that lower compliance strongly correlated with specific risk factors across all three domains. At the patient level, an American Society of Anesthesiologists (ASA) Physical Status of 4 or higher was linked to poorer adherence, as severe maternal acuity often necessitates urgent deviation from standard pathways. At the case level, evening and overnight cesarean deliveries exhibited lower compliance compared to elective daytime cases. Reduced off-hour staffing, practitioner fatigue, and emergency timing pressures significantly hinder protocol execution during night shifts. Furthermore, hospital-level factors showed that institutions lacking obstetric anesthesia fellowships or Center of Excellence designation had markedly lower adherence rates. Consequently, specialized training environments and structured quality frameworks are essential for maintaining high compliance standards.
The marked underutilization of continuous vasopressor infusions and active thermal management highlights key priorities for clinical intervention. Prophylactic vasopressor infusions, such as phenylephrine or norepinephrine, effectively mitigate spinal-induced hypotension, reduce maternal nausea, and preserve fetal oxygenation during surgery. Despite clear international guidelines, many departments still rely on reactive bolus dosing rather than proactive continuous infusions. Transitioning to routine prophylactic infusions requires updated departmental protocols, pre-mixed infusion availability, and nursing staff education. Similarly, unaddressed maternal perioperative hypothermia increases intraoperative blood loss, impairs drug metabolism, and causes neonatal thermal stress. Consequently, active forced-air warming, warmed fluid administration, and ambient temperature regulation must become mandatory standards. Automated electronic health record prompts can also help remind clinical teams to initiate active warming and vasopressor support promptly.
These multicenter findings offer vital practical insights for anesthesiologists and obstetricians in India, where cesarean section rates are rising rapidly across urban and rural centers. While neuraxial anesthesia is widely utilized across Indian delivery units, post-spinal hemodynamic stability and perioperative thermal management remain major ongoing challenges. High patient turnover, resource limitations, and variable off-hour staffing frequently impede consistent guideline adherence during emergency night-shift procedures. Therefore, adopting structured quality assurance programs modeled on international registry benchmarks can greatly enhance regional practice standards. Indian hospitals should prioritize establishing standardized vasopressor infusion protocols for spinal anesthesia and enforce active forced-air warming during operative deliveries. Furthermore, strengthening interprofessional communication between anesthesiologists, obstetricians, and nursing teams will ensure timely prophylactic antibiotics and optimal spinal needle selection across all delivery centers.
Closing the gap between published guidelines and bedside practice requires scalable data-driven quality improvement tools. Electronic medical record alerts, peer audit-and-feedback reporting, and standardized clinical checklists effectively align daily practice with evidence-based standards. Additionally, healthcare institutions must invest in specialized obstetric anesthesia training and pursue center-of-excellence status to foster dedicated clinical expertise. Mitigating off-hour practice disparities necessitates equitable night-shift staffing, accessible pre-packaged medications, and standardized emergency workflows. Professional societies should also continue updating clinical guidelines while offering adaptable implementation toolkits for diverse healthcare settings. By systematically addressing patient acuity, off-hour operational hurdles, and institutional training gaps, perioperative teams can elevate maternal safety and deliver consistent, high-quality, evidence-based care during every cesarean delivery.
Prophylactic vasopressor infusions, using agents such as phenylephrine or norepinephrine, effectively prevent spinal anesthesia-induced hypotension by maintaining maternal systemic vascular resistance. Proactive infusion management maintains arterial blood pressure stability more reliably than reactive bolus administration. Consequently, this continuous approach significantly reduces maternal nausea, intraoperative dizziness, and uteroplacental hypoperfusion, thereby optimizing umbilical arterial blood gas parameters and improving neonatal metabolic outcomes during cesarean delivery.
Perioperative hypothermia during cesarean section adversely affects both maternal and neonatal outcomes. Inadvertent maternal cooling increases intraoperative blood loss, impairs blood coagulation, alters drug metabolism, and increases post-anesthesia shivering and surgical site infection risks. Additionally, maternal hypothermia contributes to neonatal cold stress and impaired thermal adaptation immediately following birth. Active forced-air warming and heated intravenous fluid administration significantly minimize these clinical risks.
The study demonstrated that emergency or off-hour cesarean deliveries performed during evening or overnight shifts exhibited lower guideline adherence compared to daytime elective procedures. Reduced specialty staffing, practitioner fatigue, emergency time constraints, and lack of dedicated operational support contribute to these performance gaps. Addressing off-hour disparities requires standardized electronic check-lists, pre-mixed medications, and equitable night-shift staffing models across health institutions.
Disclaimer: This content is for informational and educational purposes only, and does not constitute medical advice, diagnosis, or treatment. Always seek the advice of a qualified healthcare provider with any questions you may have regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References
Francke JA et al. Frequency of adherence to obstetric anesthesia best practices for cesarean delivery: A multicenter retrospective cohort analysis. Anesthesiology. 2026 Aug 12. doi: 10.1097/ALN.0000000000006330. PMID: 42585602.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A multicenter MPOG database study of 289,047 cesarean delivery cases analyzed adherence to obstetric anesthesia best practices. General anesthesia avoidance reached 97.0%, while post-spinal vasopressor infusions (55.4%) and hypothermia prevention (56.7%) showed the lowest compliance, highlighting key targets.
4 weeks back

A large NHANES cohort study reveals that higher Healthy Eating Index scores significantly reduce all-cause mortality risk in CKD patients by 45%. This analysis highlights the importance of comprehensive diet quality and medical nutrition therapy in renal care to optimize long-term clinical survival.
Today

Explore real-world data showing how private oncogenetics and molecular tumor boards achieve 3-week consult turnaround, high ctDNA actionability, and vital germline variant detection, enhancing individualized cancer care and familial risk assessment.
Today
A meta-analysis of 13 propensity score-matched studies shows ViV-TAVR delivers lower early mortality and reduced bleeding compared to redo-SAVR for degenerated bioprosthetic aortic valves, though long-term hemodynamics warrant careful anatomical and patient-centered evaluation.
Today
Endoscopic posterior cervical fusion combines minimally invasive decompression, joint preparation, and rigid screw-rod fixation for atlantoaxial pathologies. Early clinical findings demonstrate solid bony union, excellent symptom relief, and minimal soft-tissue morbidity without significant vascular compromise.
Today

The All-India Food Processors' Association has approached the Supreme Court to oppose FSSAI's proposed per-100g benchmark for front-of-pack warning labels, advocating instead for a per-serving threshold. We explore the regulatory showdown, nutritional evidence, and implications for clinical lifestyle counseling.
Today
