

Loading, please wait...
Loading, please wait...
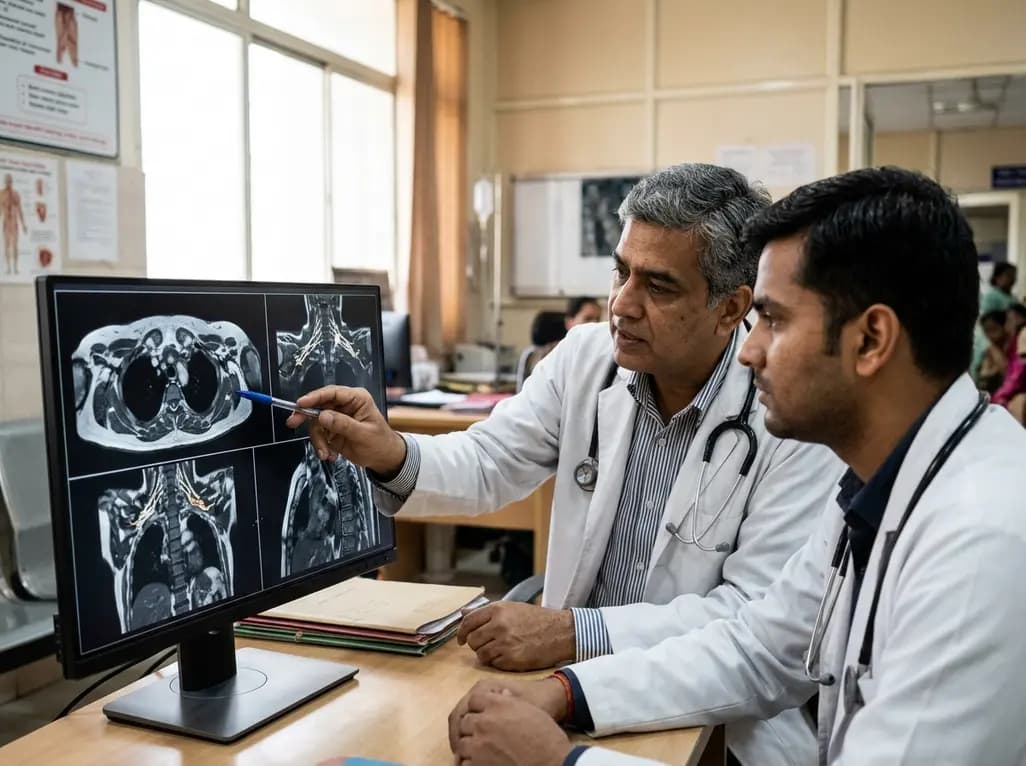
Neurogenic thoracic outlet syndrome represents one of the most perplexing peripheral nerve compression disorders encountered in modern clinical practice. Patients frequently present with debilitating upper extremity pain, paresthesias, and progressive hand weakness. However, clinicians often struggle to establish an objective diagnosis because conventional diagnostic tests yield equivocal findings. Consequently, the condition has historically remained a diagnosis of exclusion. Recent advancements in magnetic resonance neurography now offer transformative morphological visualization of the brachial plexus. By directly evaluating brachial plexus trunk architecture, high-resolution neurography substantially improves diagnostic accuracy and facilitates targeted surgical decompression strategies.
Diagnosing neurogenic thoracic outlet syndrome has long challenged orthopedic surgeons, neurologists, and interventional radiologists alike. Because the anatomical compression occurs within complex spaces—such as the interscalene triangle and costoclavicular space—routine physical maneuvers frequently lack diagnostic specificity. Indeed, provocative physical examination maneuvers often provoke nonspecific paresthesias even among healthy individuals. Furthermore, standard electromyography evaluates distal nerve conduction velocity but frequently misses proximal nerve entrapment within the scalene triangle. As a result, many symptomatic patients endure protracted delays before receiving an accurate clinical assessment. Historically, diagnostic uncertainty caused significant frustration for both patients and clinicians. In addition, conventional magnetic resonance imaging protocols often fail to reveal subtle perineural compressive elements. Fibrous bands, scalene muscle hypertrophy, and anomalous osseous structures rarely display clear compressive morphology on standard scans. Therefore, physicians have demanded more reliable, non-invasive imaging techniques to visualize the brachial plexus directly. High-resolution magnetic resonance neurography resolves these diagnostic ambiguities by providing exquisite soft-tissue contrast and superior spatial resolution. Consequently, this advanced imaging modality bridges the longstanding gap between clinical suspicion and definitive anatomical confirmation.
Recent clinical evaluations clearly demonstrate the superior diagnostic yield of magnetic resonance neurography over traditional electrodiagnostic testing. In a retrospective study evaluating surgical candidates, magnetic resonance neurography successfully identified thoracic outlet compression in 78.1 percent of patients. In stark contrast, electromyography identified abnormalities in only 43.8 percent of the exact same surgical cohort. This striking disparity highlights the notable limitations of relying solely on neurophysiological studies to guide surgical decisions. Electromyography primarily detects secondary denervation or significant motor axon loss, which typically emerges only in advanced disease. Conversely, magnetic resonance neurography visualizes immediate morphological changes within irritated neural tissue long before irreversible axonal damage manifests. Furthermore, the seven patients in the cohort with negative neurography also exhibited entirely normal electromyography and standard magnetic resonance imaging results. Consequently, magnetic resonance neurography captures a substantially higher rate of true compressive pathology. These findings emphasize that a normal electromyogram cannot reliably rule out clinically meaningful nerve trunk entrapment. Therefore, incorporating magnetic resonance neurography earlier in the diagnostic algorithm prevents critical diagnostic delays and avoids inappropriate conservative therapies.
High-resolution magnetic resonance neurography provides objective morphological markers that confirm localized nerve injury and brachial plexus compromise. Among affected patients, the most prevalent neurographic finding is T2-weighted signal hyperintensity, observed in approximately 80 percent of confirmed cases. This abnormal hyperintensity reflects endoneurial fluid accumulation, intraneural edema, and vascular congestion resulting from persistent mechanical compression. In addition, nerve trunk thickening represents the second most common structural abnormality, appearing in 44 percent of diagnostic scans. Such focal thickening indicates chronic perineural fibrosis and reactive connective tissue proliferation within the confined costoclavicular corridor. Notably, imaging also reveals secondary muscular changes resulting from nerve irritation. Approximately 16 percent of evaluated patients exhibit intramuscular edema within the supraspinatus and infraspinatus muscles. This muscular edema signifies denervation changes and localized motor dysfunction linked to proximal trunk compromise. Additionally, diagnostic scalene injections provide valuable supplemental confirmation, with approximately 40 percent of patients experiencing temporary symptom relief. When clinicians correlate these distinct neurographic imaging markers with physical examination findings, they achieve an unprecedented degree of diagnostic confidence.
Definitive surgical decompression provides dramatic symptom relief for appropriately selected patients who exhibit clear neurographic and clinical findings. In operative cohorts, surgical release—performed either with or without first rib resection—yields substantial functional improvement in over 78 percent of cases. Furthermore, complete resolution of chronic pain and paresthesias occurs in more than 12 percent of surgically treated individuals. Only a small fraction, approximately 9 percent, experience persistent postoperative discomfort, often due to longstanding chronic neuropathic pain. During surgery, surgeons direct decompression toward tight scalene musculature, anomalous fibrous bands, and osseous impingements identified on pre-operative scans. Because magnetic resonance neurography pinpoints the precise anatomical level of entrapment, surgeons can tailor their operative exposure with exceptional precision. Consequently, targeted decompression minimizes unnecessary tissue dissection and significantly reduces intraoperative risks to adjacent subclavian vasculature. Moreover, post-surgical recovery accelerates because neural structures undergo prompt, targeted mechanical decompression. These favorable surgical outcomes reinforce the vital clinical relationship between accurate pre-operative imaging localization and successful postoperative functional recovery.
The emerging evidence strongly supports integrating magnetic resonance neurography into standard clinical workflows for suspected thoracic outlet compression. Clinicians should initially conduct meticulous physical examinations, assessing for upper extremity weakness, sensory deficits, and positive provocative maneuvers. When clinical findings suggest brachial plexus entrapment, physicians should promptly order specialized neurography rather than relying solely on non-diagnostic conventional scans. Although electromyography remains helpful for excluding distal entrapment neuropathies like carpal tunnel syndrome, it lacks adequate sensitivity for isolated thoracic outlet compression. Therefore, advanced neurography should serve as the primary objective imaging tool in ambiguous or treatment-refractory cases. Additionally, multidisciplinary teams comprising neurologists, orthopedic surgeons, and radiologists must collaborate closely to interpret these complex neurographic sequences. Dynamic imaging protocols with hyperabduction maneuvers can further enhance diagnostic yield by exposing positional nerve compression. Moving forward, large-scale prospective clinical trials will help standardize imaging protocols across global healthcare institutions. Ultimately, adopting this modern diagnostic approach ensures timely intervention, reduces patient morbidity, and optimizes functional outcomes.
Conventional magnetic resonance imaging optimizes broad anatomical visualization of musculoskeletal structures, but it lacks sufficient spatial resolution to delineate individual peripheral nerve fascicles. In contrast, magnetic resonance neurography utilizes specialized, high-resolution sequences with uniform fat suppression. This advanced protocol maximizes contrast resolution, highlighting subtle intraneural signal alterations, perineural edema, and structural caliber changes that standard scans consistently miss.
Electromyography and nerve conduction studies primarily identify severe axon loss or substantial demyelination occurring in motor and large sensory fibers. In early or dynamic thoracic outlet compression, intermittent mechanical irritation primarily affects smaller, pain-sensing unmyelinated fibers without causing extensive distal motor denervation. Consequently, electrodiagnostic tests remain normal in over half of affected patients, requiring high-resolution imaging to confirm localized compression.
The predominant neurographic finding of brachial plexus compression is focal T2-weighted signal hyperintensity, which occurs in roughly 80 percent of cases due to intraneural edema. Additionally, nerve caliber enlargement or focal thickening appears in nearly half of affected patients. Clinicians also frequently observe denervation edema within adjacent shoulder girdle musculature, corroborating severe mechanical nerve impingement.
Disclaimer: This content is for informational and educational purposes only and should not be considered medical advice. Always consult a qualified healthcare professional regarding any medical condition or treatment. While we strive to provide accurate, evidence-based content, medical knowledge is constantly evolving. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A recent study highlights the critical role of MRI neurography in diagnosing neurogenic thoracic outlet syndrome. With a 78.1% detection rate compared to 43.8% for EMG, MR neurography provides vital anatomical visualization of brachial plexus compression to guide surgical decompression.
Today

Central chronotropic incompetence is an underrecognized sequela of rhombencephalitis causing exertional dyspnea despite normal resting cardiac function. Cardiopulmonary exercise testing unmasks this heart-brain uncoupling, guiding rate-responsive pacing and targeted rehabilitation.
Today
Perimenopause brings erratic hormonal surges and metabolic shifts that significantly affect breast tissue. This comprehensive clinical review examines benign breast conditions, cancer risk stratification, mammographic density challenges, and endocrine therapy transitions in midlife women.
Today
A registry study of 4,989 patients evaluates transvenous lead extraction for right-sided cardiac devices. Despite longer dwell times and older leads, right-sided extractions achieve high procedural success and comparable safety to left-sided approaches.
Today
Recent crash analyses demonstrate significant variations in traffic injury severity across vehicle seating positions. Electric vehicle passengers face disproportionately higher trauma risks than drivers, particularly during airbag deployments, demanding adapted emergency assessment and clinical vigilance.
Today

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
