

Loading, please wait...
Loading, please wait...

Modern medical systems frequently encounter severe budgetary pressures and resource allocation challenges. When clinical needs outpace available institutional resources, physicians and administrative leaders inevitably face profound ethical conflicts. Consequently, moral distress in healthcare has emerged as a pervasive organizational challenge that affects clinical decision-making, patient outcomes, and staff retention across healthcare institutions globally. Addressing these systemic obstacles requires understanding the lived experiences of frontline staff and healthcare leadership alike.
Historically, bioethicists defined moral distress as the psychological anguish that occurs when clinicians recognize the ethically correct action but face insurmountable institutional barriers that prevent them from executing it. In contemporary clinical environments, healthcare resource cutbacks represent the most prominent systemic driver of this dissonance. For instance, when hospital executives enforce austerity measures, bedside doctors must frequently navigate severe shortages of essential medications, critical care beds, and auxiliary staffing. Consequently, clinical teams face agonizing triage decisions that challenge their fundamental commitment to non-maleficence and patient advocacy. Furthermore, this dynamic is not restricted to frontline clinicians alone. Nurse managers, department chairs, and clinical directors also experience intense psychological conflict when higher administrative directives force them to cut operating budgets while expecting uncompromised clinical standards. Because institutional austerity restricts the tangible possibilities for ethical action, clinicians increasingly feel that systemic barriers undermine their moral agency. Therefore, recognizing that resource scarcity is an organizational issue is essential for preserving the mental health and professional integrity of healthcare workers.
Major structural reorganizations and administrative reforms frequently disrupt established clinical workflows and ethical care delivery. When healthcare organizations prioritize cost-efficiency over clinical nuance, clinicians frequently perceive an irreconcilable divide between corporate priorities and patient-centered values. For example, sudden cuts to auxiliary personnel, diagnostic equipment, or ward capacity directly compel clinicians to ration routine care. As a result, healthcare professionals must frequently apologize for systemic delays and inadequate accommodations that remain entirely outside their personal control. Moreover, clinical leaders often find themselves caught between senior administrative mandates and frontline clinical reality. These middle managers must implement severe budgetary restrictions while simultaneously attempting to protect ward staff from acute ethical injury. Consequently, this intermediary position creates immense cognitive dissonance and moral isolation for physician executives. When healthcare facilities undergo continuous restructuring without adequate clinical input, the lack of collaborative governance steadily deteriorates organizational trust. Furthermore, repeated exposure to compromised standards forces healthcare workers to normalize suboptimal practices, which gradually desensitizes teams to compromised patient safety and ethical care standards.
Chronic exposure to unaddressed ethical dilemmas exacts a profound emotional toll on healthcare providers. When practitioners cannot deliver ideal care, they experience persistent guilt, powerlessness, and moral failure. In addition, this unresolved emotional turmoil frequently progresses beyond conventional occupational fatigue into profound moral injury and psychological exhaustion. Over time, persistent moral distress erodes the clinician’s professional identity and undermines their sense of vocational fulfillment. Consequently, many highly capable physicians and nurses gradually detach from their clinical roles or develop cynical coping mechanisms to survive daily shifts. Furthermore, this emotional detachment directly threatens patient safety, as disengaged healthcare workers experience higher rates of cognitive fatigue, diagnostic oversights, and communication breakdowns. Ultimately, systemic neglect of these emotional repercussions fuels widespread attrition, prompting skilled healthcare professionals to abandon hospital environments or leave clinical medicine entirely. Healthcare institutions must therefore realize that unmitigated ethical stress directly destabilizes clinical workforce stability.
A deep sense of vocational calling and professional commitment has long served as the primary bedrock of quality healthcare. Clinicians willingly work extended shifts, absorb operational delays, and sacrifice personal comfort to safeguard vulnerable patients under their direct supervision. However, this profound commitment functions as a paradoxical double-edged sword within resource-constrained environments. While vocational dedication provides personal resilience during acute hospital crises, institutional administrators often exploit this goodwill to compensate for chronic operational deficiencies. Consequently, clinicians who hold the highest ethical standards and patient empathy suffer the greatest vulnerability to moral distress. Because these committed practitioners refuse to compromise on compassionate care, they shoulder the emotional and physical burden of institutional austerity alone. In addition, when systemic resource deficits repeatedly frustrate their diligent efforts, these conscientious professionals experience acute existential disillusionment. Thus, relying solely on individual resilience without providing adequate structural support creates unsustainable work environments that penalize the most conscientious healthcare workers.
Safeguarding moral agency within modern healthcare organizations demands a multifaceted approach centered on relational solidarity and ethical leadership. Open peer communication, structured clinical debriefs, and ethics consultation services provide vital psychological safe harbors where multidisciplinary teams can process difficult clinical decisions. Furthermore, empathetic leadership plays an indispensable protective role against institutional cynicism. When healthcare administrators openly acknowledge resource limitations rather than masking them behind productivity metrics, clinicians feel heard and validated. Additionally, organizations must establish transparent allocation protocols that relieve clinicians from bearing the sole burden of rationing scarce resources. Clinical ethics committees should actively collaborate with departmental leadership to develop practical frameworks that defend human dignity and equitable care. In addition, hospitals must invest in supportive institutional infrastructure, including accessible psychological support and peer-led ethics discussion rounds. Ultimately, creating an ethically sustainable healthcare ecosystem requires shifting from individual blame toward collective responsibility, structural accountability, and compassionate leadership.
Moral distress in healthcare occurs when clinicians recognize the proper ethical action but encounter institutional barriers that prevent its delivery. Unlike generalized workplace burnout, moral distress originates specifically from perceived compromises to core professional ethics and personal integrity. Consequently, this persistent dissonance leads to emotional exhaustion, guilt, cynicism, and impaired clinical performance if left unaddressed. Ultimately, institutional failure to address these challenges exacerbates clinician turnover.
While frontline healthcare professionals experience moral distress directly at the bedside when rationing treatment, healthcare leaders face a distinct administrative conflict. Specifically, middle managers and clinical directors must execute top-down financial cuts while simultaneously attempting to protect clinical quality and staff morale. Consequently, leaders experience acute moral distress because they must balance corporate mandates against the immediate welfare of their staff. This dual pressure creates profound professional isolation and management fatigue.
Hospitals can significantly reduce moral distress by establishing multidisciplinary ethics committees, instituting regular clinical debriefings, and creating transparent resource-allocation protocols. Furthermore, institutional leaders must encourage open dialogue regarding ethical dilemmas without penalizing staff who raise concerns. In addition, providing formal training in moral resilience equips clinicians with cognitive coping strategies. Furthermore, active administrative support ensures that frontline healthcare workers never face systemic austerity alone.
Disclaimer: This content is for informational and educational purposes only and should not be considered as medical advice. The views expressed are based on current research and clinical observations. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Healthcare resource cutbacks create severe organizational conditions that constrain moral agency, triggering moral distress across frontline clinicians and healthcare leaders. Addressing this crisis requires ethical leadership, relational solidarity, and transparent resource allocation frameworks.
Today

Maharashtra has initiated the appointment of two dedicated special public prosecutors in every district alongside a joint police-health SOP to fast-track PCPNDT and MTP cases. Medical imaging centers, radiologists, and obstetricians must strengthen statutory documentation and audit preparedness.
Today
A study in pediatric cardiology reveals that infants under two months require median enoxaparin doses of 2.13 mg/kg/dose, alongside more dose titrations and longer times to reach target anti-Xa levels compared to older children, underscoring the need for tailored dosing and aggressive monitoring.
Today
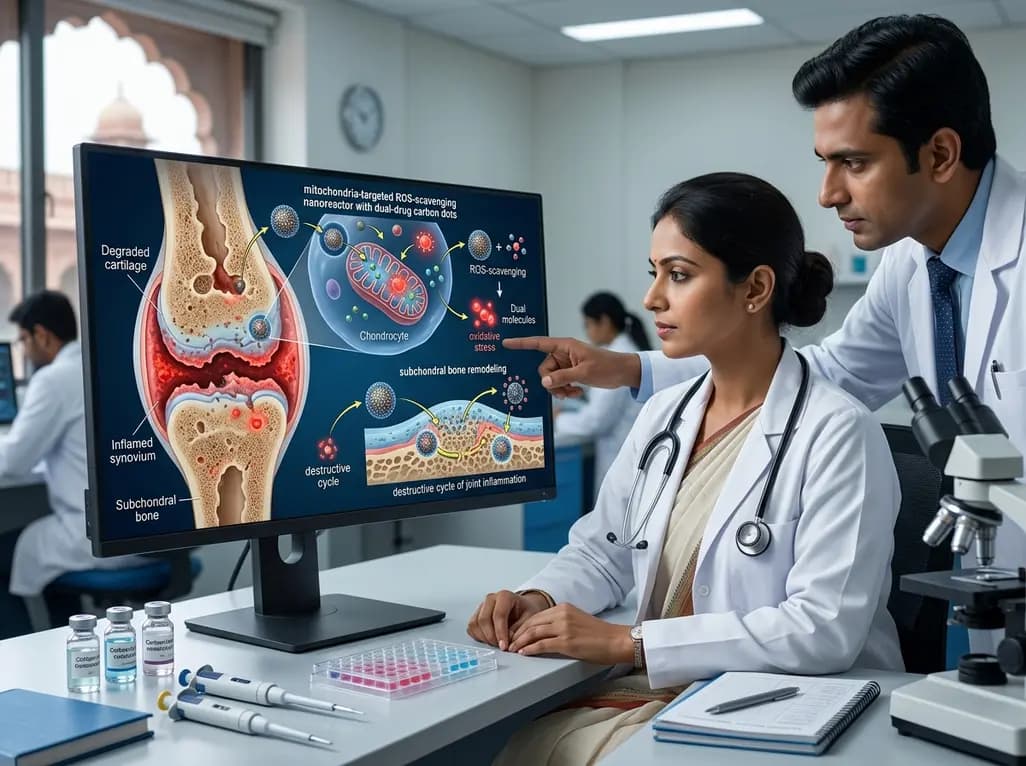
A novel mitochondria-targeted ROS-scavenging nanoreactor with dual-drug carbon dots provides a multi-mechanism strategy for osteoarthritis therapy. By neutralizing oxidative stress and remodeling subchondral bone, this platform breaks the destructive cycle of chronic joint inflammation and cartilage degeneration.
Today

An exploratory pilot study evaluates metoprolol pharmacokinetics across cisgender males, cisgender females, and transgender women on gender-affirming hormone therapy. Findings reveal distinct drug disposition trends, emphasizing the critical need for genotype-stratified research in transgender cardiovascular care.
Today
