

Loading, please wait...
Loading, please wait...
Pilonidal sinus disease represents a recurrent, debilitating problem affecting young adults worldwide. Managing deep natal cleft anatomy and chronic infection poses ongoing difficulties for operating surgeons. Over recent decades, multiple reconstructive techniques have attempted to mitigate the high rates of wound dehiscence and recurrence that follow simple excision. The newly described modified parasacral flap offers a reproducible, tension-free closure without demanding microsurgical instrumentation. Consequently, this innovation equips general and plastic surgeons with a reliable, durable strategy for complex natal cleft reconstruction.
Sacrococcygeal pilonidal sinus disease arises predominantly from an acquired mechanical mechanism. Deep natal clefts generate substantial negative pressure during locomotion, drawing shed hair and keratin debris into moist cutaneous pits. Subsequent foreign body reactions incite indolent infection, epithelialized tract formation, and chronic discharging sinuses. Conservative interventions frequently fail once extensive subcutaneous branching develops. Therefore, definitive management mandates complete excision of the infected sinus system down to the postsacral fascia.
However, traditional primary midline wound closure generates high tension across the gluteal bridge. This elevated mechanical strain often results in wound breakdown, chronic seroma collection, and unacceptable recurrence rates approaching thirty percent. When wounds heal by secondary intention, patients encounter months of uncomfortable packing and prolonged workplace absence. Thus, modern reconstructive goals prioritize complete extirpation paired with flattening of the natal cleft. Achieving these objectives moves surgical scars lateral to the intergluteal fold, eliminating the vacuum forces that cause recurrent disease.
To overcome midline wound complications, surgeons devised various transposition and rotation procedures. Notable options include the Limberg rhomboid transposition, the Karydakis lateral flap, and V-Y fasciocutaneous advancements. Although these procedures effectively shallow the deep cleft and displace scars laterally, extensive mobilization can produce tip necrosis and substantial tissue waste. Furthermore, traditional perforator-based reconstructions necessitate skeletonizing minute vascular branches, introducing technical hurdles that limit widespread general surgical adoption.
The classic parasacral perforator flap delivers excellent vascularity based on sacral branches of the internal iliac or superior gluteal vascular arcade. Nevertheless, formal perforator isolation requires microvascular dissection and intraoperative Doppler verification. These rigorous technical demands restrict classic perforator flaps to dedicated plastic surgery units. In contrast, the modified parasacral flap sidesteps tedious vessel skeletonization while preserving exceptional axial perfusion. This critical evolution maintains reconstructive safety without compromising surgical simplicity.
The modified parasacral flap refines local tissue transfer by leaving the deep flap base, intact perforators, and surrounding adventitial fat undisturbed. Following prone positioning and broad antiseptic preparation, the surgeon meticulously excises all diseased sinuses en bloc down to the presacral fascia. The resulting rhomboid or elliptical defect leaves healthy, bleeding margins alongside a flattened natal contour. Methylene blue instillation often aids in delineating obscure secondary tracts before initial incision.
Rather than dissecting isolated vascular pedicles, the operating team designs an adjacent fasciocutaneous paddle tailored to the defect dimension. Operative findings consistently reveal robust parasacral perforators situated at the 12 o'clock and 1 o'clock positions relative to the sacrococcygeal junction. By preserving a broad subcutaneous pedicle around these predictable vessels, the surgeon preserves physiological perfusion without microdissection. Mobilizing peripheral subcutaneous borders allows smooth, tensionless rotation or advancement into the cleft defect, after which layered closure obliterates dead space.
In a clinical cohort comprising twenty consecutive male patients treated between November 2014 and January 2022, this modified technique demonstrated outstanding safety. The cohort exhibited a mean age of 28.35 years, reflecting the typical demographic burden of symptomatic sacrococcygeal disease. Surgical teams fashioned flaps averaging 5 cm by 11.75 cm, successfully resurfacing sizable postsurgical voids. Across every documented intervention, surgical exploration confirmed reliable perforating branches at the anticipated cranial margins.
Remarkably, all twenty flaps achieved complete survival with zero total or partial flap loss. Only two patients developed minor postoperative complications, characterized by superficial surgical site inflammation that resolved quickly with conservative management. Across an average follow-up period of 8.65 months, clinicians identified zero recurrences. These objective metrics confirm that broad-based subcutaneous tissue preservation shields perforating vessels from stretch injury, twisting, or spasm, ensuring exceptional microcirculatory resilience.
From an institutional workflow perspective, this simplified reconstructive paradigm yields considerable logistical benefits. Traditional perforator flaps demand specialized operating loupes, micro-instruments, and acoustic handheld Doppler monitoring, which increase setup times and operative costs. Because the modified flap relies on macroscopic anatomic landmarks and preserved adipose cushioning, general surgeons can execute it safely in community and district hospital theaters.
Furthermore, avoiding intricate skeletonization significantly reduces total operative anesthesia time. Decreased operative duration lowers perioperative complication risks, an advantage that aligns well with outpatient and short-stay surgical pathways. Patients benefit from rapid tissue recovery, minimal postoperative discomfort, and early functional mobilization. By combining straightforward technical execution with durable natal cleft effacement, the procedure establishes a dependable benchmark for tertiary and secondary care hospitals alike.
How does this modified technique differ from a conventional parasacral perforator flap?
A conventional perforator flap requires skeletonizing individual vessels under optical magnification. In contrast, the modified approach intentionally keeps the flap base, its dominant perforator vessels, and the surrounding adipose tissue completely intact. This design avoids challenging microvascular dissection while safeguarding blood flow and facilitating straightforward tissue rotation.
Why is flattening the natal cleft essential in pilonidal sinus operations?
A deep natal cleft generates strong negative pressure and accumulates loose body hairs and perspiration. When surgeons transpose a vascularized flap across the cleft, they efface the deep midline groove and redirect scars laterally. This physical change removes mechanical friction, minimizes hair trapping, and reduces recurrence risks.
Which patient populations gain the greatest benefit from this reconstructive technique?
This procedure offers significant benefits for young, hirsute male patients who present with recurrent, complex, or extensive pilonidal sinus disease. Additionally, individuals who previously experienced midline wound breakdown or extensive tissue loss following secondary intention healing represent excellent candidates for this robust, well-vascularized tissue closure.
Disclaimer: This content is for informational and educational purposes only and should not be used as a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified healthcare provider with any questions you may have regarding a medical condition or procedure. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A modified parasacral perforator flap provides an easier, highly reproducible reconstructive option for pilonidal sinus disease. By preserving the base tissue and avoiding microvascular dissection, surgeons achieve robust flap survival, low complication rates, and zero recurrences in clinical evaluation.
Today

Healthcare resource cutbacks create severe organizational conditions that constrain moral agency, triggering moral distress across frontline clinicians and healthcare leaders. Addressing this crisis requires ethical leadership, relational solidarity, and transparent resource allocation frameworks.
Today

Maharashtra has initiated the appointment of two dedicated special public prosecutors in every district alongside a joint police-health SOP to fast-track PCPNDT and MTP cases. Medical imaging centers, radiologists, and obstetricians must strengthen statutory documentation and audit preparedness.
Today
A study in pediatric cardiology reveals that infants under two months require median enoxaparin doses of 2.13 mg/kg/dose, alongside more dose titrations and longer times to reach target anti-Xa levels compared to older children, underscoring the need for tailored dosing and aggressive monitoring.
Today
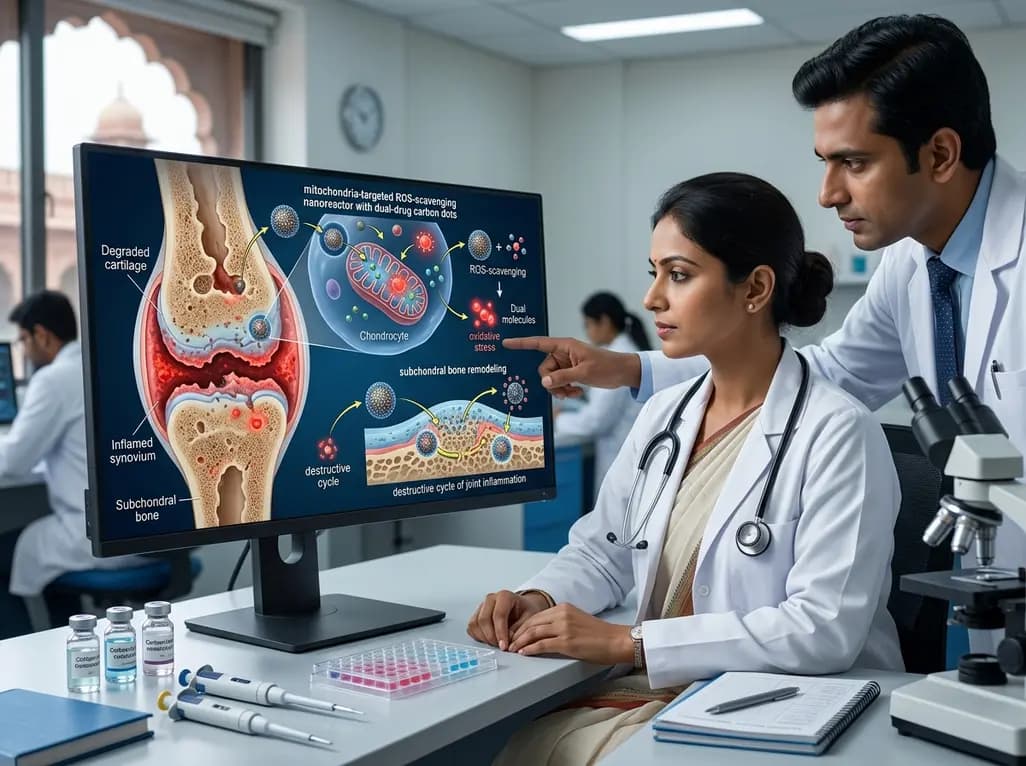
A novel mitochondria-targeted ROS-scavenging nanoreactor with dual-drug carbon dots provides a multi-mechanism strategy for osteoarthritis therapy. By neutralizing oxidative stress and remodeling subchondral bone, this platform breaks the destructive cycle of chronic joint inflammation and cartilage degeneration.
Today

An exploratory pilot study evaluates metoprolol pharmacokinetics across cisgender males, cisgender females, and transgender women on gender-affirming hormone therapy. Findings reveal distinct drug disposition trends, emphasizing the critical need for genotype-stratified research in transgender cardiovascular care.
Today
