

Loading, please wait...
Loading, please wait...

Understanding metoprolol pharmacokinetics across diverse patient populations remains a paramount clinical priority in contemporary cardiology and internal medicine. Clinicians routinely prescribe this cardioselective beta-blocker to treat hypertension, tachyarrhythmias, and ischemic heart disease. However, physiological determinants such as sex steroids, hepatic enzymatic clearance, and body composition can substantially alter systemic drug exposure. Historically, clinical pharmacological trials predominantly enrolled cisgender male participants, leaving notable evidence gaps regarding other populations. Consequently, healthcare providers frequently encounter unexplained therapeutic variability when managing regimens for female patients and transgender individuals. Transgender women receiving gender-affirming hormone therapy experience sustained alterations in sex steroid concentrations, adipose distribution, and hepatic blood flow. Therefore, evaluating drug disposition in this growing cohort provides essential foundational knowledge for personalized prescribing. While prior investigations identified sex-dependent clearance rates for several lipophilic agents, data specifically addressing transgender individuals on cross-sex hormones have remained exceedingly scarce. Because precise cardiovascular care hinges on predictable pharmacokinetics, researchers must investigate how hormonal regimens modulate hepatic drug handling. This initial inquiry underscores the urgent need to incorporate gender-diverse cohorts into cardiovascular pharmacology research.
To address this knowledge deficit, a recent exploratory pilot study investigated the single-dose disposition of oral metoprolol. Specifically, researchers enrolled nine healthy adult volunteers, assigning three participants to each of three distinct groups: cisgender males, cisgender females, and transgender women receiving gender-affirming hormone therapy. Each volunteer ingested a single 100 mg oral tablet of metoprolol, after which researchers collected serial venous blood samples across a 12-hour testing window. Investigators utilized high-performance liquid chromatography to measure plasma drug levels and modeled concentration profiles using non-compartmental pharmacokinetic principles. Descriptively, the mean area under the plasma concentration-time curve revealed notable differences across the cohorts. Cisgender males demonstrated the highest overall systemic exposure, reaching a mean area under the curve of 2550 ng·h/mL. In comparison, cisgender females showed a mean value of 2142 ng·h/mL. Interestingly, transgender women receiving hormone therapy exhibited a lower mean exposure of 1522 ng·h/mL. Peak plasma concentrations mirrored this downward trajectory, recording 418 ng/mL in cisgender males, 363 ng/mL in cisgender females, and 269 ng/mL in transgender participants. Hence, these descriptive measurements illustrate noticeable between-group variability in circulating drug concentrations.
Beyond peak exposure and overall bioavailability, the elimination kinetics also showed pronounced variations among the three cohorts. Specifically, the calculated elimination rate constants were 0.139 per hour in cisgender males and 0.140 per hour in cisgender females. In contrast, transgender women displayed a much faster elimination rate constant of 0.268 per hour. Furthermore, the mean elimination half-lives aligned with this pattern, averaging 4.98 hours in cisgender men, 4.92 hours in cisgender women, and 2.58 hours in transgender women. However, clinicians must interpret these physiological disparities with considerable scientific caution. Metoprolol undergoes extensive oxidative metabolism in the liver, driven predominantly by cytochrome P450 2D6. Because the CYP2D6 gene exhibits extreme genetic polymorphism, individual metabolic phenotypes range from poor to ultrarapid metabolizers. In this pilot investigation, researchers did not perform CYP2D6 phenotyping or genotyping. Therefore, clinicians cannot conclusively attribute the observed kinetic shifts to gender identity, biological sex, or exogenous hormone therapy alone. An unmeasured overrepresentation of ultrarapid CYP2D6 metabolizers within the transgender group could fully explain the elevated clearance. Thus, pharmacogenetic stratification remains an essential prerequisite for confirming these exploratory hypotheses in future trials.
Although genetic polymorphisms heavily govern beta-blocker breakdown, clinicians must also recognize how exogenous hormones directly alter drug disposition. Gender-affirming regimens for transgender women typically combine exogenous estrogens, such as oral or transdermal estradiol, with anti-androgens like spironolactone or cyproterone acetate. Estrogenic compounds exert complex regulatory effects on hepatic transcription factors and microsomal enzyme activity. Additionally, exogenous sex steroids alter the synthesis of circulating plasma proteins, including alpha-1-acid glycoprotein and albumin. Because metoprolol binds modestly to plasma proteins, variations in protein binding could potentially modulate the unbound fraction available for tissue distribution and hepatic extraction. Moreover, feminizing hormone therapy induces measurable shifts in body habitus over time, reducing visceral lean mass while increasing peripheral adipose tissue. Such morphological shifts naturally alter the apparent volume of distribution for lipophilic cardiovascular agents. Furthermore, oral estrogens undergo significant first-pass hepatic metabolism, potentially altering regional sinusoidal blood flow and drug transporter expression. Consequently, future pharmacokinetic protocols must systematically quantify serum estradiol and testosterone concentrations alongside drug levels. By measuring actual circulating hormone concentrations, researchers can isolate specific endocrine influences from baseline genetic enzymatic activity.
For practicing physicians, these exploratory findings provide crucial insights into individualized cardiovascular pharmacotherapy. Beta-blockers remain indispensable agents across cardiology clinics for hypertension, stable angina, and rate control in supraventricular tachycardias. When prescribing metoprolol to transgender women receiving gender-affirming hormone therapy, physicians should not rely on standardized assumptions regarding drug clearance. Instead, clinicians should implement rigorous symptom monitoring and objective hemodynamic assessments, tracking resting heart rate and blood pressure responses closely. If a patient on feminizing hormone therapy demonstrates rapid drug clearance, standard metoprolol doses might yield a shortened duration of therapeutic beta-blockade. Consequently, the patient might experience breakthrough palpitations, labile blood pressure, or inadequate chronotropic control toward the end of a typical dosing interval. In such scenarios, clinicians may consider titrating the dose, switching to an extended-release formulation, or selecting an alternate beta-blocker that does not rely exclusively on CYP2D6 metabolism, such as atenolol or bisoprolol. Furthermore, clinicians must evaluate potential drug-drug interactions, particularly when anti-androgens or adjunct medications share competitive metabolic pathways. Ultimately, proactive hemodynamic assessment ensures optimal therapeutic efficacy while preventing unexpected adverse events.
Cytochrome P450 2D6 metabolizes the vast majority of circulating metoprolol, and genetic polymorphisms produce wide variations in metabolic clearance. Individuals carrying poor metabolizer alleles experience prolonged drug exposure, whereas ultrarapid metabolizers clear the drug very swiftly. Without baseline genotyping, researchers cannot ascertain whether altered drug concentrations stem from hormone therapy or underlying inherited enzymatic activity. Therefore, rigorous CYP2D6 phenotyping remains mandatory to isolate hormonal influences on drug metabolism.
Gender-affirming hormone therapy introduces exogenous estrogens and anti-androgens that can substantially modify physiological drug handling. These hormonal agents alter hepatic cytochrome enzyme expression, modulate drug-binding plasma proteins, and adjust hepatic blood clearance. Additionally, feminizing therapy systematically redistributes body mass, increasing peripheral adipose tissue and decreasing lean muscle volume. Consequently, these systemic changes modify the drug's apparent volume of distribution and clearance rates, potentially altering both therapeutic efficacy and cardiovascular outcomes.
When patients on gender-affirming therapy display suboptimal cardiovascular control on metoprolol, clinicians should first evaluate adherence and dosing timing. If breakthrough tachycardia or elevated blood pressure persists, doctors can consider switching to extended-release metoprolol succinate to smooth plasma fluctuations. Alternatively, clinicians may substitute beta-blockers whose clearance does not depend heavily on CYP2D6 pathways, such as bisoprolol, nadolol, or atenolol. Regular monitoring of resting heart rate and blood pressure ensures safe therapy.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





An exploratory pilot study evaluates metoprolol pharmacokinetics across cisgender males, cisgender females, and transgender women on gender-affirming hormone therapy. Findings reveal distinct drug disposition trends, emphasizing the critical need for genotype-stratified research in transgender cardiovascular care.
Today

Maharashtra has initiated the appointment of two dedicated special public prosecutors in every district alongside a joint police-health SOP to fast-track PCPNDT and MTP cases. Medical imaging centers, radiologists, and obstetricians must strengthen statutory documentation and audit preparedness.
Today
A prospective study evaluates percutaneous renal denervation in high-risk patients with resistant hypertension, demonstrating significant short-term blood pressure reduction alongside notable procedural considerations.
Today
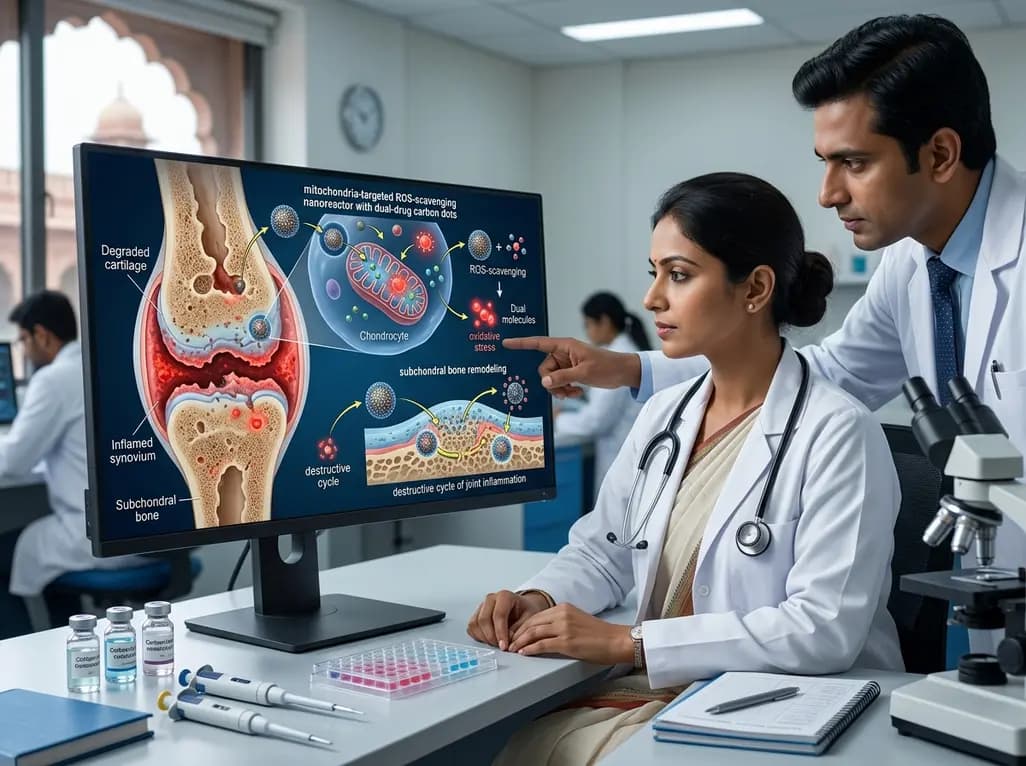
A novel mitochondria-targeted ROS-scavenging nanoreactor with dual-drug carbon dots provides a multi-mechanism strategy for osteoarthritis therapy. By neutralizing oxidative stress and remodeling subchondral bone, this platform breaks the destructive cycle of chronic joint inflammation and cartilage degeneration.
Today

A modified Delphi study identified crucial clinical and research priorities for older transgender adults. Key findings emphasize provider education, screening for social isolation, navigation of community resources, and long-term evaluation of gender-affirming hormone therapy safety during the aging process.
Today
