

Loading, please wait...
Loading, please wait...

Cellular metabolism plays a pivotal role in maintaining tissue homeostasis and driving clinical responses across complex human diseases. However, bulk metabolite abundance alone fails to explain why cellular stress triggers adaptive recovery in some tissues while driving regulated cell death in others. A groundbreaking paradigm reveals that mitochondrial quality control serves as an intermediate gating layer linking metabolic signals directly to cell fate. Mitochondria actively integrate substrate flux, receptor signaling, redox states, and covalent acylation. Consequently, the organelle determines whether a stressed cell initiates protective repair mechanisms or undergoes programmed death. Understanding these bioenergetic checkpoints offers vital insights into cardiology, oncology, and critical care medicine. Furthermore, this regulatory axis explains why conventional metabolic biomarkers often fail to forecast patient trajectories accurately.
Mitochondria function far beyond simple cellular powerplants. Instead, they serve as master decision hubs coordinating cellular survival and regulated cell death. The concept of mitochondrial quality control encompasses an integrated surveillance network of biogenesis, dynamic fusion and fission, proteostasis, and mitophagy. When cellular stressors alter local substrate concentrations, this gating layer evaluates structural and functional organellar reserves. Consequently, cells do not succumb to lethal cascades simply because circulating metabolite levels change. Rather, mitochondrial quality control determines whether metabolic signals trigger adaptive repair or fatal permeabilization. For example, robust fusion events allow healthy organelles to complement damaged neighbors and dilute biochemical insults. Conversely, selective fission isolates irreversibly injured fragments for lysosomal degradation. When acute stress overwhelms these dynamic clearance mechanisms, pro-death effectors rapidly assemble on the outer membrane. Therefore, this organellar surveillance network acts as a decisive checkpoint between physiological recovery and irreversible cell death.
Four distinct intermediate metabolites illustrate how metabolic inputs govern organellar surveillance: beta-hydroxybutyrate, lactate, succinate, and acetate. Each molecule operates through distinct biochemical modalities, spanning fuel utilization, surface receptor signaling, redox balance, and post-translational modification. For instance, beta-hydroxybutyrate serves as an alternative oxidative fuel and a potent epigenetic modifier. By inhibiting histone deacetylases, this ketone body enhances antioxidant defenses and bolsters mitochondrial resilience during nutrient deprivation. Meanwhile, lactate functions as an active signaling molecule rather than an inert metabolic byproduct. It enters mitochondria to alter redox equilibrium, modulate cytosolic acidity, and direct autophagic flux. In contrast, succinate accumulation frequently drives reverse electron transport at respiratory complex I. This mechanism generates bursts of reactive oxygen species that accelerate organelle fragmentation and sensitize cells to permeability transition. Finally, acetate modulates cellular longevity through acetyl-CoA synthesis, which fuels extensive protein acetylation across mitochondrial metabolic enzymes. Therefore, these four distinct metabolites demonstrate how biochemical pathways converge upon specific mitochondrial nodes to govern survival.
Organelle survival relies extensively on a delicate balance between biogenesis and selective autophagic removal, known as mitophagy. When metabolic perturbations generate excessive reactive oxygen species, oxidative stress damages structural proteins and cardiolipin. Consequently, the organellar membrane loses its electrochemical gradient, which stabilizes serine/threonine kinases on the outer mitochondrial membrane. These activated kinases recruit cytosolic ubiquitin ligases, systematically marking defective mitochondria for lysosomal destruction. Through this selective purging mechanism, cells eliminate leaking organelles before they release lethal pro-apoptotic signals into the cytosol. Furthermore, healthy cells counterbalance mitophagy by initiating mitochondrial biogenesis through nuclear transcriptional coactivators. This synchronized renewal ensures an adequate supply of competent organelles to sustain cellular bioenergetics. However, chronic metabolic overload or severe ischemia disrupts this protective equilibrium. When mitophagy fails to clear damaged organelles, ruptured mitochondria spill cytochrome c and mitochondrial DNA into the cytoplasm. These released components directly activate caspase cascades and inflammatory inflammasomes. Thus, maintaining tight redox balance and organellar turnover preserves structural competence and prevents inappropriate cell death.
A central insight from modern metabolic research demonstrates that identical metabolite concentrations produce vastly different outcomes across distinct human tissues. For example, high lactate concentrations support energetic resilience and functional recovery in working cardiomyocytes during exertion. Conversely, similar lactate concentrations accelerate ischemic injury and promote regulated cell death within vulnerable cerebral neurons. This paradox highlights why clinicians cannot evaluate metabolic health through static blood measurements alone. Instead, cell fate depends on tissue-specific metabolic flux and existing mitochondrial quality control reserves. High-flux organs, including the heart, liver, and kidneys, maintain specialized enzymatic machinery to buffer metabolic swings. These organs sustain robust mitophagy and fusion dynamics, which permits efficient adaptation under stress. In contrast, tissues with limited bioenergetic flexibility quickly cross lethal activation thresholds when exposed to identical biochemical insults. Moreover, exposure timing significantly modifies cellular outcomes. Transient metabolite spikes often trigger beneficial preconditioning, whereas chronic accumulation drives organelle decay. Consequently, physicians must interpret metabolic parameters within the precise physiological context of individual tissue types.
Translating these organellar principles into modern clinical practice offers unprecedented opportunities for precision pharmacology and targeted interventions. Historically, therapeutic strategies focused primarily on altering total metabolite pools, yet these efforts often produced inconsistent outcomes in clinical trials. Current experimental models demonstrate that selectively manipulating mitochondrial quality control nodes restores tissue resilience far more effectively. Specifically, small molecules that stimulate selective mitophagy or preserve mitochondrial dynamics can halt pathological regulated cell death. In acute conditions like myocardial infarction and acute kidney injury, preserving organellar integrity restricts lethal reperfusion cascades. Similarly, oncology specialists can exploit these vulnerabilities by disrupting mitochondrial quality control in malignant cells, thereby lowering their resistance to chemotherapy. Clinicians in critical care can also utilize dynamic metabolic profiles to monitor organ dysfunction and predict patient recovery. Furthermore, designing mechanism-enriched human clinical trials will allow investigators to evaluate target engagement alongside functional cellular responses. As researchers validate these organelle-directed therapies, medicine will move closer toward personalized treatments that correct fundamental cellular defects.
Bulk cellular metabolism describes the overall biochemical generation and breakdown of metabolites throughout the entire cell. In contrast, mitochondrial quality control operates as an organelle-specific surveillance network that manages structural integrity, dynamic fusion, fission, and targeted mitophagy. Consequently, while general metabolism reflects substrate availability, mitochondrial quality control determines whether an organelle survives stress or triggers regulated cell death cascades. Thus, it acts as an intermediate gating layer governing cellular viability.
Tissue-specific responses depend primarily on local metabolic flux and basal organelle quality control capacity. For instance, high-energy tissues like the myocardium possess extensive antioxidant networks and robust mitophagy pathways that efficiently buffer transient metabolite spikes. In contrast, tissues with limited clearance capacity quickly experience oxidative overload and membrane permeability transition under identical exposures. Therefore, local organellar resilience, rather than total metabolite abundance, dictates whether a cell adapts successfully or undergoes regulated death.
Targeting these pathways enables clinicians to prevent tissue loss in acute ischemia-reperfusion injuries, neurodegeneration, and septic shock by preserving organellar integrity. Conversely, selectively inhibiting mitochondrial quality control in malignant cells eliminates their chemotherapy resistance, thereby promoting tumor apoptosis. Furthermore, measuring dynamic mitochondrial turnover in human trials will provide predictive biomarkers that improve patient stratification beyond conventional static blood tests. Consequently, this therapeutic strategy holds immense potential for individualized medicine across critical care and oncology.
Disclaimer: This content is for informational and educational purposes only and is not intended as medical advice. Healthcare professionals should make decisions based on individualized patient assessments, institutional protocols, and current clinical guidelines. Refer to the latest local and national guidelines for clinical practice.
References
Hu J et al. Metabolite Regulation of Mitochondrial Quality Control and Regulated Cell Death. Antioxid Redox Signal. 2026 Sep 25. doi: 10.1177/15230864261490413. PMID: 42791195.
Liu Z, Hu W, Sun L, Liu H. Mitochondrial quality control in health and disease: Updates 2026. Chin Med J (Engl). 2026 Jun 24. doi: 10.1097/CM9.0000000000004169. PMID: 42343697.
Wang Y, Zhang X, Chen Y, Liu M. Mitochondrial Quality Control and Cell Death: Mechanisms and Therapeutic Perspectives. Int J Mol Sci. 2025 Nov 16;26(22):11084. doi: 10.3390/ijms262211084. PMID: 41303566.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A groundbreaking review highlights mitochondrial quality control as a pivotal gating layer between metabolite signaling and regulated cell death, offering transformative therapeutic avenues across cardiology, oncology, and critical care.
Today

A large retrospective study evaluates the screening accuracy, positive predictive value, and test failure rates of noninvasive prenatal testing (NIPT) in assisted reproductive technology (ART) pregnancies compared to spontaneous conceptions, highlighting key considerations for pretest counseling.
Today

Differential oxygenation during peripheral TA-NRP can cause undetected coronary hypoxemia due to arch vessel clamping. A novel circuit with continuous aortic root monitoring detects desaturation early, facilitating left ventricular unloading and preventing allograft dysfunction and unnecessary heart discard.
Today
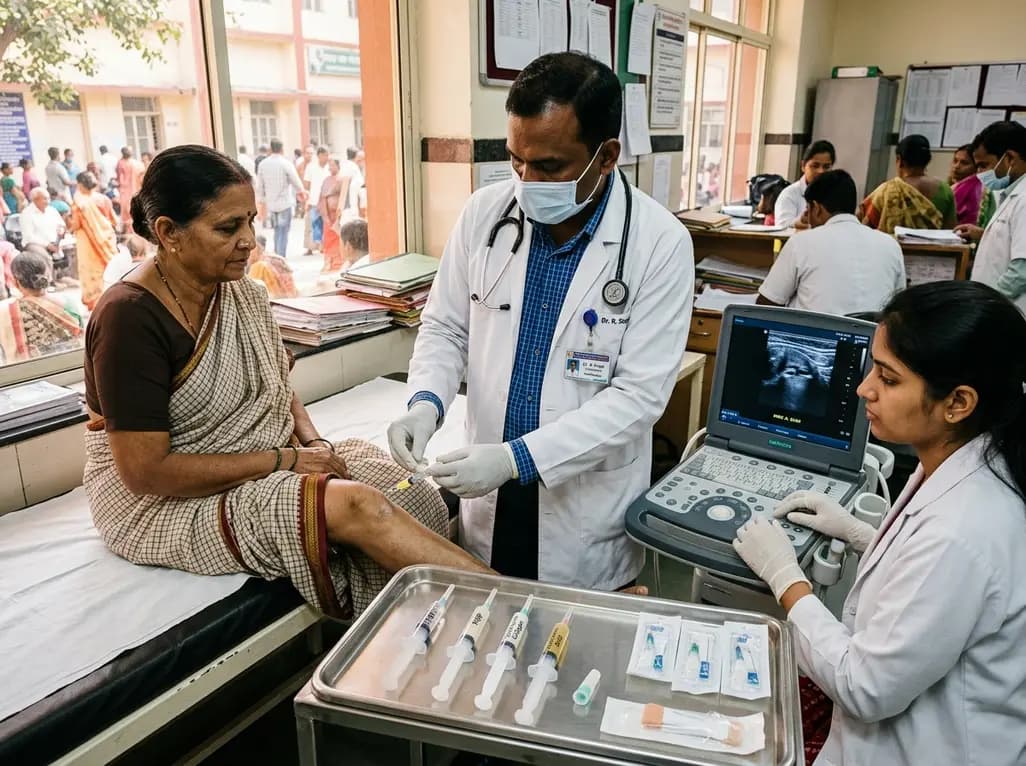
A randomized controlled trial compared ultrasound-guided intra-articular injections of PRP, hydrolyzed type I collagen, and hyaluronic acid in knee osteoarthritis. All therapies demonstrated significant improvements in WOMAC and pain scores at six months, supporting hydrolyzed collagen as a viable biological option.
Today

A scoping review evaluates 116 studies on AI in women's reproductive health, finding that 83.6% carry high risk of bias. While ensemble models show promise, disparities and lack of validation hinder LMIC deployment.
Today
