

Loading, please wait...
Loading, please wait...

Clinicians frequently manage closed head trauma in school-aged children and adolescents. However, evaluating subtle neurocognitive impairment remains an enduring challenge in acute emergency care. Pediatric mild traumatic brain injury represents one of the most common causes of sustained cognitive complaints in youth. Although conventional structural computed tomography and magnetic resonance imaging typically appear normal, young patients repeatedly struggle with attention and working memory. Consequently, identifying objective functional imaging markers is critical for modern pediatrics and pediatric neurology. Emerging electrophysiological tools now offer unprecedented insight into post-injury neural communication.
Emergency physicians and pediatricians routinely encounter children who sustain concussions during sports activities, falls, or road collisions. While most physical symptoms resolve rapidly, cognitive deficits often persist for months. Specifically, parents and teachers report that recovering children exhibit difficulties with concentration, mental speed, and multitasking. Conventional neurological examinations frequently fail to detect these subtle working memory impairments. In addition, standard neuroimaging modalities lack the sensitivity needed to capture microscopic axonal disruption or altered oscillatory dynamics. Therefore, clinicians must frequently rely on subjective questionnaires and symptom rating scales to guide recovery. Unfortunately, subjective reports vary substantially across pediatric patients and their guardians. Moreover, academic demands can quickly overwhelm an injured child whose neural processing speed remains impaired. As a result, young individuals may experience school performance declines, heightened anxiety, and persistent behavioral changes. Consequently, healthcare providers need objective, reliable functional biomarkers that directly reflect injured brain circuitry. Developing these non-invasive diagnostic strategies will significantly improve acute risk stratification and help prevent premature clearance for contact sports or intensive cognitive strain.
To uncover subtle cerebral network alterations, investigators deployed advanced magnetoencephalography during a standardized cognitive challenge. Specifically, magnetoencephalography captures millisecond-level electrophysiological signals from active cortical assemblies with superior temporal and spatial precision. In a recent prospective investigation, clinicians recruited children aged 8 to 15 years within three weeks of emergency department presentation. The cohort compared sixty patients sustaining head injury against thirty-seven controls with isolated orthopedic trauma. Furthermore, researchers evaluated participants using an established N-back working memory task during recording sessions. This behavioral paradigm requires children to monitor a continuous sequence of visual stimuli and identify items matching preceding presentations. Consequently, the task directly tests the child's real-time maintenance and manipulation of information. By measuring neural responses across alpha, beta, gamma, theta, and delta oscillatory bands, the imaging protocol reconstructed precise source-magnitude maps. Importantly, this electrophysiological technique circumvents the hemodynamic delays inherent in functional magnetic resonance imaging. Thus, the paradigm delivers a highly sensitive physiological assessment of working memory networks during the crucial subacute phase of pediatric recovery.
The investigation revealed striking neurofunctional differences between injured children and orthopedic controls across multiple frequency spectra. Most notably, injured patients displayed pronounced signal reductions, or hypoactivity, within core nodes of the working memory network. These suppressed cortical regions specifically included the dorsolateral prefrontal cortex, the anterior cingulate cortex, and the supramarginal gyrus. However, the data simultaneously revealed a paradoxical pattern of localized hyperactivity outside the primary working memory circuitry. Specifically, injured children exhibited marked over-recruitment across the frontal pole and ventromedial prefrontal cortex. Clinicians interpret this secondary hyperactivation as a compensatory physiological response to primary network breakdown. Furthermore, researchers discovered that abnormal signal magnitude in the dorsolateral prefrontal cortex and supramarginal gyrus correlated directly with longitudinal symptom trajectories. Children demonstrating greater initial network dysregulation experienced more pronounced symptom changes between three weeks and three months post-injury. Accordingly, these regional electromagnetic deviations reflect true underlying neurobiological disruptions rather than random cognitive fatigue. In summary, the distinctive coexistence of core hypoactivation and frontal compensatory over-recruitment establishes an objective signature of post-concussive network disorganization.
Understanding the underlying cellular pathophysiology is essential for developing targeted therapeutic strategies for pediatric brain trauma. Traumatic mechanical acceleration and deceleration forces exert diffuse shearing stress across fragile pediatric cortical microstructures. Consequently, gamma-aminobutyric acid inhibitory interneurons sustain significant vulnerability during these rotational impact events. These specialized GABAergic interneurons normally generate rhythmic inhibitory currents that synchronize regional pyramidal cell firing. When mechanical trauma injures these cells, regional network disinhibition inevitably follows. Therefore, injured neural assemblies lose their capacity to generate the synchronized oscillatory bursts required for working memory processing. This loss of rhythmic stimulus-evoked synchronization explains the profound hypoactivity observed within the dorsolateral prefrontal cortex and supramarginal gyrus. Meanwhile, the uninjured frontal pole attempts to compensate for this signaling deficit by elevating baseline recruitment. In addition, secondary metabolic derangements, including excessive glutamate release and transient mitochondrial strain, further exacerbate local interneuron dysfunction. As a result, the young brain faces an energetic crisis while attempting to perform standard mental tasks. Thus, restoring GABAergic inhibitory balance represents an intriguing biological target for future pharmacological and rehabilitative research.
These functional neuroimaging discoveries offer valuable practical lessons for managing pediatric patients in clinical and community settings. First, healthcare providers must recognize that subjective cognitive complaints after head injury reflect genuine neurophysiological disruption. Therefore, pediatricians should resist dismissing memory difficulties when standard structural scans show unremarkable results. Second, clinicians can utilize these insights to formulate realistic, individualized return-to-learn and return-to-play protocols. Because frontal networks must work harder to compensate for injured circuits, premature academic overload may worsen clinical exhaustion. Additionally, schools should provide temporary accommodations, such as extended examination times, reduced homework volumes, and frequent cognitive rest breaks. Furthermore, primary care clinicians and neurologists must coordinate closely to monitor symptomatic recovery over the first three months. If working memory deficits persist beyond this acute window, formal neuropsychological assessment becomes vital. In the future, advanced magnetoencephalography may serve as a routine diagnostic marker to track objective neural healing. Ultimately, integrating advanced electrophysiological markers into pediatric concussion management will enhance clinical precision, prevent secondary reinjury, and ensure safer developmental outcomes for affected youth.
Magnetoencephalography measures millisecond-level magnetic signals generated by synchronized neuronal currents in the brain. During cognitive challenges like the N-back task, it pinpoints localized hypoactivity within working memory hubs alongside compensatory frontal hyperactivity. Consequently, this high-resolution modality reveals physiological network disruption that standard structural imaging modalities fail to detect.
Rotational shearing forces during head injury selectively damage vulnerable GABAergic inhibitory interneurons across cortical circuits. Consequently, this mechanical trauma disrupts synchronized oscillatory signaling within the dorsolateral prefrontal cortex and supramarginal gyrus. Because the primary working memory network fails to coordinate properly, children experience noticeable difficulty retaining and manipulating information.
Clinicians should validate patient symptoms and implement structured return-to-learn accommodations, including shortened study sessions and frequent mental breaks. Furthermore, doctors must monitor clinical progression across the initial three months post-injury. If cognitive impairment persists, referral for comprehensive neuropsychological assessment and targeted cognitive rehabilitation is strongly warranted.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A prospective magnetoencephalography study demonstrates working memory network hypoactivation and compensatory frontal recruitment in pediatric mild traumatic brain injury, offering an objective functional biomarker for persistent post-concussive symptoms.
Today
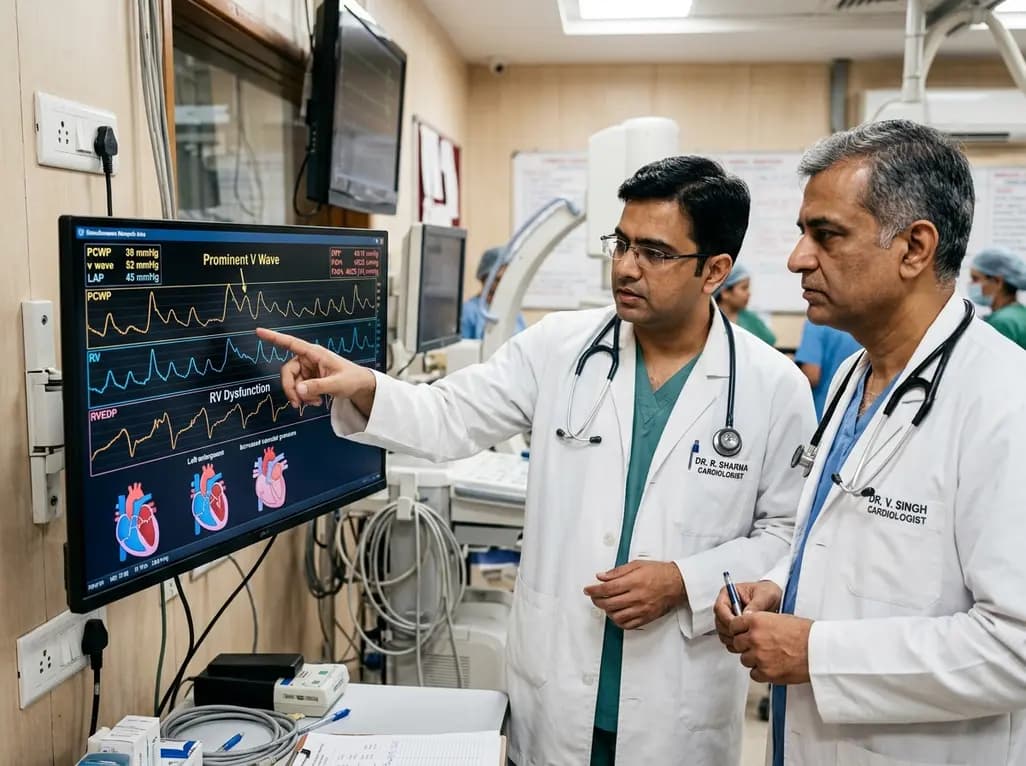
Left atrial stiffening generates prominent V waves that pressurize the pulmonary circulation and augment right ventricular afterload independently of intrinsic pulmonary vascular disease in patients with heart failure with preserved ejection fraction.
Today

A meta-analysis demonstrates that secondhand smoke exposure significantly elevates fetal loss risk by 21% among nonsmoking pregnant women. Clinicians must implement household screening and family-centered cessation interventions to prevent avoidable miscarriages and stillbirths.
Today

Preclinical validation demonstrates that a novel contact force-integrated pulsed field quantization index accurately predicts lesion depth in real time, achieving 100% durable pulmonary vein isolation without collateral injury.
Today
A new cross-sectional evaluation reveals how regional lean mass and bone mineral content interact in resistance-trained men, showing that whole-body size and allometric scaling explain shared musculoskeletal phenotypes and strength relationships.
Today

Explore the emerging role of glucose metabolic reprogramming in exercise-attenuated osteoporosis, examining how physical activity influences osteoblast glycolysis, osteoclast bioenergetics, and skeletal remodeling pathways to improve bone mineral density.
Today
