

Loading, please wait...
Loading, please wait...
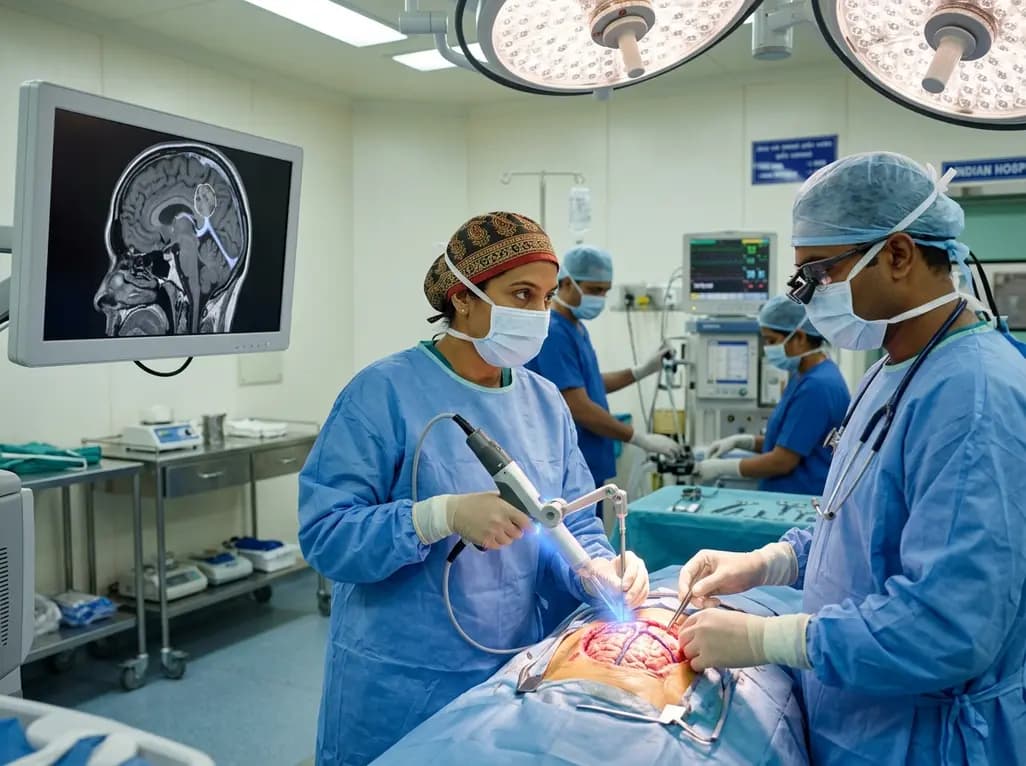
Surgical resection remains a primary therapeutic intervention for symptomatic or solitary brain metastases. However, achieving durable local cavity control requires effective adjuvant radiation. Neurosurgeons and radiation oncologists frequently rely on postoperative stereotactic radiosurgery to eliminate residual microscopic tumor cells. In recent years, intraoperative radiotherapy has gained considerable attention as an efficient alternative. Delivering a single high-precision radiation dose directly to the tumor bed during surgery eliminates scheduling delays. Furthermore, this approach spares vulnerable cancer patients from prolonged outpatient treatment courses. Despite these clear logistical advantages, clinicians often express valid concerns regarding complications when tumors sit adjacent to major dural venous sinuses. Specifically, practitioners worry that delivering high focal radiation doses near the superior sagittal or transverse sinuses might induce local vascular injury, intraluminal endothelial damage, and subsequent thrombosis. Consequently, evaluating intraoperative radiotherapy sinus thrombosis risks is crucial for expanding this technique safely into complex anatomical regions. A pioneering study published in the Journal of Neuro-Oncology directly tackles this clinical dilemma by assessing whether intraoperative irradiation increases cerebral venous occlusions compared to stereotactic radiosurgery.
The research team performed a comprehensive retrospective comparative analysis of 166 consecutive patients who underwent surgical resection for histologically confirmed brain metastases. Among this overall cohort, 71 patients received intraoperative radiotherapy immediately following surgical resection. Meanwhile, 95 patients underwent standard postoperative adjuvant stereotactic radiosurgery. The investigators meticulously documented key anatomical and treatment-related variables for every individual. These clinical parameters included precise tumor location, immediate proximity to major dural venous sinuses, postoperative imaging timing, and the presence of sinus vein thrombosis on contrast-enhanced neuroimaging. Additionally, for patients in the stereotactic radiosurgery group, the team documented the interval between surgical tumor resection and the initiation of radiation therapy. Routine magnetic resonance imaging or computed tomography venography served as the diagnostic standard for identifying intraluminal filling defects. Importantly, the researchers stratified patients by anatomical sinus proximity. This careful stratification enabled a direct, unbiased comparison between treatment modalities. Thus, the methodological structure provided clear insights into the true vascular impact of immediate cavity irradiation.
The study results provide strong reassurance regarding the vascular safety of both treatment strategies. Postoperative sinus vein thrombosis occurred in only 5 out of the 166 analyzed patients, representing an overall incidence of 3.0%. When examining the two treatment modalities separately, the authors found no statistically significant difference in thrombosis frequency. In the intraoperative radiotherapy cohort, sinus vein thrombosis developed in 2 patients (2.8%). Similarly, in the postoperative stereotactic radiosurgery cohort, thrombosis occurred in 3 patients (3.2%). A comparative statistical assessment confirmed equivalent safety profiles between both groups. Furthermore, all five thrombosis events occurred exclusively in patients with lesions situated directly adjacent to dural venous sinuses. Crucially, every identified case of thrombosis remained clinically asymptomatic throughout the observation period. Follow-up imaging demonstrated that the time elapsed from surgery to initial neuroimaging did not differ significantly between the two groups. In addition, the time from surgery to imaging and the radiation interval showed no significant differences between patients who developed thrombosis and those who did not.
Surgical manipulation near major intracranial venous structures naturally carries an inherent baseline risk of mechanical vessel trauma, local edema, and transient stasis. When clinicians introduce ionizing radiation to the surgical bed, theoretical concerns arise regarding acute endothelial swelling, microvascular obliteration, and prothrombotic cascades. However, the findings from this landmark study indicate that focal intraoperative irradiation does not amplify this baseline surgical risk. Several radiobiological factors likely contribute to this favorable outcome. Modern low-energy X-ray intraoperative radiotherapy systems deliver steep dose gradients. The radiation dose attenuates rapidly within adjacent normal tissues, which limits high-dose exposure to the deep endothelial lining of large venous channels. Moreover, the rapid completion of single-session irradiation avoids repetitive vascular injury that might otherwise occur during fractionated regimens. Because all recorded thrombotic events in the study occurred solely in sinus-adjacent tumors, anatomical proximity and surgical manipulation appear to drive the baseline risk far more than the specific radiation technique applied.
Beyond establishing vascular safety, intraoperative radiotherapy offers profound clinical benefits for patients battling metastatic brain disease. Conventional postoperative stereotactic radiosurgery typically requires an interval of three to four weeks post-resection to permit adequate surgical wound healing. Unfortunately, this mandatory waiting period delays the resumption of vital systemic treatments, including cytotoxic chemotherapy, targeted molecular therapies, and immune checkpoint inhibitors. In contrast, intraoperative radiotherapy delivers definitive local cavity treatment at the exact moment of surgical resection. Consequently, oncologists can reintroduce systemic therapies significantly sooner, effectively curbing distant systemic progression. Furthermore, intraoperative delivery eliminates the risk of cavity volume alterations that frequently complicate postoperative stereotactic radiosurgery planning. Postoperative resection cavities often collapse or expand dynamically, creating geometric uncertainties during target volume delineation. Single-session intraoperative treatment bypasses these contouring challenges while simultaneously reducing hospital visits. Thus, intraoperative radiotherapy harmonizes local cavity control with holistic oncologic disease management.
These findings offer valuable guidance for multidisciplinary neuro-oncology teams evaluating therapeutic options for sinus-adjacent brain metastases. Neurosurgeons should no longer consider proximity to major dural sinuses as an absolute contraindication to intraoperative radiotherapy. Instead, surgical teams can confidently select intraoperative treatment when clinical, systemic, and anatomical considerations favor immediate single-session delivery. Nevertheless, maintaining meticulous surgical technique remains paramount during sinus dissection to minimize direct mechanical trauma and intraluminal endothelial disruption. In addition, clinicians should implement standardized postoperative neuroimaging protocols for high-risk sinus-adjacent resections. Routine contrast-enhanced magnetic resonance venography ensures early detection of subclinical venous filling defects. Because all thromboses in this trial remained asymptomatic, conservative observation without aggressive therapeutic anticoagulation proved effective for stable subclinical cases. Multidisciplinary tumor boards should actively integrate these safety insights when customizing personalized local treatment pathways.
The risk of cerebral sinus vein thrombosis with intraoperative radiotherapy is approximately 2.8%, which matches the 3.2% rate seen with stereotactic radiosurgery. Clinical data show that intraoperative radiation does not significantly increase vascular occlusion rates compared to conventional postoperative radiation options.
In clinical trials evaluating sinus-adjacent brain metastasis treatments, postoperative sinus vein thrombosis cases remained entirely asymptomatic. These incidental filling defects were discovered on surveillance neuroimaging and did not produce neurological deficits, intracranial hypertension, or need emergency surgical thrombectomy procedures.
Intraoperative radiotherapy delivers definitive single-fraction cavity irradiation during surgery, preventing treatment delays to systemic chemotherapy and immunotherapy. Its steep dose falloff protects adjacent healthy tissue, while sparing patients from multiple postoperative hospital visits and complex stereotactic cavity contouring uncertainties.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals must exercise independent clinical judgment and verify information against established scientific literature and clinical guidelines. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study in the Journal of Neuro-Oncology demonstrates that intraoperative radiotherapy does not increase the risk of cerebral sinus vein thrombosis compared to postoperative stereotactic radiosurgery in patients with sinus-adjacent brain metastases.
last month

Ceftriaxone therapy can lead to biliary sludge and gallstone formation due to calcium-ceftriaxone precipitation. A recent cohort study shows that the noninvasive Fibrosis-4 (FIB-4) index, alongside treatment duration, independently predicts lithogenesis, enabling proactive risk stratification.
Today

A multiparametric MRI approach combining quantitative T2 shading, apparent diffusion coefficient (ADC) measurements, and morphological signs provides superior diagnostic accuracy over subjective evaluation to differentiate ovarian endometriomas from benign hemorrhagic cysts.
Today
A landmark case report reveals a donor heart beating for a century in a 63-year-old recipient, challenging conventional age limits in cardiac transplantation and offering critical lessons on organ longevity, donor selection, and long-term graft survival.
Today
A propensity-matched analysis reveals that patients undergoing total hip arthroplasty on maintenance dialysis experience significantly higher rates of adverse events, periprosthetic infection, and revision surgery at 90 days, 2 years, and 5 years compared to non-dialysis peers.
Today

New research reveals that M1 macrophage-derived exosomes aggravate diabetic nephropathy by transferring WTAP to stabilize S1PR2 mRNA. Silencing WTAP in these vesicles attenuates endothelial injury and renal fibrosis, pointing toward innovative nanomedicine therapies.
Yesterday
