

Loading, please wait...
Loading, please wait...

Providing compassionate reproductive healthcare requires clinicians to understand the psychological burdens of pregnancy termination. In clinical practice, internalized abortion stigma represents an insidious burden. Individuals frequently absorb sociocultural taboos and turn harsh judgments inward. Consequently, women often perceive themselves as morally compromised or socially deviant. This distress occurs even when they access services within lawful public facilities. A recent cross-sectional study demonstrates that internalized abortion stigma persists across diverse demographics. For obstetricians and physicians, recognizing this hidden distress is vital. Specifically, self-directed shame impairs post-procedure recovery and future healthcare engagement. Moreover, patients carrying guilt often delay critical follow-up consultations. As a result, clinical risks such as undetected infection or hemorrhage escalate significantly. Healthcare practitioners must therefore realize that procedural success does not guarantee emotional resolution. When clinicians provide empathetic care, they actively dismantle destructive self-blame. In addition, validating abortion as standard healthcare restores personal dignity. Furthermore, supportive communication fosters patient autonomy during future reproductive planning. Therefore, compassionate consultation remains a cornerstone of comprehensive post-abortion management. Notably, early emotional validation prevents long-term depressive symptoms and chronic distress.
The evaluated study examined women receiving legal abortion services at a public hospital. Researchers gathered data within six hours following the clinical procedure. The participant cohort demonstrated an average age of approximately thirty-one years. In addition, fifty-five percent of participants had completed only primary education. Furthermore, sixty-two percent underwent termination specifically for maternal health indications. Notably, statistical analyses revealed no significant differences in stigma across demographic categories. Educational level, marital education, household income, and employment status did not alter stigma scores. Similarly, the number of living children and conception methods showed no significant correlation. Prior abortion history and time since previous procedures also showed negligible statistical impact. However, researchers identified a weak negative correlation between patient age and judgment concerns. Consequently, younger women exhibited greater apprehension regarding social criticism and personal condemnation. Most importantly, participants universally registered their highest distress scores regarding perceived societal judgment. These findings confirm that internalized abortion stigma operates independently of socioeconomic status. Therefore, clinicians cannot assume that educated or affluent patients experience less emotional distress. Instead, healthcare teams must anticipate profound judgment concerns across every patient demographic.
Researchers utilized the Individual Level Abortion Stigma Scale alongside standardized demographic forms. This validated instrument measures internalized shame, perceived community judgment, and recurring secrecy needs. Societal conditioning frequently equates reproductive choices with moral worth. Consequently, many patients internalize external societal disapproval into intense personal guilt. This internal psychological conflict often forces individuals into acute emotional isolation. Furthermore, women deliberately withhold their medical history from partners, friends, and family. The study data demonstrate that fear of negative evaluation dominates the post-abortion period. In addition, high secrecy scores strongly correlate with acute anxiety and depressive symptoms. Patients who conceal their abortions frequently experience sleep disturbances and emotional hypervigilance. Therefore, identifying these psychological dimensions during initial consultations proves clinically essential. Clinicians can utilize ILASS domains to guide empathetic pre-discharge bedside conversations. Moreover, structured psychological screening illuminates hidden distress that physical examinations routinely overlook. By normalizing emotional vulnerability, healthcare providers actively alleviate distressing feelings of alienation. As a result, patients regain emotional equilibrium alongside uneventful physiological healing. Thus, validated psychological assessment strengthens overall post-abortion clinical care protocols.
In India, reproductive healthcare functions under the progressive Medical Termination of Pregnancy Amendment Act. This statute provides clear legal authorization for terminating unintended or clinically complicated pregnancies. Nevertheless, cultural taboos persist across both urban centers and rural communities. Consequently, Indian women frequently experience intense internalized abortion stigma despite statutory legality. Deep-rooted patriarchal expectations often lead women to view pregnancy termination as moral failure. Furthermore, unmarried individuals and adolescents face severe social condemnation from conservative local communities. These punitive social attitudes compel many women to seek secretive, unsafe termination alternatives. In addition, patients frequently fear that medical facilities will breach personal confidentiality. The amended MTP Act explicitly mandates strict privacy protections for every registered patient. Therefore, Indian obstetricians and primary healthcare doctors must actively communicate these legal safeguards. Clinicians must assure patients that healthcare consultations remain strictly private and confidential. Moreover, doctors must dismantle perceived institutional hostility through respectful, reassuring clinical engagement. When physicians champion nonjudgmental care, they eliminate significant barriers to legal reproductive services. Accordingly, medical practitioners play a pivotal role in operationalizing reproductive justice across India.
Healthcare facilities must implement actionable protocols to mitigate internalized abortion stigma effectively. First, clinicians should standardize communication practices to eliminate moralizing or accusatory interview questions. Physicians must never interrogate patients regarding personal contraceptive choices or private marital dynamics. Instead, providers should validate abortion as an essential component of routine reproductive healthcare. Second, hospital administrators must enforce acoustic privacy during clinical examinations and post-procedure recovery. Patients require quiet, confidential spaces to discuss their medical histories without fear of eavesdropping. Furthermore, healthcare teams should implement brief pre-discharge counseling sessions before patient discharge. These structured interactions provide reassurance, correct prevalent myths, and offer clear recovery guidance. In addition, nursing staff and support personnel must use respectful, non-stigmatizing medical terminology. Third, hospitals should establish referral pathways connecting gynecology units with qualified mental health professionals. Consequently, women experiencing severe guilt can access professional counseling without facing additional judgment. Moreover, peer support resources and educational pamphlets empower patients to process complex emotions safely. Ultimately, medical teams cultivate healing environments by replacing societal judgment with clinical empathy. Therefore, dedicated stigma reduction protocols improve clinical adherence, psychological resilience, and patient well-being.
Internalized abortion stigma significantly impairs emotional and physical health outcomes by generating intense guilt, acute anxiety, and persistent social isolation. Consequently, affected individuals frequently conceal their reproductive medical history, avoid timely clinical follow-ups, and delay seeking emergency intervention for complications. Furthermore, this chronic distress escalates long-term risks for clinical depression. Ultimately, unaddressed stigma reduces quality of life and erodes patient trust in public healthcare systems.
The Individual Level Abortion Stigma Scale measures internalized guilt, perceived social judgment, and secrecy needs effectively. Although originally designed for research, its core domains help clinicians identify vulnerable patient profiles during consultations. Therefore, understanding these specific metrics allows medical teams to tailor supportive counseling. In addition, practitioners can anticipate psychological distress and structure post-procedure mental health interventions successfully. Consequently, systematic assessment bridges the gap between surgical success and long-term emotional recovery.
Indian healthcare providers can reduce abortion stigma by maintaining privacy and eliminating moralistic language during consultations. Furthermore, doctors must reassure patients regarding strict statutory confidentiality under the amended MTP Act. Clinicians should validate pregnancy termination as standard, essential healthcare rather than a moral failure. In addition, providing compassionate, nonjudgmental counseling and structured psychosocial referrals empowers women significantly. Consequently, patients navigate post-abortion recovery with enhanced dignity and emotional confidence.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A cross-sectional study demonstrates that internalized abortion stigma affects women seeking legal pregnancy termination independently of demographic factors. Clinicians must address pervasive judgment concerns, enforce strict confidentiality, and deliver empathetic care to improve psychological recovery.
Today

A randomized controlled trial demonstrates that a 12-week Tai Chi program significantly reduces post-transplant fatigue, enhances sleep quality, and increases 6-minute walk distance in renal transplant recipients, providing a safe and effective non-pharmacological rehabilitative exercise therapy.
Today

A study shows that the aggregate index of systemic inflammation (AISI) significantly associates with elevated myocardial injury markers, including cardiac troponin T and CK-MB, in patients with coronary heart disease, highlighting its potential utility for cardiovascular risk stratification.
Today
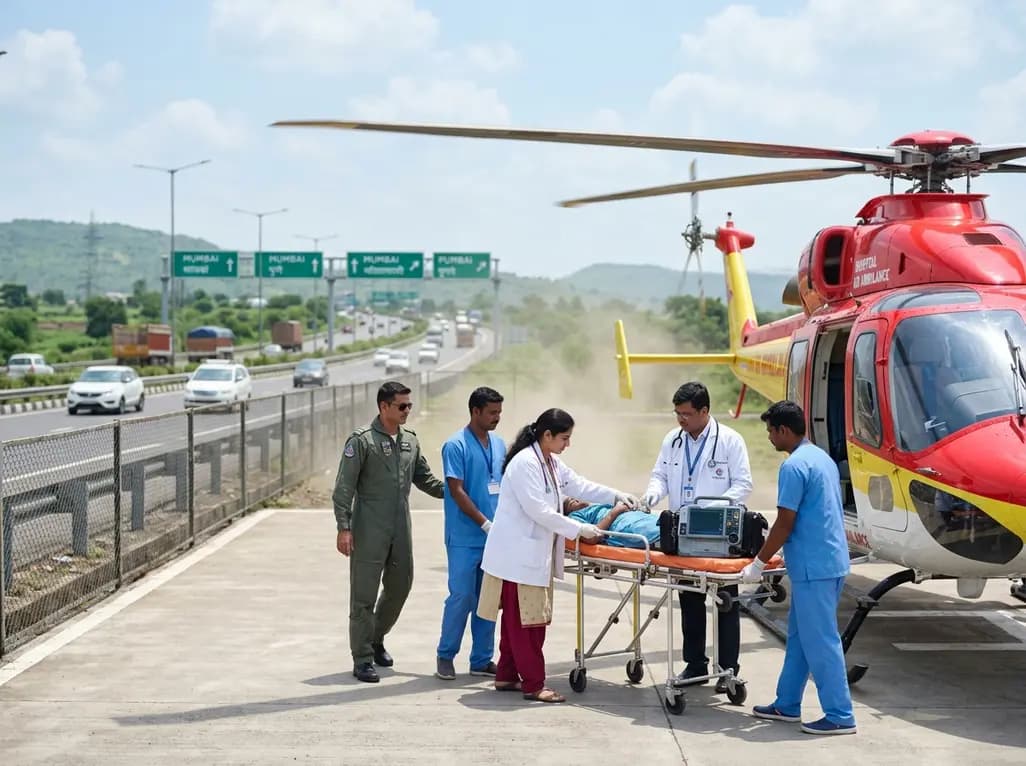
The state government is deploying helicopter emergency medical services across the Mumbai-Pune Expressway, Samruddhi Mahamarg, and Mumbai-Goa Highway. This initiative establishes unified standard operating procedures to enable rapid triage, advanced prehospital resuscitation, and seamless trauma care transfers.
Today

Calcimimetic therapy for primary hyperparathyroidism can induce profound tumor fibrosis, necrosis, and reduced vascularity. These changes alter ultrasound and 4D-CT imaging and cause dense recurrent laryngeal nerve adhesions, requiring heightened surgical vigilance during definitive parathyroidectomy.
Today
