

Loading, please wait...
Loading, please wait...

Sleep disturbances represent one of the most prevalent yet undertreated comorbidities among neurodivergent youth. Clinical research indicates that up to 80 percent of youth on the autism spectrum experience significant sleep disruption. Specifically, managing insomnia in autistic adolescents presents unique behavioral and neurological challenges for families and clinicians alike. For example, pediatricians and child psychiatrists frequently encounter persistent sleep onset delay, fragmented rest, and early morning awakenings in this patient population. A qualitative study led by Cleary and colleagues explores how autistic youth and their caregivers experience and manage these sleep challenges. Consequently, understanding these firsthand accounts helps clinicians design supportive, individualized sleep interventions.
Sleep architecture in neurodivergent populations often exhibits pronounced physiological differences. In particular, researchers have identified endogenous melatonin dysregulation, altered circadian rhythmicity, and heightened autonomic arousal as core contributors to chronic sleeplessness. Consequently, autistic adolescents frequently encounter persistent difficulties initiating and sustaining restorative sleep throughout the night.
Furthermore, untreated insomnia compounds core neurodevelopmental symptoms, exacerbating sensory sensitivities, emotional dysregulation, and daytime executive dysfunction. For instance, adolescents frequently struggle with school attendance and academic engagement when sleep debt accumulates. Therefore, sleep cannot remain an afterthought in pediatric care; it demands targeted clinical assessment.
In addition to physiological drivers, co-occurring psychological conditions frequently worsen bedtime resistance. Similarly, generalized anxiety, social stressors, and attention-deficit comorbidities significantly disrupt evening wind-down periods. Clinicians must recognize that chronic sleep disruption deeply affects whole families, causing persistent caregiver stress and household strain. As a result, addressing these layered issues early during adolescence protects long-term cognitive and psychiatric well-being. Hence, clinicians must proactively screen for insomnia during routine developmental evaluations. Moreover, inadequate sleep intensifies tactile and auditory hypersensitivities during the daytime. Ultimately, this vicious cycle between sensory reactivity and sleep loss underscores the urgent need for structured clinical frameworks.
A particularly intriguing outcome from the study by Cleary and colleagues involves the stark contrast between adolescent perceptions and objective functional reality. Specifically, many autistic adolescents reported that they slept well, even while describing classical insomnia symptoms. For example, participants reported prolonged sleep onset latency and nighttime awakenings without recognizing these patterns as sleep pathology.
In fact, this perceptual discrepancy often arises from altered interoception and atypical self-monitoring among autistic individuals. Consequently, adolescents may view several hours of tossing and turning as entirely typical. However, objective daytime consequences remain evident to parents, educators, and clinicians. For instance, severe morning lethargy, irritability, and attentional lability frequently betray underlying chronic sleep deprivation.
Therefore, healthcare providers cannot rely solely on self-reported sleep quality when evaluating neurodivergent teenagers. Instead, clinicians must actively triangulate information by taking comprehensive histories from caregivers. Additionally, introducing validated sleep logs and wearable actigraphy helps bridge the gap between youth perception and clinical reality. Furthermore, by reviewing concrete sleep data alongside adolescents, practitioners foster self-advocacy without invalidating their personal lived experiences. Ultimately, this collaborative approach enhances therapeutic rapport and encourages meaningful engagement in behavioral adjustments.
Families rarely wait for formal sleep clinic appointments before attempting practical solutions at home. Instead, parents and youth collaboratively deploy numerous intentional behavioral modifications to encourage rest. In the qualitative study, participants consistently favored multimodal routine activities designed to diminish sensory overload before bedtime.
Specifically, adolescents relied heavily on auditory supports to mask distressing household and ambient sounds. For example, many participants used white noise machines, calming music, or familiar recorded stories to facilitate evening relaxation. Similarly, parents emphasized the critical value of rigorous stimulus reduction. Consequently, they deliberately dimmed household lights, instituted tech-free quiet periods, and adapted bedroom temperature to sensory preferences.
Furthermore, maintaining predictable, structured bedtime routines provided indispensable emotional grounding. In addition, behavioral predictability significantly alleviates nocturnal anxiety, signaling neurochemical readiness for sleep. However, families often develop these interventions through protracted trial and error rather than professional medical guidance. While some sensory adaptations prove beneficial, others—such as unsupervised bedtime screen use—can inadvertently suppress natural melatonin production. Therefore, clinicians must guide families in optimizing these home routines, refining constructive sensory habits while phasing out counterproductive sleep practices.
The qualitative research reveals an important systemic vulnerability regarding health communication. Specifically, adolescents obtained almost all their knowledge about sleep hygiene directly from parents rather than medical professionals. Conversely, parents actively searched external sources, navigating disparate online forums, support communities, and popular literature to find actionable answers.
In fact, this finding highlights a troubling communication gap within mainstream healthcare systems. Despite the profound prevalence of chronic insomnia among autistic adolescents, families encounter minimal proactive counseling during routine medical visits. Consequently, parents shoulder an immense navigational burden, often feeling isolated and overwhelmed by conflicting non-evidence-based claims online.
Furthermore, available specialized pediatric sleep services remain exceedingly scarce in many regions, creating extensive waitlists. Similarly, primary care physicians and pediatricians frequently lack training in neurodiversity-affirming sleep medicine, leaving them uncertain about behavioral modification techniques. Therefore, bridging this gap requires structured clinical initiatives. For example, healthcare systems must integrate accessible educational toolkits into routine adolescent assessments. When clinicians actively demystify sleep hygiene, they validate parental dedication and provide adolescents with scientifically grounded health literacy. As a result, families achieve better clinical outcomes and reduced long-term caregiver burnout.
To improve outcomes for autistic adolescents with insomnia, clinicians must translate these qualitative insights into structured, actionable management protocols. First-line clinical guidelines consistently recommend behavioral sleep interventions before initiating pharmacotherapy. However, standard cognitive behavioral therapy protocols for insomnia require deliberate adaptation for autistic youth.
Specifically, clinicians should integrate visual schedules, concrete social stories, and individualized sensory accommodations into sleep hygiene counseling. In addition, clinicians must tailor environmental adjustments to each patient's unique sensory profile, whether addressing tactile sensitivities to bedding or nocturnal auditory hypersensitivity. Furthermore, practitioners should directly involve adolescents in goal setting. For instance, when clinicians invite youth to identify their preferred calming routines, compliance and treatment ownership increase substantially.
Moreover, clinicians must evaluate underlying medical and psychiatric drivers, including gastroesophageal reflux, nocturnal seizures, restless legs syndrome, and generalized anxiety. If behavioral modifications prove insufficient, low-dose melatonin represents an evidence-supported pharmacological option under physician supervision. Ultimately, clinicians must adopt a collaborative, family-centered partnership model. Therefore, by combining empathetic listening with evidence-based strategies, medical professionals can significantly enhance sleep quality and overall daily well-being for neurodivergent youth.
Insomnia in autistic adolescents commonly presents as prolonged sleep onset latency, frequent nocturnal awakenings, irregular circadian rhythms, and shortened total sleep duration. Adolescents may exhibit significant bedtime anxiety, bedtime resistance, and daytime sensory sensitivities or irritability. However, some youth might not subjectively report distress despite severe daytime functional impairment.
First-line interventions focus on behavioral and environmental modifications tailored to sensory profiles. Clinicians recommend predictable bedtime routines, visual schedules, dimming evening lighting, and mitigating disruptive noises using white noise. Minimizing late-evening screen exposure, maintaining consistent waking times, and utilizing comfortable, non-irritating bedding further support restful and restorative sleep onset.
Clinicians consider pharmacotherapy when structured behavioral adjustments and sensory modifications fail to resolve persistent sleep disruption. Exogenous melatonin represents the best-studied first-line agent for shortening sleep onset latency. Physicians must initiate low doses, monitor for adverse effects, and thoroughly address underlying medical conditions, such as gastrointestinal distress or anxiety.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Up to 80% of autistic adolescents experience sleep disturbances. A qualitative study by Cleary et al. reveals key disconnects between youth self-perception and clinical insomnia, underscoring the value of tailored sensory routines, parental guidance, and heightened professional awareness in neurodevelopmental care.
Today
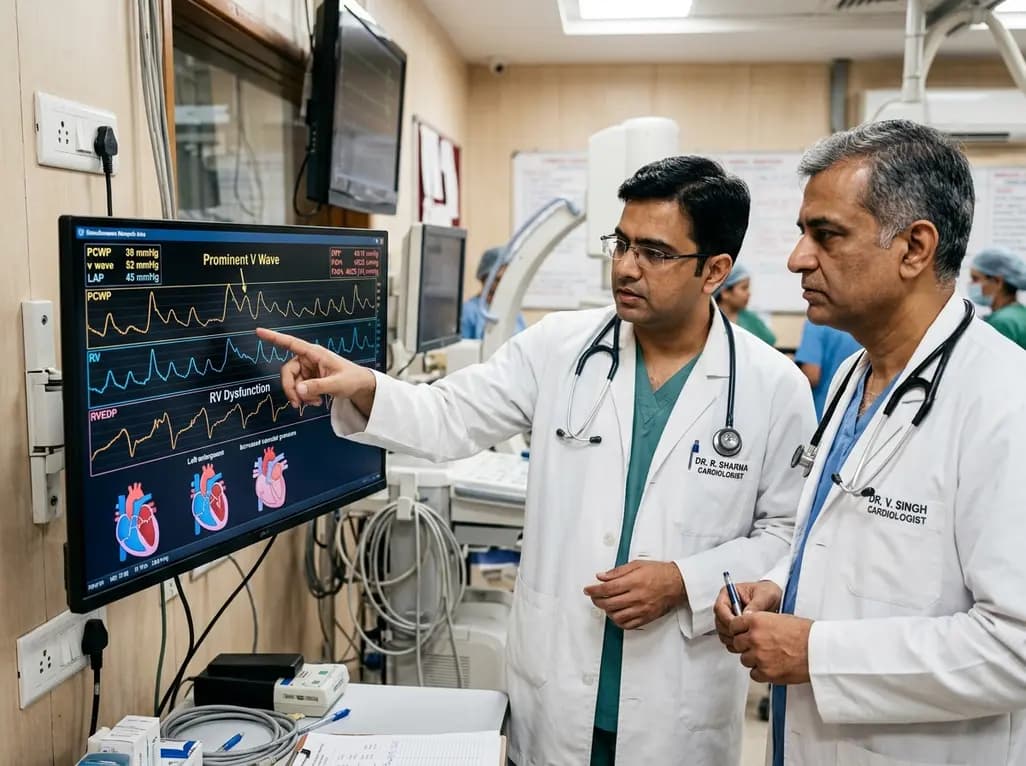
Left atrial stiffening generates prominent V waves that pressurize the pulmonary circulation and augment right ventricular afterload independently of intrinsic pulmonary vascular disease in patients with heart failure with preserved ejection fraction.
Today

A meta-analysis demonstrates that secondhand smoke exposure significantly elevates fetal loss risk by 21% among nonsmoking pregnant women. Clinicians must implement household screening and family-centered cessation interventions to prevent avoidable miscarriages and stillbirths.
Today

Preclinical validation demonstrates that a novel contact force-integrated pulsed field quantization index accurately predicts lesion depth in real time, achieving 100% durable pulmonary vein isolation without collateral injury.
Today
A new cross-sectional evaluation reveals how regional lean mass and bone mineral content interact in resistance-trained men, showing that whole-body size and allometric scaling explain shared musculoskeletal phenotypes and strength relationships.
Today

Explore the emerging role of glucose metabolic reprogramming in exercise-attenuated osteoporosis, examining how physical activity influences osteoblast glycolysis, osteoclast bioenergetics, and skeletal remodeling pathways to improve bone mineral density.
Today
