

Loading, please wait...
Loading, please wait...

Forensic clinicians increasingly encounter individuals deemed incompetent to stand trial due to debilitating psychiatric illnesses. In modern legal systems, defendants must possess sufficient mental capacity to understand proceedings and assist counsel rationally. However, severe mental disorders frequently impair these cognitive and communicative faculties. When untreated psychosis impairs rational decision-making, the court stays criminal proceedings for psychiatric evaluation and restoration. Consequently, forensic hospitals experience unprecedented occupancy pressures as referrals surge. A landmark multi-hospital investigation by McDermott and colleagues examined individuals committed across state hospitals following competency evaluations. Specifically, researchers combined state psychiatric records with Medicaid data covering community mental health services prior to arrest. Their findings revealed that nearly half of these defendants experienced unsheltered homelessness during their apprehension. Furthermore, half of the individuals had received no community mental health care during the preceding six months. Therefore, being adjudicated incompetent to stand trial frequently reflects a catastrophic breakdown in public health support rather than a purely forensic dilemma. Addressing this crisis requires clinicians to examine underlying social determinants of health systematically.
The relationship between housing instability and severe mental disorder represents a deeply entrenched bidirectional cycle. Specifically, acute psychosis severely disrupts an individual's occupational functioning and executive decision-making. Consequently, vulnerable individuals frequently lose family connections, financial security, and stable shelter. On the other hand, living unsheltered directly exacerbates psychiatric decompensation. Sleep deprivation, street violence, nutritional compromise, and social isolation worsen affective and cognitive symptoms. In addition, substance use disorders often emerge as maladaptive coping mechanisms on the street, compounding cognitive disorganization. Clinical evaluations consistently reveal that homeless defendants exhibit significantly higher rates of formal thought disorder and paranoia. Because acute street survival demands immediate vigilance, chronic psychiatric symptoms remain entirely unmanaged. Hence, these vulnerable patients frequently encounter law enforcement for minor public disturbance offenses. When the justice system arrests these individuals, reality distortion immediately impedes legal proceedings. Thus, homelessness functions both as a potent catalyst for psychiatric deterioration and as a consequence of unmanaged illness.
A striking revelation from epidemiological forensic investigations centers on the complete absence of outpatient care before arrest. Despite possessing social welfare coverage, nearly half of incompetent defendants receive zero community mental health treatment for months prior to criminal charges. Instead, when these individuals access healthcare, it occurs almost exclusively through acute emergency departments. Hospital emergency rooms provide brief stabilization, yet they lack robust discharge mechanisms to sustain longitudinal recovery. Moreover, data indicate pronounced gender disparities within forensic populations. Homeless men with severe psychiatric disorders face disproportionately high hurdles in accessing outpatient clinics and subsidized supportive housing. Societal stigma, fragmented social service programs, and rigid clinical criteria often alienate unhoused men until legal conflict occurs. Furthermore, public clinics frequently require fixed residential addresses, effectively disenfranchising unsheltered individuals. Consequently, treatable mental illnesses progress unabated into profound functional disability. As psychiatric symptoms escalate without clinical containment, decompensated men experience heightened vulnerability to arrest. Therefore, carceral settings increasingly function as default psychiatric institutions for underserved men.
Once courts declare a defendant incompetent to stand trial, the primary statutory objective shifts strictly toward competency restoration. Clinicians administer evidence-based pharmacotherapy and psychoeducation to help the patient comprehend courtroom proceedings. However, this legal mandate frequently creates profound ethical and systemic tensions for practicing psychiatrists. State forensic hospitals face severe shortages of psychiatric beds, forcing decompensated individuals to languish in local jails for months awaiting admission. In carceral environments, sensory deprivation, punitive isolation, and lack of specialized nursing care drastically worsen psychotic symptoms. Furthermore, hospital clinicians often note that competency restoration primarily prepares individuals for trial rather than comprehensive community reintegration. Once restored and sentenced, defendants frequently return to the identical unsheltered environments that precipitated their initial clinical decline. This revolving door between streets, jail cells, and forensic hospital wards squanders public resources and harms vulnerable patients. In addition, treating severe schizophrenia solely through episodic crisis interventions prevents durable biological and psychological recovery. Without coordinated post-restoration diversion pathways, patients remain trapped in continuous forensic cycles. Thus, psychiatric systems must reevaluate how forensic interventions interface with rehabilitative medicine.
Resolving the crisis of incompetent defendants requires fundamentally restructuring community mental health delivery and diversion mechanisms. Legislative reforms, such as California's Community Assistance, Recovery, and Empowerment Act, seek to intervene earlier before criminal conduct occurs. Similarly, international mental health frameworks, including India's Mental Healthcare Act 2017, mandate community-based rehabilitation for homeless mentally ill individuals. For practicing clinicians, early assertive community treatment teams provide a powerful clinical vehicle to reach homeless individuals before legal decompensation happens. These multidisciplinary teams deliver long-acting injectable antipsychotics, supportive psychotherapy, and immediate supportive housing directly on the streets. Moreover, pre-booking diversion programs enable law enforcement officers to transfer individuals experiencing acute psychosis directly to crisis stabilization centers rather than detention cells. When criminal courts divert non-violent offenders into outpatient restoration and clinical treatment, hospital burden decreases dramatically. In addition, establishing specialized mental health courts ensures continuous judicial oversight paired with individualized medical treatment plans. Ultimately, providing stable supportive housing alongside continuous psychiatric treatment breaks the recurrent cycle of homelessness and incarceration. Healthcare providers must actively advocate for these integrated models to restore human dignity.
Clinicians evaluate whether an active mental illness impairs a defendant's factual and rational understanding of court proceedings. Specifically, the forensic examiner assesses if the individual can comprehend legal charges, appreciate possible courtroom penalties, and communicate effectively with defense counsel. When severe delusions, thought disorganization, or cognitive deficits destroy these functional capabilities, the court declares the person incompetent to stand trial. Consequently, judges mandate therapeutic competency restoration before proceeding with legal adjudication.
Homeless men experience compounded vulnerabilities stemming from severe chronic psychopathology, profound social isolation, and severe barriers to social welfare services. Furthermore, public outpatient clinics often lack flexible outreach frameworks capable of engaging unsheltered individuals experiencing paranoid delusions. Consequently, unmedicated psychotic illnesses progress untreated until bizarre or disruptive behaviors trigger law enforcement intervention. Because men also encounter higher rates of street-level arrests, their untreated illnesses rapidly funnel them into the forensic competency system.
Outpatient competency restoration enables non-violent defendants to receive structured psychiatric treatment in community settings instead of carceral facilities or locked forensic wards. By integrating continuous medication management, supportive housing, and legal psychoeducation, these specialized community programs avert debilitating incarceration trauma. Furthermore, patients maintain vital family networks, access comprehensive social rehabilitation, and learn durable illness management skills. Ultimately, this therapeutic approach relieves forensic bed shortages while significantly curbing recidivism among vulnerable psychiatric patients.
Disclaimer: This content is for informational and educational purposes only. It is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A multicenter forensic study highlights how homelessness and a lack of prior outpatient psychiatric care correlate with being adjudicated incompetent to stand trial, underscoring the urgent need for integrated community mental health systems and diversion programs.
Today

The ASAS core set defines mandatory domains and instruments for axial spondyloarthritis across routine and extended clinic visits, optimizing outpatient care and aligning treatment monitoring with international guidelines.
Today

A Belgian study highlights maternal desires and healthcare provider perspectives on breastfeeding in women living with HIV. While viral suppression reduces transmission risk below 1%, significant clinical training and policy gaps remain, highlighting the urgent need for multidisciplinary counseling protocols.
Today
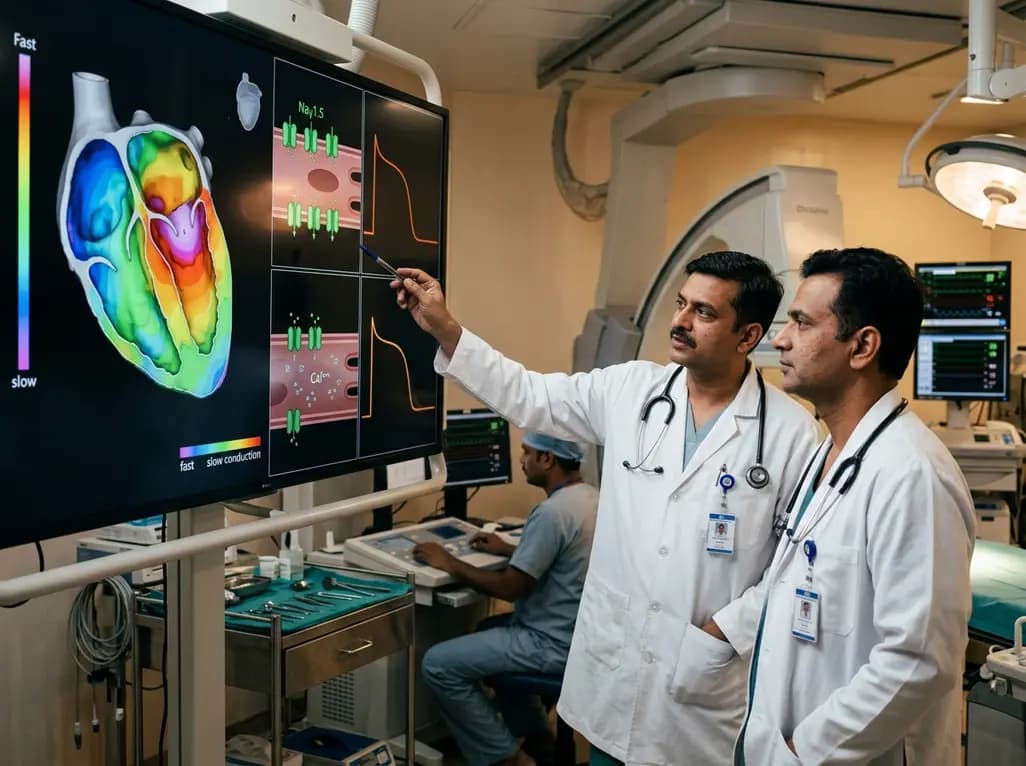
New research reveals that non-ablative radiotherapy suppresses ventricular tachycardia by increasing conduction velocity via NaV1.5 upregulation and action potential prolongation. However, sustained sodium current elevation and depressed calcium handling highlight the need for careful clinical translation.
Today

Diagnostic data shows that nearly one in four spine investigations now involve patients younger than 40 years. This comprehensive overview explores the drivers behind this demographic trend, evaluates ergonomic hazards, clarifies red-flag signs, and highlights clinical indications for judicious diagnostic imaging.
Yesterday

A landmark randomized clinical trial demonstrates that real-time continuous glucose monitoring significantly reduces HbA1c and enhances time in range for individuals with type 2 diabetes who do not take insulin, paving the way for broader clinical adoption and personalized metabolic therapy in primary care.
Today
