

Loading, please wait...
Loading, please wait...

Managing sleep architecture and psychotropic pharmacology during the perioperative period presents significant challenges for surgical teams. Historically, acute postoperative behavioral disturbances received quick referrals to mental health specialists. However, contemporary evidence demonstrates that hypnotic discontinuation after surgery represents an intricate physiological signal rather than a definitive psychiatric illness. When patients suddenly cease taking long-term sedative-hypnotic medications following an operation, neurochemical balance undergoes profound disruption. Therefore, treating clinicians must view these presentations through a comprehensive neurobiological lens. Careful evaluation ensures timely interventions and protects surgical recovery.
Hypnotic discontinuation after surgery frequently occurs unintentionally across diverse hospital environments. Patients admitted for planned or emergency procedures often experience unexpected interruptions in their chronic medication regimens. Consequently, surgical teams may fail to reconcile outpatient prescriptions accurately during perioperative transitions. In addition, routine postoperative fasting, gastrointestinal paralysis, and strict nil-per-os protocols prevent oral pill administration. Because sedative-hypnotic medications alter gamma-aminobutyric acid neurotransmission, their sudden cessation precipitates a cascade of autonomic and central nervous system abnormalities. Surgical teams frequently encounter patients exhibiting profound sleeplessness, psychomotor restlessness, and heightened anxiety within forty-eight hours of surgery. Unfortunately, clinicians might interpret these acute manifestations as de novo psychiatric emergencies or personality decompensations. Recognizing this trajectory as a predictable pharmacology-driven phenomenon rather than an intrinsic psychiatric crisis remains paramount. Furthermore, early identification allows clinicians to distinguish between physiological withdrawal and other serious postsurgical complications, including sepsis, pulmonary embolism, and cerebral hypoperfusion.
Chronic consumption of benzodiazepines and non-benzodiazepine receptor agonists induces profound down-regulation of inhibitory neural circuits. Over time, central nervous system pathways adapt by diminishing GABA-A receptor sensitivity and simultaneously up-regulating excitatory glutamatergic signaling. Therefore, abrupt drug removal unmasks a dominant state of unmitigated neuroexcitation. Surgical stress significantly amplifies this imbalance through systemic neuroendocrine stimulation. The surgical stress response triggers high releases of cortisol, catecholamines, and inflammatory cytokines like interleukin-six. Consequently, these circulating inflammatory mediators cross the blood-brain barrier and further destabilize cerebral homeostasis. Patients subsequently experience severe rebound insomnia, diaphoresis, tachycardia, fine tremors, and sensory hyperacusis. In severe scenarios, untreated neuroexcitation rapidly evolves into overt delirium or grand mal seizures. Surgeons must recognize that these physiological signs reflect profound neurochemical adaptation rather than primary psychiatric decompensation. Thus, immediate pharmacological re-evaluation takes absolute precedence over psychiatric confinement.
Differentiating surgical complications from primary psychiatric disorders requires rigorous clinical discrimination. When acute agitation develops on postoperative wards, primary teams frequently request emergent psychiatric consultations to diagnose psychotic or affective disorders. Nevertheless, assigning a lifelong psychiatric diagnosis during the immediate perioperative phase is clinically inappropriate. The surgical recovery process introduces massive physiological confounders, including unmanaged surgical pain, occult bleeding, fluid shifts, and electrolyte imbalances. In addition, acute urinary retention and hypoxemia mimic severe agitation and panic states. When teams overlook hypnotic discontinuation, they misattribute agitation to underlying psychopathology and administer inappropriate dopamine antagonists. First-generation and atypical antipsychotics can lower seizure thresholds and aggravate autonomic instability in withdrawing patients. Therefore, clinicians must systematically examine preoperative substance histories before attributing altered mental status to psychiatric illness. A comprehensive medication reconciliation accurately identifies hypnotic cessation as the primary driver of patient distress.
Establishing collaborative care between surgeons, anesthesiologists, and consulting psychiatrists ensures optimal outcomes for complex surgical patients. Structured perioperative protocols should actively identify chronic hypnotic users weeks before elective operations occur. For instance, pre-anesthetic evaluation clinics must document exact dosages, treatment durations, and specific agents taken for insomnia. When hospitalization interrupts normal oral intake, teams should implement planned bridging therapies using equivalent intravenous or sublingual agents. Furthermore, clinical pharmacists play an indispensable role by preventing accidental omission of chronic sedative therapies. If discontinuation is clinically necessary, structured tapering protocols minimize withdrawal severity and preserve cognitive clarity. Concurrently, nursing staff should implement environmental modifications to support circadian rhythms. Minimizing nighttime ward noise, avoiding unnecessary vital sign checks during deep sleep, and exposing patients to morning sunlight substantially improve sleep stability. Thus, integrated multimodal protocols minimize reliance on emergency psychotropic interventions.
In the Indian healthcare context, addressing hypnotic cessation holds unique clinical relevance. Over-the-counter dispensing practices and fragmented electronic medical records often obscure chronic benzodiazepine and Z-drug consumption among surgical candidates. Furthermore, patients rarely disclose sleep aids to surgical teams due to social stigma or misconceptions regarding sleep medication relevance. Consequently, Indian surgeons frequently encounter unheralded withdrawal delirium in elderly postoperative cohorts. Given high surgical volumes and crowded inpatient wards, untreated agitation dramatically increases nursing burdens and accidental tube removals. Therefore, Indian healthcare institutions must implement standardized preoperative screening tools at admission. Training junior residents and nursing personnel to recognize early withdrawal signs prevents catastrophic outcomes. By acknowledging that acute insomnia signals pharmacologic disruption rather than psychiatric failure, hospitals optimize clinical resource allocation. Ultimately, systematic medication tracking improves patient safety and aligns surgical practice with international quality standards.
Deploying validated assessment tools allows healthcare teams to differentiate withdrawal states from emerging delirium promptly. Clinicians can utilize standardized instruments such as the Confusion Assessment Method and the Clinical Institute Withdrawal Assessment scale. Moreover, structured deprescribing must never occur haphazardly during acute surgical stress. If chronic hypnotic cessation represents an overarching clinical goal, providers should defer the deprescribing timeline until physical recovery stabilizes. Initiating deliberate dose reductions during acute wound healing precipitates severe sleep fragmentation and elevates catabolic hormones. Consequently, chronic sleep deprivation impairs immune surveillance and delays tissue regeneration. Instead, clinicians should stabilize sleep pharmacologically during hospitalization and arrange post-discharge tapering schedules in outpatient settings. Transitioning patients to cognitive behavioral therapy for insomnia provides lasting non-pharmacological recovery once surgical recovery completes.
Abrupt cessation of chronic hypnotic agents causes sudden loss of inhibitory GABAergic tone and unchecked glutamatergic excitation. When combined with surgery-induced neuroinflammation and elevated catecholamines, this pharmacological imbalance produces severe anxiety, tachycardia, restlessness, and cognitive confusion. Clinicians must recognize this neurochemical storm as acute pharmacological withdrawal rather than an emerging psychiatric illness.
Teams should immediately perform comprehensive medication reconciliation and reintroduce the baseline hypnotic agent or a long-acting equivalent. If the patient cannot swallow, clinicians should administer intravenous or transdermal substitutes under hemodynamic monitoring. Supportive care involves maintaining electrolyte balance, optimizing analgesia, ensuring adequate hydration, and consulting clinical pharmacists to design a safe, gradual postoperative tapering schedule.
Withdrawing hypnotics during acute surgical convalescence induces severe insomnia and elevates systemic stress hormones like cortisol and adrenaline. Consequently, disrupted sleep architecture impairs immune function, worsens pain perception, and delays surgical wound healing. Deprescribing achieves significantly higher success rates when conducted gradually in stable outpatient environments with non-pharmacological behavioral therapy support.
Disclaimer: This content is for informational and educational purposes only and does not substitute professional medical advice. Refer to the latest local and national guidelines for clinical practice.
References
Tambasco D et al. When hypnotic discontinuation follows surgery: A clinical signal, not a psychiatric verdict. Psychiatry Clin Neurosci. 2026 Oct 18. doi: 10.1111/pcn.70153. PMID: 42893958.
Gleason LJ et al. Perioperative medication reconciliation and the management of chronic sedative-hypnotic agents. Anesthesiology. 2023;138(4):450-461.
Devlin JW et al. Clinical practice guidelines for the prevention and management of pain, agitation/sedation, delirium, immobility, and sleep disruption in adult patients in the ICU. Crit Care Med. 2018;46(9):e825-e873.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Hypnotic discontinuation after surgery often reflects complex perioperative physiology and medication cessation rather than a primary psychiatric breakdown. Clinicians must recognize these acute neurobehavioral signals to prevent misdiagnosis, optimize medication reconciliation, and improve patient recovery.
Today
Kenya's confirmation of its eighth Ebola infection highlights the acute risk of secondary transmission in hospital environments. Clinicians must maintain high vigilance, enforce strict infection prevention protocols, and implement rapid triage mechanisms for viral hemorrhagic fevers across healthcare settings.
Today
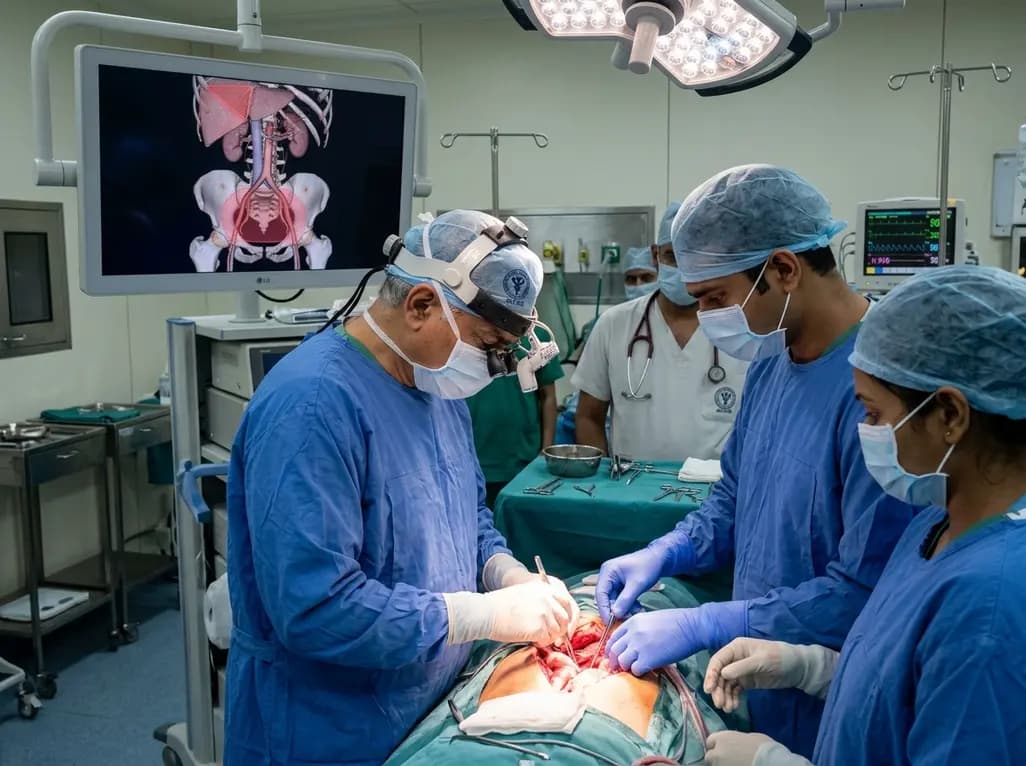
Surgical oncologists at AIIMS Delhi have mapped two critical anatomical landmarks: Ray's Zone in the deep pelvis and Ray's Hepatocaval Triangle near the liver. These predefined hazard boundaries guide dissection, dramatically reduce severe intraoperative bleeding, and preserve vital nerves and visceral organs.
Today

A study reveals that the MYLK c.4079G>A, p.(Gly1360Asp) variant is linked to high-penetrance heritable thoracic aortic disease and early-onset aortic dissection, showing a founder effect in Finnish cohorts. Findings emphasize early cascade screening and vigilant surveillance.
Yesterday

A novel sacrificial-template technique combines FDM polymer 3D printing and micro-arc oxidation to fabricate orientation-controlled porous titanium scaffolds. These bioactive constructs offer tailored stiffness, exceptional multidirectional load resistance, and robust osseointegration for bone defect repair.
Today
A novel label-free electrochemical biosensor utilizing magnetic nanocomposites enables ultrasensitive TERT C228T mutation detection (LOD: 0.67 pM) for rapid risk stratification in papillary thyroid cancer, offering promising point-of-care utility for endocrine oncology.
Today
