

Loading, please wait...
Loading, please wait...

Atopic dermatitis is a chronic inflammatory skin condition that frequently presents with severe localized manifestations on visible body sites. Consequently, assessing facial and cervical involvement requires precise, standardized clinical scoring instruments. The head and neck EASI sub-score has emerged as an indispensable metric in modern randomized controlled trials and clinical registries. However, clinicians previously lacked validated qualitative strata to interpret these numerical values in daily practice. A landmark multi-observer validation study has successfully established robust severity strata for this instrument, aligning them directly with the validated Investigator Global Assessment for Atopic Dermatitis.
Facial and cervical eczema imposes an overwhelming psychosocial and physical burden on affected individuals. Visible erythema, scaling, and excoriation significantly impair emotional well-being and social interactions. Furthermore, the head and neck region exhibits distinct anatomical characteristics, including thinner skin, heightened follicular density, and greater susceptibility to cutaneous irritants. Although full-body EASI quantifies overall cutaneous involvement, it often dilutes the pronounced impact of localized head and neck flares. For instance, severe facial eczema might generate only a modest change in the total body score. Therefore, targeted assessment of this specific anatomical zone provides essential clinical insight that global scores obscure.
Moreover, contemporary systemic treatments have underscored the necessity of localized disease tracking. Recent clinical trials evaluating biologic therapies and oral Janus kinase inhibitors frequently highlight head and neck outcomes as critical secondary endpoints. In addition, clinicians occasionally report paradoxical head and neck erythema during dupilumab therapy. Consequently, isolating regional activity through the head and neck EASI metric allows dermatologists to monitor therapeutic responsiveness precisely. Establishing objective, validated bands ensures that clinicians evaluate regional disease severity uniformly across academic research and routine patient care.
To overcome interpretive ambiguity, researchers conducted a rigorous multi-rater validation study. Twenty-two experienced dermatologists independently reviewed high-resolution standardized clinical photographs depicting twenty-one diverse patients with head and neck atopic dermatitis. Specifically, the evaluators assessed each patient case using both the head and neck EASI and the validated Investigator Global Assessment for Atopic Dermatitis. The investigators employed an anchor-based methodology, which represents the gold standard in psychometric outcome validation. This technique maps unfamiliar continuous score distributions directly onto an established, clinically meaningful anchor scale.
Furthermore, the researchers applied advanced statistical modeling to derive the definitive severity thresholds. They analyzed the empirical distribution of continuous head and neck EASI values within each static vIGA-AD tier. In addition, the study team evaluated convergent validity by calculating Kendall rank correlation and Spearman rank correlation coefficients. To determine interrater agreement, investigators calculated intraclass correlation coefficients and weighted Cohen kappa values. This dual assessment ensured that derived numerical cutoffs reflected genuine biological severity rather than subjective investigator variance. Consequently, the study yielded a mathematically sound framework that bridges continuous scoring with intuitive clinical strata.
The statistical analyses yielded precise numerical thresholds that map head and neck EASI scores directly to standard morphological grades. Clinicians can now interpret numerical sub-scores across five distinct clinical categories. A score of exactly zero denotes completely clear skin without visible inflammatory lesions. Subsequently, scores ranging between 0.1 and 0.6 designate almost clear skin, reflecting minimal residual erythema or induration. Patients scoring between 0.7 and 1.7 fall into the mild severity stratum. In contrast, scores extending from 1.8 to 3.0 represent moderate disease activity, where palpable infiltration and visible excoriations become prominent. Finally, scores between 3.1 and the regional maximum of 4.8 denote severe head and neck dermatitis.
These stratification boundaries provide immense utility for clinicians evaluating therapeutic response trajectories. In clinical trial designs, regulators frequently demand binary endpoints, such as achieving clear or almost clear status with a two-grade improvement. However, regional sub-scores previously lacked consensus definitions for treatment success. By establishing that scores under 0.7 correspond to clear or almost clear skin, this study equips researchers with standardized benchmark targets. Therefore, investigators can evaluate facial disease resolution with the same statistical rigor applied to whole-body endpoints.
The statistical findings demonstrated exceptional agreement between the head and neck EASI strata and vIGA-AD classifications. Specifically, the analysis revealed a weighted Cohen kappa of 0.83 with a tight 95% confidence interval spanning from 0.80 to 0.86. In psychometric science, a kappa value exceeding 0.80 indicates almost perfect agreement among independent raters. Furthermore, evaluations of convergent validity using Kendall tau and Spearman correlation coefficients confirmed robust monotonicity between the continuous and ordinal measurement systems. Consequently, clinicians can trust that changes in regional numerical scores mirror observable shifts in disease severity.
In addition, intraclass correlation coefficients confirmed excellent interrater reliability across the twenty-two assessing dermatologists. Interobserver consistency represents a pivotal requirement for clinical instruments because subjective variation can introduce significant measurement error. Photodermatological assessments often suffer from variability in lighting, angle, and rater perception. Nevertheless, this evaluation proved that clinicians achieve remarkable consistency when grading head and neck dermatitis using standardized strata. Thus, these validated cutoffs eliminate ambiguity, ensuring reproducible clinical documentation in multicenter research trials as well as outpatient hospital clinics.
The implementation of validated regional strata holds meaningful implications for dermatologists practicing across India. In Indian clinical settings, atopic dermatitis exhibits distinct challenges, such as diagnostic delays, humid tropical weather flares, and prevalent post-inflammatory hyperpigmentation. Because melanin conceals subtle erythema in darker skin phototypes, Indian practitioners frequently find visual erythema grading complex. Consequently, clinicians must integrate edema, excoriation, and lichenification meticulously when calculating regional scores. Anchoring regional severity to clear categories enables Indian practitioners to categorize facial involvement accurately despite underlying pigmentary variation.
Furthermore, facial eczema management requires heightened therapeutic vigilance to prevent steroid-induced cutaneous atrophy, telangiectasia, and perioral dermatitis. Patients in India frequently present after prolonged, unmonitored application of over-the-counter topical corticosteroids. Therefore, having objective strata helps physicians identify when regional disease is moderate or severe, justifying transitions to topical calcineurin inhibitors, crisaborole, or systemic therapies. Moreover, as advanced biologics and oral JAK inhibitors become increasingly accessible in Indian dermatology clinics, utilizing objective regional strata provides defensible documentation for initiating advanced targeted interventions. Ultimately, standardizing regional scoring elevates diagnostic precision and improves long-term patient outcomes.
The head and neck EASI specifically isolates cutaneous signs affecting the facial and cervical regions. While the total EASI integrates four anatomical regions to compute an aggregate score between 0 and 72, the head and neck component evaluates regional erythema, edema, excoriation, and lichenification. Furthermore, multiplying the regional sum by area coverage and a regional weighting factor yields a localized score up to 4.8, allowing clinicians to objectively track sensitive facial dermatitis.
The vIGA-AD provides a standardized, five-point morphological benchmark familiar to regulators and clinicians globally. However, standalone numerical scores from sub-indices lack clear qualitative descriptors. By anchoring head and neck severity directly to vIGA-AD categories, clinicians can readily translate regional numbers into actionable qualitative descriptions. Consequently, practitioners can determine whether localized facial eczema represents mild, moderate, or severe inflammation, standardizing both clinical study endpoints and real-world therapy escalations.
Indian dermatologists frequently encounter persistent facial and cervical eczema triggered by climatic humidity, environmental allergens, and chronic steroid use. In addition, post-inflammatory pigmentary alterations often complicate visual disease evaluation in darker skin phototypes. Therefore, adopting validated score intervals establishes a standardized diagnostic metric. This objective stratification ensures accurate documentation of disease activity, guides judicious non-steroidal topical prescriptions, and supports timely transitions to targeted biologic treatments or JAK inhibitors.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study by Rønnstad et al. defines head and neck EASI severity strata anchored to vIGA-AD: 0 (Clear), 0.1-0.6 (Almost clear), 0.7-1.7 (Mild), 1.8-3.0 (Moderate), and 3.1-4.8 (Severe). This validation provides clinicians with an objective metric to grade regional eczema and monitor targeted treatment responses.
Today

The ASAS core set defines mandatory domains and instruments for axial spondyloarthritis across routine and extended clinic visits, optimizing outpatient care and aligning treatment monitoring with international guidelines.
Today

A Belgian study highlights maternal desires and healthcare provider perspectives on breastfeeding in women living with HIV. While viral suppression reduces transmission risk below 1%, significant clinical training and policy gaps remain, highlighting the urgent need for multidisciplinary counseling protocols.
Today
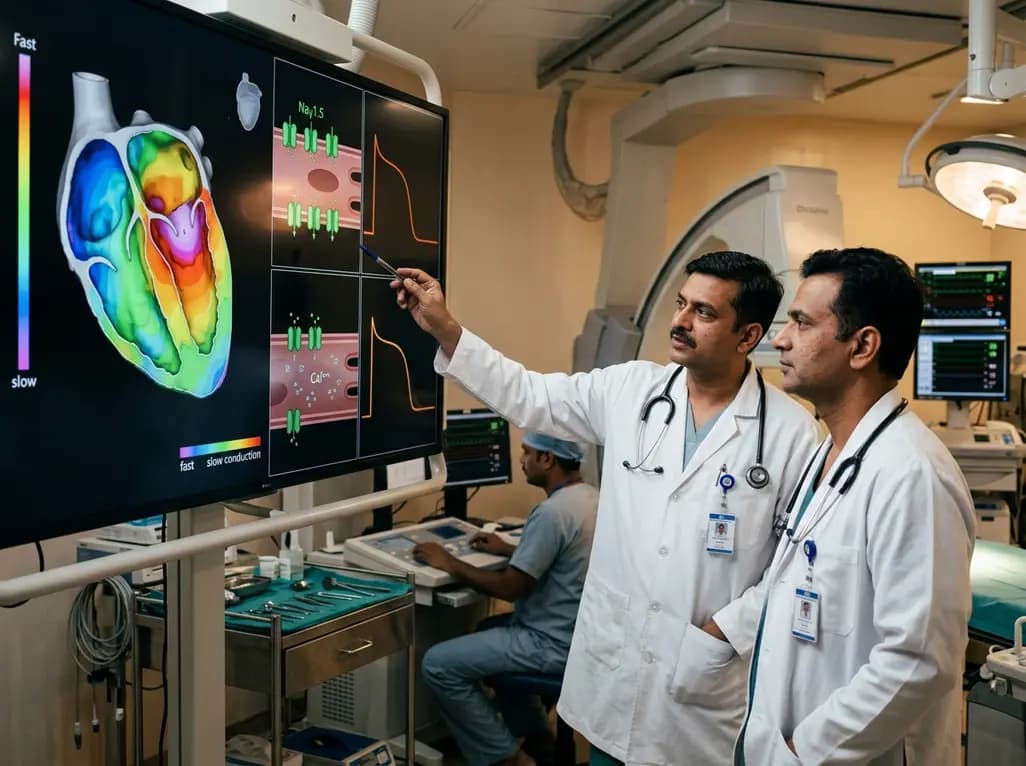
New research reveals that non-ablative radiotherapy suppresses ventricular tachycardia by increasing conduction velocity via NaV1.5 upregulation and action potential prolongation. However, sustained sodium current elevation and depressed calcium handling highlight the need for careful clinical translation.
Today

Diagnostic data shows that nearly one in four spine investigations now involve patients younger than 40 years. This comprehensive overview explores the drivers behind this demographic trend, evaluates ergonomic hazards, clarifies red-flag signs, and highlights clinical indications for judicious diagnostic imaging.
Yesterday

A landmark randomized clinical trial demonstrates that real-time continuous glucose monitoring significantly reduces HbA1c and enhances time in range for individuals with type 2 diabetes who do not take insulin, paving the way for broader clinical adoption and personalized metabolic therapy in primary care.
Today
