

Loading, please wait...
Loading, please wait...

Chronic insomnia remains a widespread medical condition that significantly impairs quality of life, metabolic health, and emotional well-being across diverse patient demographics. Although international guidelines consistently endorse cognitive behavioural therapy as the first-line intervention, practical implementation in everyday practice remains exceptionally low. Clinicians frequently encounter severe barriers, including a shortage of trained therapists, prohibitive private consultation costs, and demanding schedules. Consequently, primary care physicians often feel forced to prescribe sedative-hypnotic medications despite substantial risks of dependence, tolerance, and adverse effects. The delivery of group CBT for insomnia offers a transformative, highly accessible alternative that optimizes clinical resources while preserving robust therapeutic outcomes.
Primary healthcare represents the initial point of contact for the vast majority of patients seeking relief from disrupted sleep patterns. Nevertheless, standard clinical consultations rarely accommodate lengthy psychotherapeutic interventions. Therefore, group delivery models provide an indispensable bridge between specialized sleep clinics and community health centers. In this treatment paradigm, clinicians can guide small cohorts of five to fifteen patients through structured behavioural modifications simultaneously. Moreover, the group dynamic creates a therapeutic microclimate where participants realize that their nocturnal struggles and catastrophic sleep cognitions are not unique. This peer validation significantly reduces the nocturnal anxiety, isolation, and acute frustration that perpetually fuel chronic sleeplessness. In addition, collective accountability fosters stronger treatment adherence, encouraging patients to maintain rigid sleep restriction schedules despite initial daytime fatigue. Furthermore, group discussions allow participants to share realistic coping strategies and celebrate incremental improvements together. As a result, low-threshold primary care programs can dramatically expand service capacity without requiring costly individual psychotherapy appointments. Ultimately, this structural scalability makes evidence-based non-pharmacological care feasible in busy outpatient settings where psychological resources remain notoriously constrained.
To evaluate whether this approach works in real-world outpatient settings, researchers executed a pragmatic, multicentre randomized controlled trial across twenty-six Norwegian Healthy Life Centres. Specifically, the study enrolled 308 adult patients presenting with clinically significant sleep disturbances, defined as an Insomnia Severity Index score of twelve or greater. The investigators randomly allocated participants in a two-to-one ratio, assigning 181 individuals to four weekly group sessions and 127 participants to a waiting list control group. Importantly, the intervention utilized a low-threshold structure consisting of four two-hour sessions delivered over four consecutive weeks. Trained community health professionals conducted these interactive group sessions rather than tertiary academic sleep specialists. Furthermore, the pragmatic design mirrored daily clinical conditions by welcoming patients with common medical and psychiatric comorbidities. Although participants knew their group allocation due to the behavioural nature of psychotherapy, the investigators who analyzed and interpreted the clinical outcome data remained strictly blinded throughout the trial. Consequently, the trial design successfully minimized analytical bias while maintaining the ecological validity necessary for translating clinical trial evidence directly into regular primary practice.
The primary outcome evaluated self-reported symptom change at three months following baseline assessment using the validated Insomnia Severity Index questionnaire. Notably, the group intervention produced substantial and statistically robust improvements compared to the control condition. The adjusted mean difference between the treatment and waiting list arms was negative 3.4 points, demonstrating a clear therapeutic advantage for group therapy. In addition, categorical response rates highlighted profound clinical differences that extended well beyond simple statistical significance. Specifically, 33.6 percent of patients receiving group sessions achieved a clinically relevant improvement, defined as an eight-point or greater reduction on the severity index. In stark contrast, only 13.2 percent of participants on the waiting list reached this threshold of recovery. This divergence yielded an impressive odds ratio of 3.4, indicating that patients participating in groups were more than three times as likely to experience profound relief. Furthermore, subsequent evaluations confirmed that these meaningful symptomatic improvements persisted at six months post-intervention. Therefore, brief group therapy delivers durable relief that matches the benchmarks established in far more resource-intensive, individual treatment protocols.
The efficacy observed in this pragmatic trial stems directly from the multi-component architecture of the cognitive behavioural framework. First, stimulus control therapy works diligently to dismantle the maladaptive conditioned arousal that connects the bed with wakeful frustration. Patients learn to leave the bedroom whenever nocturnal wakefulness exceeds twenty minutes, thereby rebuilding a rapid neurobiological association between the bed and consolidated sleep. Second, sleep restriction temporarily curtails total time in bed to match the patient's actual nocturnal sleep duration. Consequently, this controlled restriction elevates homeostatic sleep pressure, substantially reducing sleep onset latency and eliminating prolonged midnight awakenings. Furthermore, cognitive restructuring systematically dismantles catastrophic thought loops regarding daytime dysfunction and unrealistic eight-hour sleep requirements. Patients discover how to reframe nocturnal anxieties into objective, calm appraisals. In addition, relaxation training and sleep hygiene education address peripheral autonomic hyperarousal and environmental disruptions. When clinicians deliver these synergistic tools within a supportive cohort, group members actively normalize setbacks and encourage persistent behavioural adherence. Thus, cognitive and behavioural interventions work harmoniously to restore the brain's innate sleep-wake regulatory mechanisms.
Sedative-hypnotic medications, including benzodiazepines and Z-drugs, continue to dominate routine insomnia management in outpatient clinics despite clear clinical warnings. However, pharmacotherapy provides only short-term symptom suppression without resolving the cognitive distortions or conditioned hyperarousal maintaining chronic insomnia. Moreover, long-term prescription usage carries severe liabilities, such as psychomotor slowing, daytime cognitive blunting, rebound sleeplessness, and chemical dependency. In this pragmatic trial, group participation significantly curtailed both prescription and over-the-counter sleep medication consumption at three months post-intervention. Nevertheless, general practitioners often struggle to provide non-drug options due to severe consultation time limits and inadequate psychological training. Implementing group sessions within community health structures resolves this clinical dilemma by delegating behavioural delivery to trained nurses, physiotherapists, or allied health counselors. Consequently, physicians can refer insomnia patients to structured group programs without depleting precious diagnostic time during standard primary consultations. Furthermore, this collaborative delegation establishes a safer standard of care that preserves pharmacotherapy strictly as an acute, second-line intervention for short-term crises.
Implementing low-threshold group therapy yields crucial insights for healthcare systems aiming to modernize sleep medicine delivery. First, primary care clinics do not require highly specialized doctoral psychologists to achieve robust clinical improvements in insomnia severity. Instead, general nurses and community health workers can successfully guide structured four-week protocols after brief, standardized training in behavioural sleep medicine. Second, healthcare administrators must establish streamlined, direct referral pathways between general practices and community wellness centers. When physicians can easily prescribe an educational group course, patient enrollment and completion rates increase dramatically. Furthermore, clinicians should emphasize that four structured two-hour sessions represent an exceptionally cost-effective public health investment that prevents downstream chronic diseases. Chronic sleeplessness strongly accelerates cardiovascular disease, type 2 diabetes, mood disorders, and workplace accidents. Therefore, treating insomnia early in primary care produces substantial systemic savings across entire healthcare economies. Ultimately, adopting scalable group models ensures that evidence-based behavioural sleep therapies become accessible to broad populations rather than remaining an exclusive luxury reserved for tertiary private centers.
Rigorous clinical research demonstrates that group delivery achieves comparable symptom reduction, sleep efficiency gains, and medication tapering rates to individual therapy. Although individual sessions allow personalized pacing, group settings provide mutual peer encouragement, reduce patient isolation, and dramatically increase healthcare provider scalability without compromising overall therapeutic efficacy.
Stimulus control and sleep restriction therapy constitute the most potent active components of behavioral sleep interventions. Stimulus control breaks conditioned nocturnal arousal by restricting bedroom activities to sleep and intimacy, whereas sleep restriction temporarily consolidates sleep by systematically aligning time spent in bed with actual total sleep duration.
Yes, community health nurses, physiotherapists, and allied medical personnel can effectively conduct structured four-session group protocols following brief, standardized training. Real-world pragmatic trials confirm that these allied professionals achieve therapeutic outcomes comparable to specialized psychotherapists, making group programs exceptionally practical for routine community implementation.
Disclaimer: This content is for informational and educational purposes only and should not be considered medical advice or a substitute for professional clinical judgment. Treatments and interventions must be tailored to the individual patient’s clinical presentation. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A pragmatic multicentre randomized controlled trial shows that low-threshold group-delivered cognitive behavioural therapy for insomnia (CBT-I) achieved meaningful symptom reduction in primary care, offering an evidence-based, scalable non-pharmacological alternative to long-term sedative use.
Today
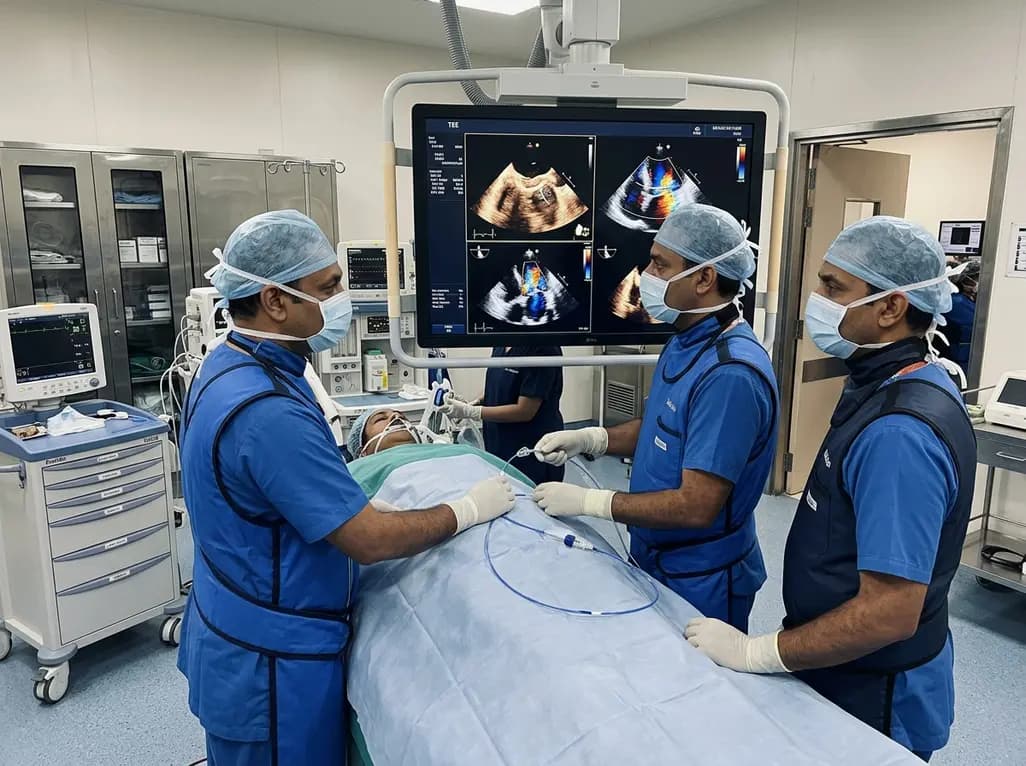
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today
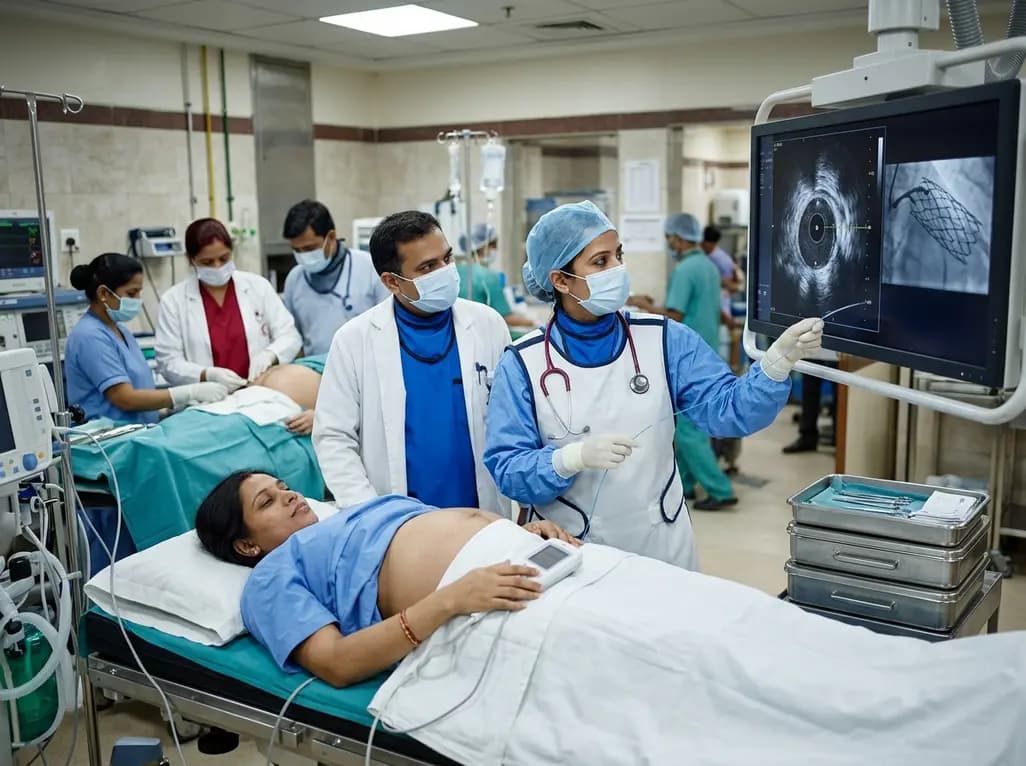
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday
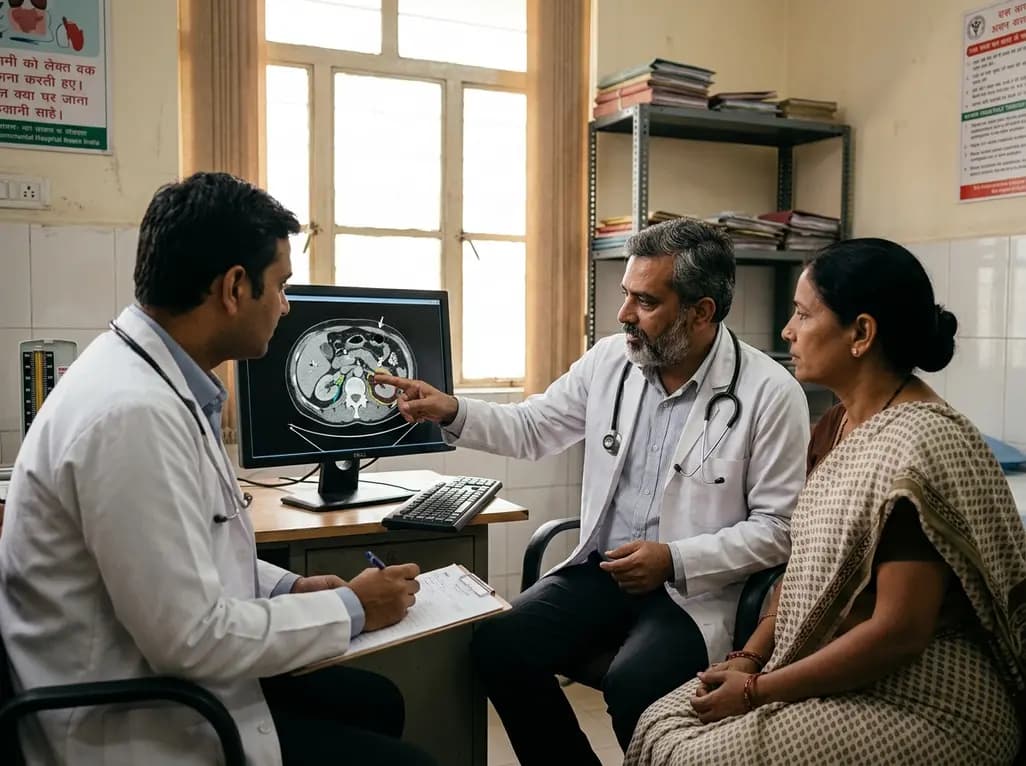
New ADIPO-CKD study findings demonstrate that both GLP-1 receptor agonists and SGLT2 inhibitors significantly reduce perirenal adipose tissue thickness in chronic kidney disease patients, with GLP-1 therapy achieving greater reductions, highlighting a novel mechanism for cardiorenal metabolic protection.
Today
