

Loading, please wait...
Loading, please wait...

Gestational glucose intolerance represents an abnormal one-hour glucose challenge during pregnancy without reaching formal criteria for gestational diabetes mellitus. Historically, clinicians routinely reassured pregnant individuals who failed their initial 50-gram screening test but subsequently passed the diagnostic evaluation. However, emerging metabolic evidence proves that borderline maternal dysglycemia carries enduring cardiometabolic penalties. In a groundbreaking investigation published in The Journal of Clinical Endocrinology & Metabolism, investigators analyzed the physiologic underpinnings of this condition. Specifically, the study demonstrates that maternal glucose elevation is not a benign, transient event. Instead, it serves as a sensitive harbinger of persistent beta-cell and peripheral tissue dysfunction. Therefore, classifying women based solely on binary disease definitions overlooks vulnerable cohorts at high risk for future dysglycemia. By investigating physiological phenotypes early during pregnancy, endocrinologists and obstetricians can identify targeted mechanistic deficits. Consequently, clinicians gain actionable insights into subsequent chronic disease trajectories. This paradigm shift encourages proactive metabolic vigilance well beyond the immediate postpartum recovery window. Furthermore, treating gestational glucose intolerance as an early metabolic indicator empowers primary care teams to intervene before permanent glycemic decompensation takes place.
Researchers historically treated hyperglycemia in pregnancy as a uniform pathophysiologic entity. In contrast, modern diabetology recognizes distinct metabolic mechanisms that drive impaired glucose tolerance. To delineate these pathways, the study team assessed fasting glucose and insulin levels between 16 and 20 weeks of gestation using homeostasis model assessment. Subsequently, they categorized participants into three primary physiological phenotypes: insulin resistant, insulin deficient, and mixed pathophysiology. The insulin-resistant subtype exhibited preserved or exaggerated beta-cell secretion alongside significant peripheral tissue insensitivity. Conversely, the insulin-deficient subtype demonstrated impaired early insulin secretion despite relatively preserved peripheral insulin sensitivity. Furthermore, the mixed cohort exhibited both severe peripheral resistance and inadequate compensatory pancreatic secretion. Interestingly, insulin resistance represented the most common presentation among affected participants. Nevertheless, a substantial portion displayed predominant secretory failure. These distinct profiles highlight that maternal dysglycemia arises through fundamentally divergent biological pathways. Thus, recognizing these underlying drivers provides an objective foundation for personalized maternal metabolic management. Moreover, identifying the specific physiological subtype enables clinicians to forecast distinct postpartum cardiometabolic risks with greater clinical precision.
During nearly a decade of clinical follow-up, researchers meticulously tracked maternal metabolic status across all study cohorts. Strikingly, nearly thirty percent of women with gestational glucose intolerance developed prediabetes or overt type 2 diabetes. Furthermore, longitudinal survival models demonstrated that all physiological subtypes experienced an increased risk compared to individuals with normal glucose tolerance. Women exhibiting the insulin-resistant subtype faced an elevated hazard ratio of 1.7 for subsequent dysglycemia. Similarly, individuals with isolated insulin deficiency carried an almost identical risk profile. Most notably, the mixed pathophysiology cohort experienced the highest vulnerability, with a hazard ratio exceeding 2.0. Hence, the coexistence of defective secretion and insulin resistance amplifies metabolic decline over time. Consequently, healthcare providers must acknowledge that even mild gestational glycemic elevations portend permanent pancreatic stress. While diagnostic criteria often dichotomize clinical care, longitudinal maternal biology operates along a continuous spectrum of risk. Therefore, postpartum metabolic evaluation remains essential regardless of whether patients met formal criteria for gestational diabetes. In addition, ongoing surveillance helps identify impaired fasting glucose before cardiovascular damage ensues.
Why does gestational glucose intolerance correlate so robustly with future metabolic deterioration? Pregnancy naturally induces progressive physiological insulin resistance to prioritize nutrient delivery to the growing fetus. Consequently, maternal pancreatic beta cells must dramatically increase insulin output to maintain euglycemia. When underlying cellular vulnerability exists, the pancreas fails to compensate adequately. In patients with insulin-resistant phenotypes, chronic hyperinsulinemia accelerates hepatic steatosis, vascular stiffness, and adipocyte inflammation. Conversely, in patients with intrinsic beta-cell defects, glucotoxicity and metabolic exhaustion progressively diminish insulin secretory reserves. After delivery, placental hormones clear rapidly, which temporarily restores maternal glycemic balance. However, the intrinsic subclinical defects persist beneath the surface. Over the subsequent decade, age-related metabolic decline and lifestyle stressors overwhelm the fragile metabolic equilibrium. Therefore, an abnormal prenatal screening test unmasks latent physiological susceptibility years before overt disease manifests. Understanding these cellular mechanisms helps clinicians anticipate complications and counsel patients effectively during regular health maintenance visits. Ultimately, early cellular stress signals provide invaluable predictive data regarding lifetime metabolic trajectory and vascular resilience.
These findings carry immense clinical significance for medical practitioners across India and South Asia. South Asian women exhibit a well-documented phenotype characterized by increased visceral adiposity, higher baseline insulin resistance, and premature beta-cell exhaustion. As a result, the prevalence of pregnancy-related dysglycemia is exceptionally high across Indian urban and rural demographics. Historically, many Indian pregnant women who test negative on formal secondary diagnostic testing receive no structured metabolic follow-up. Unfortunately, this clinical oversight misses a vital window for early lifestyle and therapeutic intervention. Because Indian women transition rapidly from gestational dysglycemia to chronic prediabetes and young-onset type 2 diabetes, proactive surveillance is paramount. Physicians should actively track fasting plasma glucose and glycated hemoglobin within six to twelve weeks postpartum. Furthermore, primary care teams must advocate sustained physical activity, culturally tailored balanced nutrition, and weight optimization. Obstetricians should also document abnormal screening values clearly in post-discharge summaries to guide primary care providers. In summary, bridging prenatal observations with proactive postpartum preventive care safeguards long-term maternal cardiometabolic health across diverse healthcare settings.
Gestational glucose intolerance describes an abnormal screening result on a one-hour glucose challenge test, typically measuring 140 mg/dL or higher, followed by normal diagnostic oral glucose tolerance testing. In contrast, gestational diabetes requires meeting explicit diagnostic thresholds on the multi-hour diagnostic test. Although patients with glucose intolerance do not meet formal diabetic criteria during pregnancy, they retain a significantly elevated risk for postpartum prediabetes and type 2 diabetes.
Different physiologic subtypes reflect distinct underlying cellular impairments, such as primary peripheral insulin resistance, isolated pancreatic beta-cell secretory dysfunction, or a combination of both mechanisms. While isolated insulin resistance strains skeletal muscle and hepatic glucose uptake, beta-cell deficiency limits compensatory insulin production. Patients presenting with mixed pathophysiology experience both defects simultaneously, which accelerates pancreatic exhaustion and results in the highest long-term risk of developing chronic prediabetes and diabetes.
Indian clinicians should recommend structured postpartum metabolic follow-up rather than offering false reassurance. Healthcare providers should schedule fasting plasma glucose or oral glucose tolerance testing at six to twelve weeks postpartum, accompanied by annual glycated hemoglobin assessments. Additionally, clinicians must emphasize targeted lifestyle interventions, including culturally tailored balanced nutrition, regular aerobic and resistance exercise, and healthy weight maintenance to prevent or delay the onset of overt diabetes.
Disclaimer: This content is for informational and educational purposes only and should not be considered as medical advice. Healthcare professionals should make clinical decisions based on their independent judgment and individual patient circumstances. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A landmark study reveals that physiologic subtypes of gestational glucose intolerance, including insulin resistance and insulin deficiency, independently raise long-term risks of maternal prediabetes and diabetes, underscoring the urgent need for structured postpartum surveillance.
Today
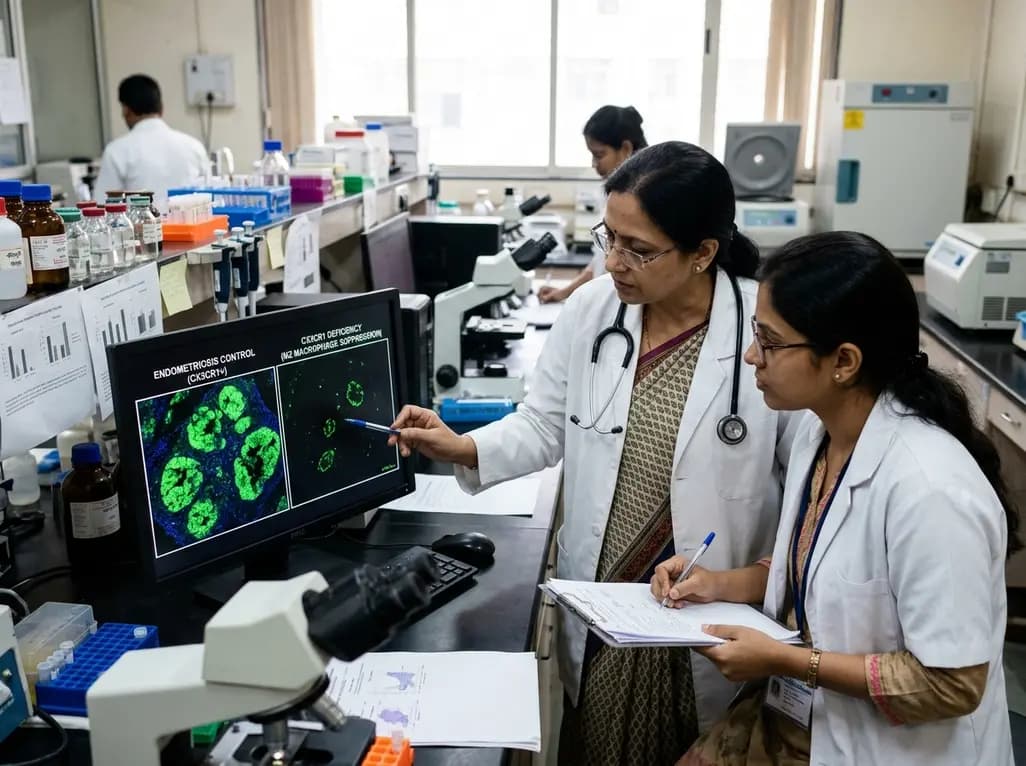
Groundbreaking experimental research demonstrates that CX3CR1 deficiency significantly attenuates endometriotic lesion growth by suppressing pro-repair M2 macrophage polarization. This discovery identifies the CX3CL1-CX3CR1 chemokine axis as a promising non-hormonal target for managing chronic endometriosis.
Today
A systematic review and component network meta-analysis evaluated the incremental benefits of drug classes in HFmrEF and HFpEF. SGLT-2 inhibitors and MRAs provided the most robust reductions in heart failure hospitalizations, while mortality benefits remained elusive across all investigated drug classes.
Today

A meta-analysis of 19 studies reveals that 69% of ophthalmologists suffer from work-related musculoskeletal disorders. Slit lamps, microscopes, and high surgical loads cause severe cervical and lumbar strain, underscoring the urgent need for ergonomic workstations, micro-breaks, and institutional reforms.
Today

Mayo Clinic trials and real-world datasets show GLP-1 receptor agonists improve left ventricular remodeling, reduce intracardiac filling pressures, decrease hospitalizations by 34%, and lower geriatric fall risks in patients with obesity and heart failure, delivering notable clinical and economic benefits.
Today
