

Loading, please wait...
Loading, please wait...

Clinical evaluations of major depressive disorder and bipolar disorder frequently measure recovery through numerical symptom scales and workplace productivity. However, these conventional metrics often fail to capture real-world patient priorities. Qualitative research shows that understanding functioning in mood disorders requires examining internal identity, personal autonomy, and relational vitality. A recent meta-synthesis of thirty-eight qualitative studies across seventeen countries analyzed the lived experiences of 679 participants. The findings demonstrate that patients perceive everyday capability through deeply nuanced psychological dimensions rather than simple symptomatic remission. Therefore, clinicians must reorient psychiatric care to support multifaceted functional recovery.
Traditional clinical assessments frequently define occupational performance and basic activities of daily living as primary indicators of clinical wellness. However, service users define their functional reality through much broader personal benchmarks. Participants across diverse cultural backgrounds consistently explain that daily ability fluctuates well beyond formal employment duties. For instance, individuals frequently describe functioning as the emotional bandwidth needed to pursue creative interests and enjoy personal hobbies. Furthermore, patients emphasize that symptom abatement without meaningful personal activity feels largely hollow. When clinicians prioritize quantitative rating scales over lived daily realities, they risk overlooking persistent cognitive deficits and emotional exhaustion. Consequently, treating physicians and psychiatric nurses must actively integrate qualitative inquiry during routine outpatient reviews. Clinicians should specifically explore what patients value most in their immediate social and domestic environments. By incorporating individualized goals into collaborative treatment plans, healthcare teams foster greater personal agency, therapeutic alliance, and treatment adherence. Therefore, modern psychiatric management must evaluate holistic fulfillment alongside standard functional benchmarks.
A dominant meta-theme emerging from qualitative investigations involves the profound erosion of personal identity during mood episodes. Severe depressive episodes and manic states systematically strip away self-worth, agency, and confidence. Consequently, patients frequently feel detached from their core values, describing their diagnosis as an overwhelming, alien force. Functional recovery therefore represents an active, ongoing effort to reclaim a coherent sense of self. Furthermore, this internal rebuilding requires patients to distinguish their authentic character from the episodic manifestations of their affective disorder. When individuals successfully separate illness symptoms from personal integrity, their self-efficacy improves dramatically. Mental health professionals play an essential role in facilitating this psychological reconstruction. Clinicians can introduce reflective psychotherapeutic exercises and narrative therapies that reinforce personal strengths rather than deficits. In addition, encouraging patients to acknowledge incremental victories helps counteract chronic self-doubt. By validating the struggle of identity reclamation, practitioners empower individuals to reconstruct stable, self-directed lives that transcend periodic affective fluctuations.
Mood disorders severely disrupt social networks, intimate partnerships, and family dynamics. During depressive phases, individuals often withdraw socially because communication feels utterly exhausting and overwhelming. Conversely, manic episodes can strain relationships through impulsive actions, irritability, or erratic behaviors that alienate close loved ones. As a result, participants identify relational reconnection as a vital pillar of functional rehabilitation. Rebuilding meaningful bonds provides emotional validation, decreases vulnerability, and reduces the risk of despair. Nevertheless, re-establishing social intimacy requires considerable courage and emotional energy. Patients often fear judgment or rejection from peers who may not understand fluctuating mood symptoms. Clinicians must actively assist patients in repairing damaged interpersonal bridges. For example, structured communication training and family-focused psychoeducation help relatives understand affective volatility without assigning personal blame. Moreover, peer support groups provide safe spaces where service users share practical coping mechanisms without fear of ostracism. When patients establish reciprocal, supportive relationships, their functional trajectory and psychological resilience improve substantially.
Long-term functional stability depends heavily on a patient's capacity to master proactive mood management strategies. Participants in qualitative studies describe mood regulation not as passive adherence to medication, but as an active, daily discipline. Specifically, successful self-management requires meticulous monitoring of early warning signs, maintaining consistent sleep hygiene, and regulating circadian rhythms. Patients emphasize that recognizing subtle hypomanic shifts or prodromal depressive feelings enables timely intervention before severe functional decline occurs. In addition, lifestyle modifications such as balanced physical exercise and structured daily schedules provide vital neurobiological stabilization. However, maintaining these rigorous routines demands immense psychological endurance and continuous cognitive effort. Healthcare providers must collaborate closely with patients to co-create personalized wellness action plans. Nurses and therapists can deliver practical behavioral tools, including daily mood charting and stress-inoculation techniques. Consequently, when clinicians validate self-management efforts rather than imposing rigid directives, patients gain confidence in navigating unavoidable affective shifts. Ultimately, self-directed management transforms vulnerable patients into resilient partners in long-term health.
The qualitative synthesis highlights a striking disparity regarding stigma between diagnostic categories. While individuals with unipolar depression experience significant societal misunderstanding, participants with bipolar disorder face exceptionally severe and pervasive prejudice. Public stereotypes associating mania with unpredictability, violence, or moral weakness generate profound social apprehension. Consequently, individuals with bipolar disorder frequently internalize this societal discrimination, resulting in crippling self-stigma and secrecy. In the workplace, fear of disclosure prevents patients from requesting reasonable accommodations, which accelerates occupational burnout and job loss. Furthermore, institutional stigma within healthcare settings occasionally leads clinicians to dismiss legitimate physical concerns as psychiatric symptoms. To dismantle these destructive barriers, multidisciplinary mental health teams must champion anti-stigma initiatives at every level of care. Clinicians should openly discuss stigma during clinical consultations, validating patient hesitations regarding diagnosis disclosure. Moreover, psychiatric professionals should advocate for inclusive workplace policies and deliver community-wide educational programs that demystify bipolar conditions. Reducing systemic stigma directly restores dignity, encourages social participation, and secures long-term functional recovery.
Integrating these qualitative findings into clinical practice requires a paradigm shift across mental health nursing and psychiatric care. Traditional treatment models predominantly concentrate on acute symptom stabilization through pharmacotherapy. However, full recovery requires healthcare providers to prioritize the human experience of functioning alongside biological management. Mental health nurses occupy an exceptional frontline position to deliver this holistic care. Because nurses engage with patients across diverse settings, they can assess subtle functional impediments that formal consultations miss. Specifically, nurses can implement recovery-oriented interventions that rebuild identity, strengthen social connections, and enhance daily problem-solving abilities. Furthermore, collaborative goal-setting allows clinicians to align medical therapies with personal aspirations, including returning to parenting or community work. Establishing multidisciplinary support systems ensures continuous care during vulnerable transitional phases. By moving beyond symptom suppression and embracing patient-defined outcomes, psychiatric practitioners help service users achieve durable, fulfilling lives. Ultimately, listening to patient voices transforms functional assessment from an administrative chore into a catalyst for profound personal healing.
Standard psychiatric rating scales typically measure symptom reduction, work attendance, and basic self-care tasks. In contrast, patients view functioning through qualitative dimensions such as reclaiming identity, enjoying social bonds, experiencing creative vitality, and maintaining emotional autonomy. Patients prioritize meaningful daily engagement over simple numerical score improvements.
Bipolar disorder carries greater public misconceptions due to unpredictable manic presentations, media sensationalism, and exaggerated stereotypes regarding behavioral volatility. Consequently, individuals with bipolar disorder face harsher workplace discrimination, greater social alienation, and deeper internalized self-stigma, which collectively compromise their functional recovery far more severely than depression.
Clinicians can utilize narrative therapy and strengths-based psychological interventions to help patients decouple their personal identity from diagnostic labels. Furthermore, encouraging incremental daily achievements, establishing peer support, and promoting creative self-expression validate personal agency, enabling patients to rebuild durable self-worth and confidence beyond their affective illness.
Disclaimer: This content is for informational and educational purposes only. It does not constitute formal medical advice, diagnosis, or treatment recommendations. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A qualitative meta-synthesis of 38 studies reveals that functioning in mood disorders extends far beyond symptom remission. Patients define recovery through four core meta-themes: sense of self, interpersonal connection, active mood management, and overcoming stigma, guiding clinical and psychiatric nursing care.
Today

Cardiac involvement is the leading cause of mortality in EGPA. This report highlights an overlap phenotype of lymphocyte-predominant myocardial injury, Takotsubo-like cardiomyopathy, and left ventricular thrombus, emphasizing early multimodality diagnostics and aggressive immunosuppressive biologic therapy.
Today
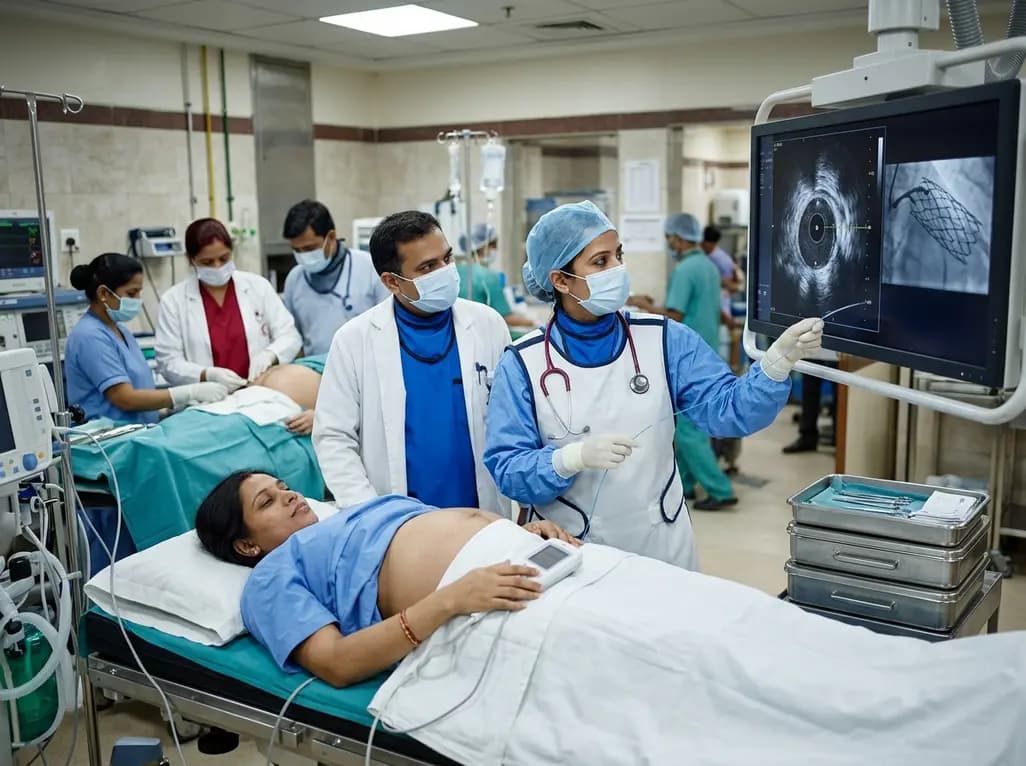
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today
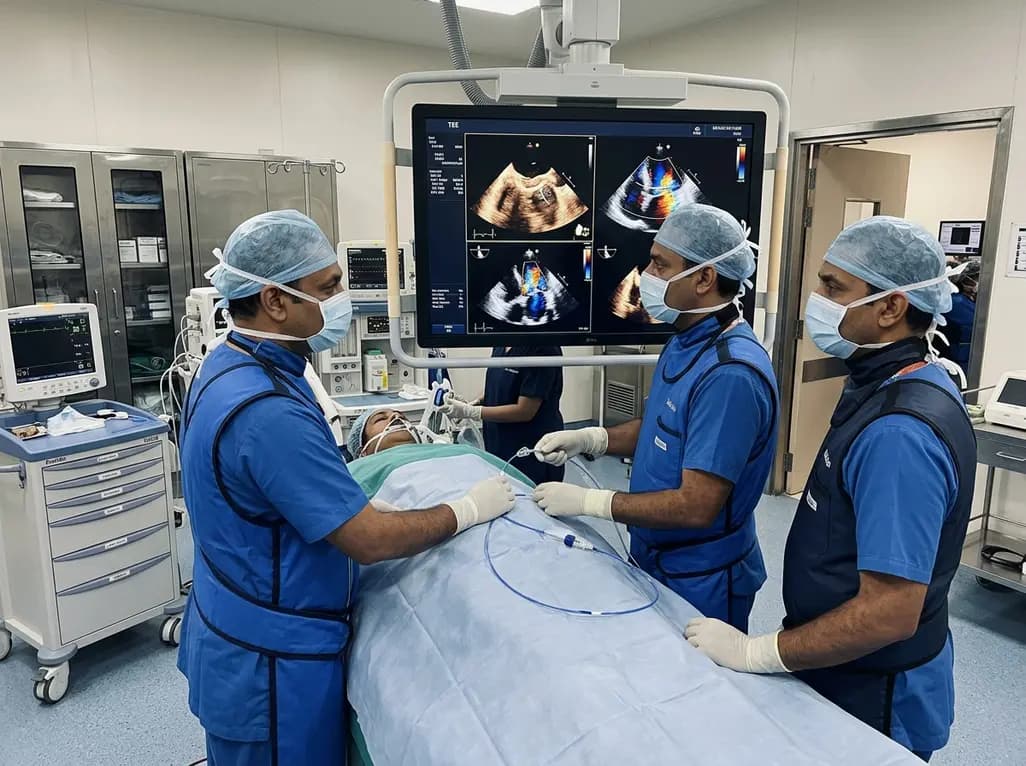
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today
