

Loading, please wait...
Loading, please wait...

Clinicians frequently instruct patients with metabolic disorders to eat home-cooked meals. However, prescriptive dietary advice often overlooks whether patients possess true food agency in their daily lives. Food agency describes an individual's practical ability to procure, organize, and prepare wholesome foods within real-world environments. When clinicians ignore these environmental determinants, patients often struggle to sustain recommended dietary modifications. Consequently, chronic cardiometabolic diseases continue to escalate across vulnerable patient populations. Concept mapping research demonstrates that daily cooking behaviors depend heavily on structural conditions. While patients understand basic nutritional guidelines, their cooking habits reflect immediate environmental realities. For instance, individuals must balance financial budgets, culinary skills, transport access, and working hours. Moreover, geographic location profoundly shapes the availability and affordability of nutritious groceries. Primary care physicians and clinical dietitians must therefore assess these baseline capacities during clinical visits. Evaluating these practical elements allows medical practitioners to formulate realistic lifestyle prescriptions. Furthermore, understanding the structural determinants of cooking empowers healthcare teams to support lasting behavior change. Ultimately, bridging clinical advice and domestic practice requires a clear appreciation of everyday constraints.
Recent mixed-methods concept mapping investigations reveal four foundational domains governing daily cooking actions. Specifically, researchers identify ingredient-related, time-related, health-related, and motivational factors as universal drivers. These critical domains represent a dynamic balance between personal capabilities and external social constraints. For example, health and nutrition priorities appear universally valued across both urban and rural demographics. Patients generally recognize the vital connection between wholesome ingredients and long-term metabolic health. Nevertheless, knowledge alone cannot guarantee home cooking when severe external barriers intervene. Time-related constraints frequently conflict with complex cooking processes, especially when long working hours dominate schedules. Additionally, physical ingredient access dictates whether a patient can prepare balanced meals at home. If local markets fail to stock affordable fresh produce, patients cannot execute clinical recommendations. Furthermore, motivational factors determine whether individuals feel emotionally capable of cooking after exhausting workdays. These interconnected domains prove that cooking behavior rarely stems from personal willpower alone. Therefore, clinicians must recognize that external environmental barriers frequently overpower personal intentions. Without addressing these practical dimensions, standard dietary advice yields minimal clinical benefit.
While universal domains exist, their practical manifestation varies dramatically across different residential environments. In urban and suburban settings, residents navigate a dense commercial landscape with abundant retail options. Consequently, urban-suburban individuals frequently frame home cooking around culinary variety, novel recipes, and creative expression. These home cooks often enjoy direct access to specialized supermarkets and diverse ethnic grocery stores. However, urban living also imposes severe time pressures that frequently disrupt consistent meal preparation routines. Demanding corporate schedules, extended traffic commutes, and ubiquitous food delivery applications discourage regular domestic cooking. As a result, urban professionals often view cooking as an occasional hobby rather than a daily habit. Furthermore, reliance on packaged convenience foods introduces hidden sodium, trans fats, and refined carbohydrates into diets. Clinicians counseling urban patients must explicitly address these lifestyle trade-offs during clinical consultations. Rather than recommending complex traditional cooking, practitioners should advocate realistic meal assembly strategies. For instance, clinicians can suggest batch-cooking grains and utilizing pre-cut vegetables to save valuable time. Tailoring nutritional counseling to modern urban schedules significantly enhances long-term dietary compliance.
In sharp contrast to metropolitan areas, rural and remote populations encounter distinct socioeconomic and physical hurdles. Geographic isolation and fewer commercial grocery stores restrict access to diverse produce and specialty ingredients. Therefore, rural residents depend heavily on regional staples, local growers, discount stores, and home gardening. Motivational drivers in rural households also diverge substantially from patterns observed in urban cohorts. Rather than pursuing novelty or culinary creativity, rural cooks prioritize preparing meals that satisfy collective family tastes. Because household budgets are frequently constrained, cooks avoid unfamiliar recipes that risk costly food waste. If family members reject an experimental healthy meal, the emotional and financial burden falls on the cook. Moreover, multi-generational households often expect traditional comfort foods rich in energy and familiar flavors. Healthcare providers serving rural communities must respect these familial expectations and cultural values. Instead of prescribing isolated individual diets, clinicians should help patients modify shared family recipes. By enriching traditional dishes with affordable local vegetables and legumes, clinicians foster household-wide health improvements. This collaborative strategy minimizes familial resistance and dramatically strengthens clinical adherence.
These geographic disparities demonstrate that conventional, one-size-fits-all dietary advice cannot produce equitable outcomes. Historically, medical dietary counseling has relied on didactic instructions that emphasize nutrient restrictions and forbidden items. However, didactic instruction regularly fails because it ignores an individual's environmental agency and structural limitations. Medical educators and practicing clinicians must transition toward participatory, collaborative nutrition education models. Participatory counseling actively invites patients to identify their specific logistical hurdles, time constraints, and domestic priorities. For example, clinicians can explore which healthy ingredients are physically available in the patient's local neighborhood. Furthermore, providers can assess whether recommended cooking techniques align with available kitchen appliances and schedule realities. Integrating culinary medicine principles into primary care offers a practical roadmap for addressing chronic metabolic diseases. By teaching actionable food navigation skills alongside clinical guidelines, clinicians empower patients to take charge of health. Ultimately, measuring and supporting food agency enables healthcare teams to deliver realistic, compassionate, and effective nutritional guidance. This patient-centered approach transforms routine lifestyle counseling into a sustainable therapeutic partnership.
Basic cooking skills refer strictly to mechanical culinary techniques, such as chopping vegetables or boiling grains. In contrast, food agency encompasses a comprehensive capacity to plan, procure, adapt, and prepare nutritious meals within specific socioeconomic environments. It incorporates cognitive problem-solving, financial budgeting, time management, and emotional resilience. Therefore, a person may possess advanced technical skills yet lack the food agency required to overcome exhausting work schedules or limited grocery access.
Rural households often operate under strict grocery budgets and limited ingredient availability, making food waste a critical financial concern. When primary cooks experiment with unfamiliar ingredients or exotic recipes, they risk household meal rejection. Consequently, rural home cooks prioritize dishes that every family member readily eats. Moreover, shared multi-generational meals reinforce cultural bonds and daily traditions, encouraging caregivers to prepare dependable, familiar staples rather than pursuing individual culinary experimentation or varied recipes.
Physicians can easily integrate culinary medicine by asking targeted questions about home food preparation routines during lifestyle reviews. Clinicians should identify whether time, cooking equipment, or ingredient access impedes dietary compliance. Instead of prescribing rigid diet sheets, practitioners should recommend simple ingredient substitutions, batch cooking, and realistic modifications of traditional household recipes. Connecting patients with clinical dietitians and community cooking workshops further reinforces practical skills, empowering individuals to achieve long-term metabolic health.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Yi J et al. Exploring Facilitators and Barriers of Cooking and Food Preparation Among Urban-Suburban and Rural-Remote Residents: A Mixed-Methods Concept Mapping Study. J Nutr Educ Behav. 2026 Sep 17. doi: undefined. PMID: 42752051.
Lahne J, Wolfson JA, Trubek A. Cooking, Food Agency and Pro-Health Behavior. Curr Environ Health Rep. 2026; doi: 10.1007/s40572-026-00541-x. PMID: 42142215.
Trubek AB, Carabello M, Morgan C, Lahne J. Development of the Cooking and Food Provisioning Action Scale (CAFPAS): A new measurement tool for individual cooking practice. Appetite. 2017;118:43-53.
Park S, Kim K. Food Agency and Intentions to Improve Cooking Skills Among Korean Young Adults: Demographic Differences and Motivators. Nutrients. 2026;18(4):612. PMID: 41724012.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A mixed-methods concept mapping study reveals that while health goals are shared, cooking facilitators and barriers differ across urban and rural cohorts. Clinicians must assess food agency and social-structural factors to design effective, participatory dietary interventions.
Today
A bibliometric study maps global research on intimate partner violence during COVID-19, revealing a 17.08% publication growth rate and motor themes of mental health and social support. Clinicians require trauma-informed screening and systemic crisis preparedness to protect vulnerable women during ongoing crises.
Today
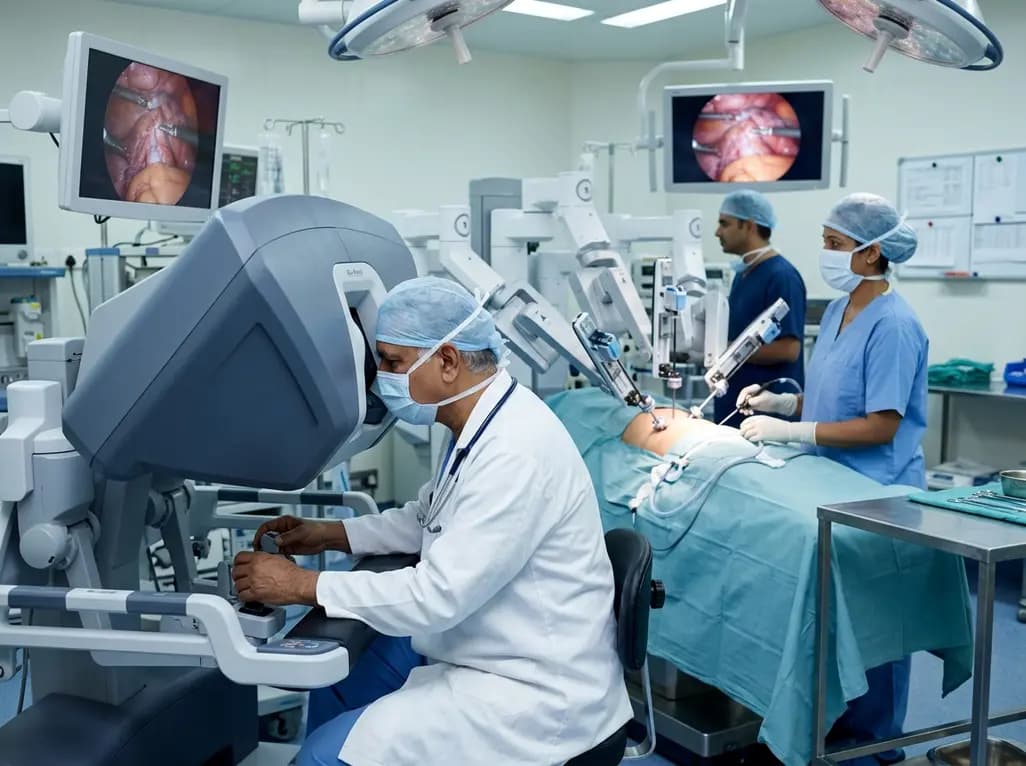
Surgical robotics is redefining modern operating theaters by replacing extensive open incisions with micro-dexterity and stereoscopic 3D vision. Multi-specialty surgeons highlight how robotic platforms mitigate tissue trauma, enhance functional organ preservation, and shorten postoperative hospital recovery.
Today
Piezoelectric amino acids and peptides convert mechanical stress into bioelectric cues. By mimicking endogenous electrical fields, these biodegradable biomaterials advance tissue regeneration, biosensing, antimicrobial therapy, and targeted oncology without leaving toxic residues.
Today

A network meta-analysis of 10 RCTs comprising 37,923 patients reveals that SGLT2 inhibitors offer the broadest cardiorenal protection in diabetic kidney disease. Dapagliflozin reduced kidney outcomes more than semaglutide, while finerenone increased hyperkalaemia and treatment discontinuation rates.
Today
