

Loading, please wait...
Loading, please wait...
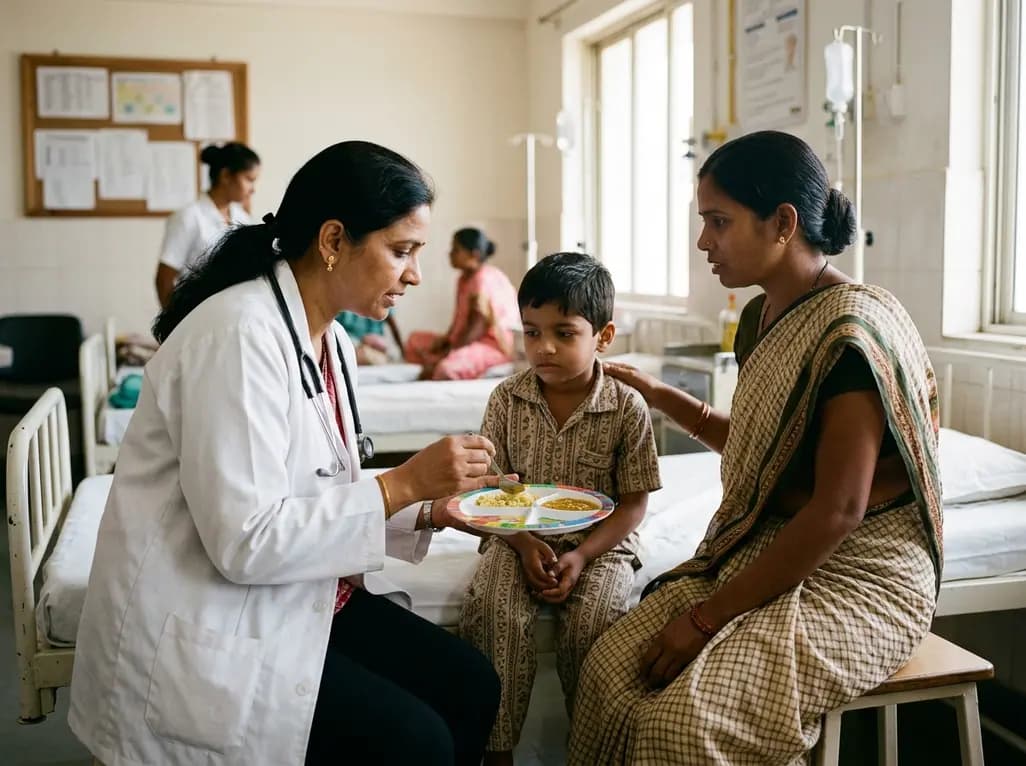
Managing feeding in neurodevelopmental disorders presents substantial clinical challenges for pediatricians, nurses, and dietitians. Children diagnosed with conditions like autism spectrum disorder and attention-deficit/hyperactivity disorder often experience pervasive mealtime distress. Consequently, these feeding difficulties frequently lead to restricted dietary variety, micronutrient deficiencies, and compromised physical growth. Recent epidemiological data indicate that feeding challenges affect up to eighty percent of neurodivergent children. In contrast, neurotypical peers encounter severe feeding disruptions far less frequently. Therefore, clinicians must routinely evaluate daily dietary quality during pediatric health checkups.
Furthermore, early childhood nutrition directly influences neurodevelopment, behavioral stability, and immune function. When mealtime distress dominates the home, chronic nutritional deficits quickly impair long-term physical growth trajectories. In addition, unaddressed feeding difficulties exacerbate gastrointestinal issues, including chronic constipation and abdominal pain. Because mealtime participation requires complex sensory processing and oral-motor coordination, clinicians must recognize these challenges as neurodevelopmental vulnerabilities. Ultimately, proactive nutritional screening represents a critical clinical priority for vulnerable pediatric patients.
Recent comparative cross-sectional research offers vital empirical evidence regarding mealtime quality in pediatric cohorts. Specifically, researchers evaluated two hundred and five children aged three to ten years across pediatric centers in China. The study cohort included ninety-one children with confirmed neurodevelopmental disorders alongside one hundred and fourteen typically developing peers. Investigators administered validated questionnaires, including the Nutrition Quotient for Preschoolers, while recording standardized anthropometric measurements. Consequently, this rigorous methodological design permitted precise comparisons of nutritional adequacy and eating patterns.
Notably, children with neurodevelopmental disorders demonstrated significantly lower overall nutrition scores compared to typically developing controls. The neurodivergent group scored an average of 55.19, whereas the neurotypical cohort achieved 62.01. Furthermore, multigroup structural equation modeling demonstrated that atypical eating behaviors directly compromised overall nutritional quality. In addition, necessary condition analysis confirmed that specific caregiver feeding practices significantly shaped these nutritional outcomes. Therefore, these clinical findings highlight that nutritional vulnerability stems from an intricate interaction between innate neurobehavioral characteristics and family feeding dynamics.
Children with neurodevelopmental disorders frequently present with atypical eating behaviors driven by underlying sensory processing differences. For example, severe food selectivity often restricts children to very specific food textures, temperatures, odors, or visual presentations. Consequently, many neurodivergent children reject entire food categories, particularly fibrous vegetables and protein sources. This pronounced food refusal often provokes substantial anxiety during structured family mealtimes. Moreover, heightened oral sensory sensitivity makes diverse textures feel physically overwhelming to the child.
Additionally, subtle oral-motor dyspraxia and coordination deficits can impede effective chewing and safe swallowing. As a result, children may choke, gag, or pocket food boluses within their cheeks. Furthermore, attentional fluctuations and hyperactivity prevent young patients from remaining seated for typical meal durations. When parents attempt to enforce rigid meal schedules, children frequently react with emotional distress or oppositional avoidance. Thus, pediatric clinicians must systematically assess these behavioral presentations. Recognizing that sensory anomalies and motor fatigue drive mealtime disruptions allows practitioners to design compassionate, targeted therapeutic plans.
Mealtime disturbances inevitably disrupt the broader family ecosystem, generating sustained caregiver stress and exhaustion. Because parents often worry about their child's physical growth, they experience significant anxiety during daily meal preparation. In response to persistent food refusal, caregivers frequently adopt compensatory strategies, including offering preferred calorie-dense snacks or applying coercive pressure. However, coercive feeding practices typically trigger oppositional resistance, transforming dining spaces into high-conflict battlegrounds. Consequently, family mealtimes become an emotionally draining ordeal rather than a calm, bonding experience.
Furthermore, structural equation modeling reveals that maladaptive caregiver feeding strategies unintentionally worsen dietary limitations. For instance, repeatedly preparing separate meals or yielding to rigid demands reinforces severe food selectivity over time. In contrast, parental feeding warmth and structured routines reliably foster better eating stability. Nevertheless, parents rarely receive evidence-based guidance on managing complex neurodivergent feeding challenges. As a result, many families experience profound isolation and unwarranted self-blame regarding their child's eating patterns. Therefore, healthcare teams must provide empathetic, family-centered support frameworks that actively bolster parental coping skills.
Pediatric nurses and primary clinicians occupy a critical front-line position for early nutritional evaluation and intervention. Specifically, routine clinical assessments must extend beyond standard growth charts and body mass index percentiles. While a child might maintain an acceptable weight through calorie-dense carbohydrates, they often harbor unrecognized micronutrient deficiencies. Therefore, clinical personnel should incorporate validated nutritional screening tools, such as the Nutrition Quotient for Preschoolers, during outpatient visits. In addition, screening protocols must evaluate meal duration, mealtime tantrums, and parent-child interactions.
Furthermore, managing neurodevelopmental feeding difficulties requires structured, sensory-informed intervention strategies. Clinicians should advise caregivers to establish predictable mealtime routines with visual schedules and designated seating. Caregivers can also expand limited food repertoires through systematic food chaining, introducing new items that share familiar textures or colors. Moreover, pediatric teams must address coexisting gastrointestinal discomfort, such as constipation, which frequently aggravates food refusal. Ultimately, multidisciplinary collaboration between pediatricians, nurses, occupational therapists, and dietitians empowers families and fosters sustainable nutritional improvement.
Children with neurodevelopmental disorders frequently experience heightened sensory sensitivity, oral-motor coordination difficulties, and rigid behavioral preferences. Consequently, they often reject diverse food textures, fresh vegetables, and protein sources, leading to restricted diets. Furthermore, associated gastrointestinal symptoms and mealtime anxiety compound these eating challenges, resulting in lower overall dietary quality and essential micronutrient deficiencies.
Caregivers should avoid coercive feeding practices and maintain predictable mealtime environments using visual cues. Additionally, parents can introduce unfamiliar foods through systematic food chaining, offering items similar in color and texture to accepted foods. Encouraging children to explore foods through touch and smell without pressure also desensitizes oral defensiveness. Consistent, stress-free exposure gradually expands dietary acceptance over time.
Pediatric nurses play an essential role by screening for atypical feeding behaviors, dietary diversity, and caregiver stress during clinical visits. Beyond monitoring anthropometric measurements, nurses evaluate mealtime dynamics and identify early nutritional risks using validated screening tools. Furthermore, they provide family-centered education and coordinate referrals to occupational therapists, pediatric neurologists, and specialized dietitians for comprehensive multidisciplinary care.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Sun S et al. Family-centered feeding support and nutritional quality in children with neurodevelopmental disorders: A comparative cross-sectional study. J Pediatr Nurs. 2026 Sep 26. doi: undefined. PMID: 42800766.
Bandini LG, Curtin C, Hamad C, et al. Food selectivity in children with autism spectrum disorders and typically developing children. J Pediatr. 2010;157(2):259-264.
Curtin C, Hubbard K, Anderson SE, et al. Food selectivity, mealtime behavior problems, spousal stress, and family functioning in families of children with autism spectrum disorder. J Autism Dev Disord. 2015;45(5):1378-1386.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A comparative study reveals children with neurodevelopmental disorders experience significantly lower nutritional quality and higher feeding constraints than peers. Pediatric nursing assessments and family-centered support strategies are essential to optimize dietary intake and mitigate caregiver burden.
Today

New evidence from the J-ECOH study demonstrates that exclusive and dual use of heated tobacco products significantly increases sleep latency and restless sleep among workers. These findings refute harm reduction claims, highlighting critical sleep health risks relevant to clinical counseling in India.
Today

A multiparametric MRI approach combining quantitative T2 shading, apparent diffusion coefficient (ADC) measurements, and morphological signs provides superior diagnostic accuracy over subjective evaluation to differentiate ovarian endometriomas from benign hemorrhagic cysts.
Today

Discover a novel laparoscopic approach for iatrogenic diaphragmatic hernia repair following pedicled omentoplasty. This modified Sugarbaker technique integrates dorsal pedicle lateralization and round ligament reinforcement to secure the diaphragmatic defect while preserving vital omental vascularity.
Yesterday
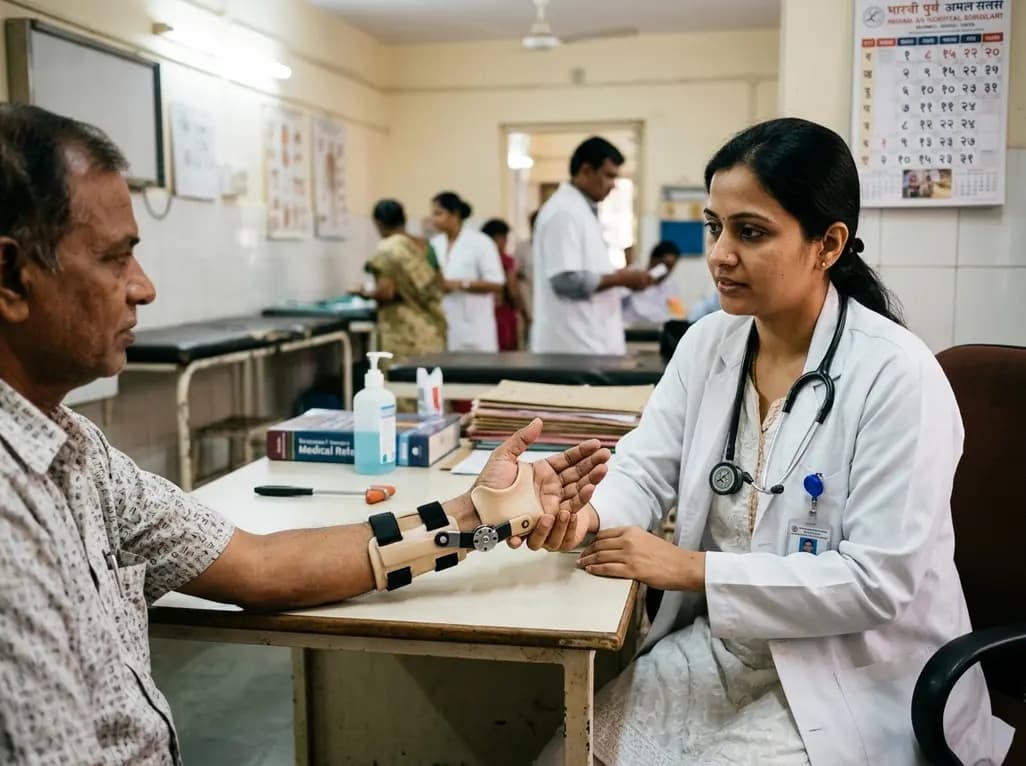
A new randomized crossover trial reveals that a hinged ulnar gutter orthosis significantly improves hand function and weight-bearing tolerance compared to standard volar splints in patients with degenerative triangular fibrocartilage complex lesions, supporting functionally permissive orthotic designs.
Today

New research reveals that M1 macrophage-derived exosomes aggravate diabetic nephropathy by transferring WTAP to stabilize S1PR2 mRNA. Silencing WTAP in these vesicles attenuates endothelial injury and renal fibrosis, pointing toward innovative nanomedicine therapies.
Today
