

Loading, please wait...
Loading, please wait...

Emergency departments worldwide face relentless crowding due to surges in non-urgent visits and minor acute complaints. Consequently, prolonged waiting times frequently compromise institutional efficiency and patient safety. A groundbreaking randomized clinical trial evaluated the nurse-led fast care model. The investigators tested whether early nursing assessment and dedicated leadership could optimize throughput for low-acuity presentations.
Hospital crowding strains healthcare personnel and disrupts clinical pathways. In particular, minor emergencies such as uncomplicated lacerations, isolated limb trauma, and mild infections consume disproportionate clinical bandwidth. Patients waiting for basic interventions often experience worsening discomfort, dissatisfaction, and unexpected clinical deterioration. Furthermore, conventional triage models frequently route low-acuity patients to general waiting areas where they linger behind critical resuscitations. Therefore, healthcare systems urgently require specialized throughput pathways. The fast care model resolves this organizational bottleneck through structured clinical leadership and dedicated nursing workflows. Instead of passively assigning a triage category, senior triage nurses immediately initiate diagnostic workups and symptomatic therapy. Moreover, these experienced clinicians provide continuous oversight until formal discharge or referral. By establishing early assessment protocols, the team prevents treatment stalls before they occur. Consequently, clinical teams preserve emergency department capacity for life-threatening pathologies without neglecting less severe illnesses. This proactive alignment creates a predictable rhythm for ambulatory patients. Ultimately, the framework transforms fragmented episodic triage into a smooth, accountable care continuum.
To validate this streamlined strategy, investigators executed a rigorous randomized clinical trial within a tertiary university emergency department. The research team recruited 801 consecutive adult patients presenting with minor acute emergencies. Subsequently, the researchers randomized eligible individuals in a 1:1 ratio to either the intervention or usual care. Patients assigned to the intervention received structured, nurse-led care characterized by immediate evaluation and sustained longitudinal tracking. In contrast, participants in the control cohort followed traditional departmental triage, registration, and physician-driven consultation queues. The primary investigational outcomes evaluated both initial waiting time and total departmental length of stay. Additionally, secondary metrics captured early walkouts, specifically measuring patients who left without being seen, alongside 72-hour emergency readmissions. Because the trial occurred in an active academic medical center, the findings directly reflect everyday operational challenges. Furthermore, robust baseline matching ensured comparable clinical characteristics across both arms, eliminating confounding baseline disparities. As a result, the methodological design provides high-grade evidentiary proof regarding clinical flow reorganization.
The quantitative outcomes demonstrated dramatic clinical and operational gains for patients managed under the specialized workflow. Specifically, participants in the intervention cohort achieved an impressive 77.6-minute reduction in initial waiting time compared to standard care. Furthermore, their active treatment time dropped by 156.9 minutes. This profound acceleration culminated in an overall departmental length of stay reduction of 178.1 minutes. Thus, patients completed their entire clinical journey nearly three hours faster than individuals navigating standard protocols. These statistical gains highlight the immense friction embedded within traditional physician-centered processing for low-acuity complaints. When experienced emergency nurses initiate standardized order sets, they eliminate redundant handover cycles. Moreover, rapid point-of-care diagnostics and immediate wound or analgesia protocols drastically shorten idle intervals. As a result, beds clear rapidly, and bed turnover accelerates significantly. Consequently, the entire emergency unit experiences less physical congestion and improved operational velocity. Emergency clinicians can therefore direct their undivided cognitive attention toward deteriorating patients in resuscitation suites.
Emergency department crowding frequently drives vulnerable individuals to abandon care prematurely. Patients who leave without complete medical evaluation face substantial risks of secondary infection, unmanaged fractures, and avoidable readmission. Notably, the trial uncovered a striking disparity in early departures between the study cohorts. In the usual care group, an alarming 32.2% of patients left before undergoing formal clinical evaluation. In stark contrast, only 2.5% of participants in the intervention arm departed before treatment completion. Thus, the streamlined pathway practically eliminated premature walkouts by establishing immediate therapeutic rapport and rapid relief. Furthermore, patients achieved full completion of their diagnostic and treatment pathways in almost every single instance. Interestingly, tracking 72-hour emergency readmissions revealed no increase in secondary returns among rapidly discharged patients. Hence, rapid processing did not compromise diagnostic safety or result in missed pathology. By maintaining continuous nursing oversight, the clinical team delivered safe, definitive care rather than superficial symptom masking. Consequently, early therapeutic engagement safeguards both patient health and medicolegal security.
Adopting this advanced operational structure yields compelling advantages for resource-limited hospitals and busy urban centers. In many international facilities, overburdened casualty wards struggle with severe bed shortages and prolonged diagnostic delays. However, successfully translating these trial results into clinical practice requires thoughtful institutional restructuring. First, hospital leadership must empower senior emergency nurses with standardized clinical protocols and credentialing privileges. For example, protocolized analgesic administration, basic radiographic ordering, and wound care algorithms expedite clinical throughput safely. Additionally, administrators must allocate dedicated physical space near triage to prevent ambulatory patients from occupying acute resuscitation stretchers. Interdisciplinary collaboration between attending physicians and clinical nursing leads also ensures rapid escalation whenever patient status changes. Furthermore, continuous audit loops must assess patient safety, return visits, and diagnostic accuracy. By investing in specialized nursing leadership, healthcare organizations unlock latent clinical capacity without expanding physical hospital infrastructure. Therefore, this model serves as an indispensable blueprint for modernizing emergency throughput worldwide.
The core principle centers on immediate nursing leadership and continuous patient oversight for low-acuity emergencies. Rather than relegating minor presentations to passive waiting queues, senior triage nurses promptly initiate validated diagnostic orders, analgesia, and wound care. Furthermore, this dedicated clinical oversight eliminates fragmented departmental handovers. Consequently, patients progress through an uninterrupted, focused trajectory that significantly shortens overall emergency dwell time while preserving vital clinical safety standards.
Prolonged waiting times represent the single greatest cause of emergency department walkouts. When low-acuity patients experience indeterminate delays without communication, many abandon care out of frustration or despair. However, early nurse assessment establishes immediate clinical connection and rapid symptomatic relief within minutes of arrival. Because patients recognize active diagnostic progress and attentive care, their anxiety dissipates rapidly. Therefore, completing the clinical journey becomes seamless, lowering walkout rates from 32.2% down to 2.5%.
Yes, resource-limited hospitals can readily adapt this methodology without substantial financial outlays. Implementing the pathway relies primarily on reorganizing operational staff workflows rather than acquiring costly new equipment. By empowering senior staff nurses with validated standing orders and creating an ambulatory sub-track, facilities decongest acute resuscitation zones. Furthermore, reducing bed bottlenecks allows emergency teams to manage high volumes efficiently. Consequently, this model delivers immense value in public hospitals confronting persistent patient crowding.
Disclaimer: This content is for informational and educational purposes only. It should not be used as a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A randomized trial of 801 patients reveals that a nurse-led Fast Care model reduces emergency department wait times by 77.6 minutes, cuts overall length of stay by nearly three hours, and slashes early departures from 32.2% to 2.5%, highlighting the power of clinical nursing leadership in minor emergencies.
Today
Cardiac involvement is the leading cause of mortality in EGPA. This report highlights an overlap phenotype of lymphocyte-predominant myocardial injury, Takotsubo-like cardiomyopathy, and left ventricular thrombus, emphasizing early multimodality diagnostics and aggressive immunosuppressive biologic therapy.
Today
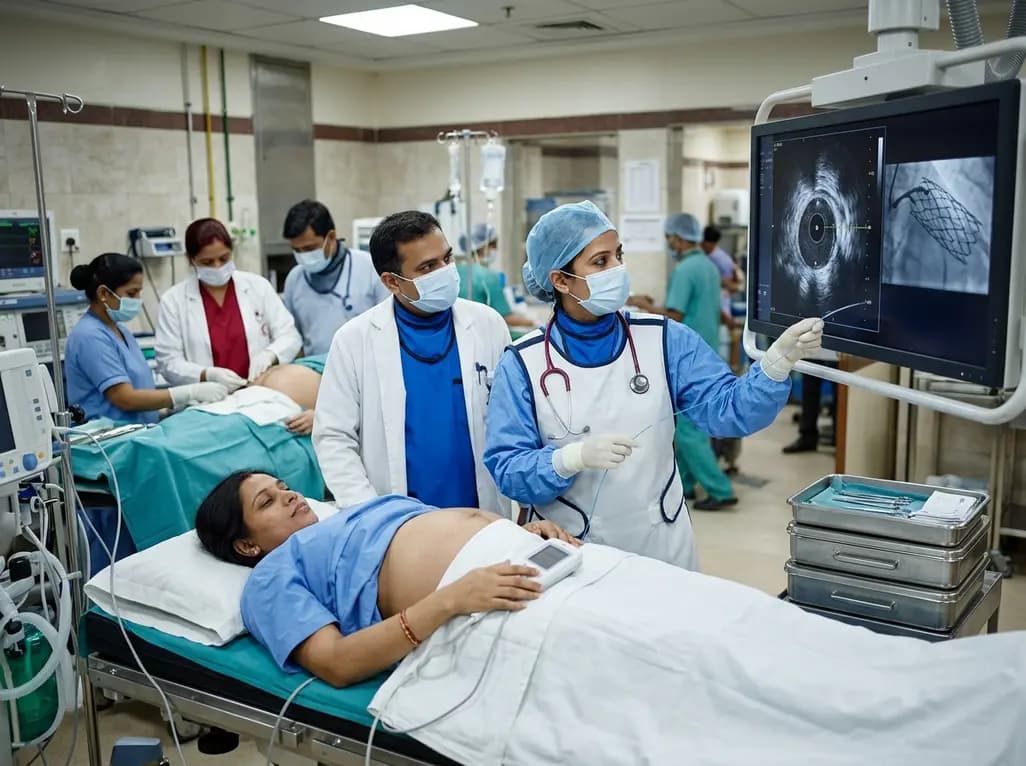
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today
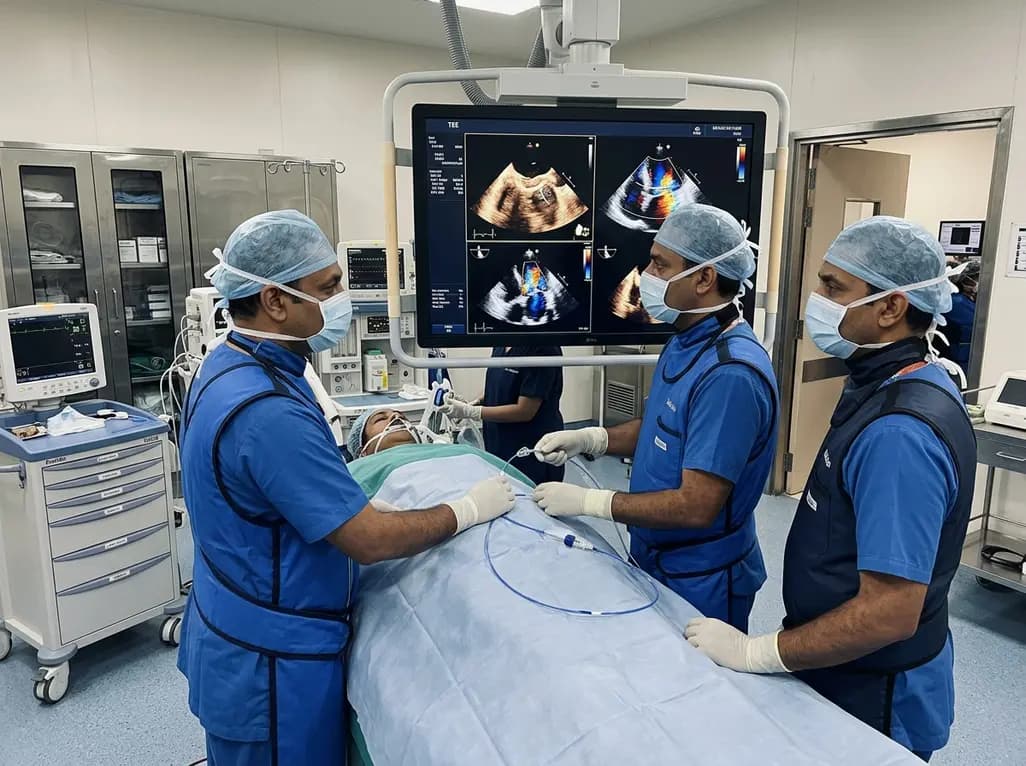
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today
