

Loading, please wait...
Loading, please wait...

Major depressive disorder represents a leading cause of global disability, imposing a profound clinical and economic burden on healthcare systems worldwide. For decades, clinicians have recognized that genetic liability heavily influences an individual's susceptibility to affective disorders. When evaluating psychiatric patients, clinicians routinely document a patient's family history of depression to estimate inherited predisposition. This generational aggregation offers vital diagnostic clues regarding shared genomic architecture as well as early household environment. However, conventional clinical inquiries frequently condense this rich genealogical background into an overly simplistic yes-or-no question. Such dichotomous classifications inevitably ignore essential epidemiological variables, including overall family size, degree of biological relatedness, and age at illness onset. Consequently, simple questions fail to represent the continuous nature of genetic risk across complex pedigrees. In recent years, genomic advancements have introduced molecular polygenic scores calculated from massive genome-wide association studies. While polygenic scoring provides an objective molecular index of vulnerability, DNA genotyping remains economically impractical for routine primary healthcare clinics in many countries. Therefore, psychiatric epidemiologists seek to optimize clinical pedigree assessment through advanced statistical methodologies like the liability threshold model. Analyzing how mathematically refined genealogical scores perform relative to molecular scores illuminates superior avenues for psychiatric risk stratification. Understanding these complementary assessment strategies empowers healthcare professionals to deliver more tailored clinical interventions.
Biostatisticians and genetic epidemiologists evaluate diverse mathematical methods to synthesize familial psychiatric diagnoses into calibrated prognostic scores. In daily practice, clinicians historically utilize dichotomous indicators, merely noting whether any biological relative has suffered from a major affective episode. Alternatively, clinical investigators frequently compute proportional indicators, which quantify the exact ratio of affected first-degree relatives relative to total family size. Although proportional indices clearly improve statistical accuracy, they still fail to adjust for differential heritability or baseline population disease rates. To address these persistent analytical limitations, investigators introduced the Pearson-Aitken Family Genetic Risk Score (PAFGRS). This sophisticated method directly implements the classic liability threshold model across comprehensive genealogical records. Specifically, the PAFGRS framework incorporates variable family structure, differing degrees of genetic relatedness, age-related censoring, and trait-specific heritability parameters. By converting pedigree data into a continuous liability scale, this framework provides an exceptionally rigorous representation of inherited disease vulnerability. Meanwhile, genome-wide polygenic scores summarize the aggregated effect of thousands of single nucleotide polymorphisms discovered in patient DNA samples. Crucially, each approach approaches disease liability through a fundamentally distinct observational lens. While polygenic metrics directly measure common single nucleotide polymorphisms, family indicators capture broader inherited genetics alongside unmeasured shared environmental influences. Consequently, understanding these structural differences enables researchers to interpret risk estimates with greater biological fidelity.
A recent comprehensive investigation conducted by Pruin and colleagues systematically analyzed these comparative risk metrics within the Netherlands Study of Depression and Anxiety cohort. The research cohort comprised 1,339 adult participants, including 1,086 individuals who met formal diagnostic criteria for lifetime depressive disorders. The investigative team generated multiple familial risk indicators, spanning basic dichotomous metrics, proportional scores, and the advanced PAFGRS liability framework. Concurrently, researchers derived individual polygenic scores utilizing summary statistics from the latest international depression genome-wide association studies. Statistical analyses demonstrated that all family history metrics correlated strongly with one another, showing correlation coefficients ranging from 0.71 to 0.99. In striking contrast, familial indicators exhibited a remarkably modest correlation of only 0.15 with molecular polygenic scores. This pronounced divergent relationship demonstrates that pedigree metrics and molecular arrays capture non-redundant dimensions of depressive vulnerability. Furthermore, predictive modeling revealed a distinct, progressive increase in diagnostic discrimination across the evaluated pedigree methods. The basic proportional score demonstrated modest diagnostic capability, whereas the mathematically advanced PAFGRS algorithm attained significantly higher predictive accuracy. In multivariable models, PAFGRS emerged as an exceptionally potent independent predictor of lifetime diagnosis, confirming the superior predictive value of theory-based genealogical modeling. These critical findings highlight that algorithmic sophistication significantly enhances the clinical value of standard pedigree data.
The pronounced statistical independence observed between molecular polygenic scores and genealogical risk metrics carries profound ramifications for clinical psychiatry. Currently, genome-wide polygenic scores capture only a modest fraction of total depression heritability, leaving substantial genomic liability unexplained. Critical elements such as rare penetrant mutations, structural copy number variants, non-additive epistatic interactions, and epigenetic modifications completely bypass common-variant genotyping arrays. Conversely, a detailed family history of depression inherently captures these missing genetic components alongside shared developmental and socioeconomic environments. Consequently, merging molecular profiling with comprehensive pedigree metrics generates powerful synergistic predictive advantages. In the NESDA cohort, multivariable regression demonstrated that both PAFGRS and polygenic scores remained robustly and independently associated with lifetime depressive disorder. The best-performing family indicator exhibited an adjusted odds ratio exceeding fifteen, while the polygenic risk score contributed a significant independent odds ratio of 1.30. These robust findings decisively prove that molecular genotyping cannot replace thorough generational pedigree assessments in psychiatric evaluation. Instead, both investigative modalities provide mutually reinforcing clinical insights into an individual's total pathophysiological susceptibility. Therefore, integrating refined familial algorithms with emerging molecular tests represents the most comprehensive strategy for future risk assessment. Consequently, psychiatric assessment achieves optimal precision when practitioners systematically evaluate both biological history and genomic profiles simultaneously.
These empirical insights offer immediate, highly practical implications for medical practitioners, particularly within developing nations such as India. In low-resource clinical settings, broad deployment of routine molecular genotyping and polygenic profiling remains cost-prohibitive for the general public. However, conducting a meticulous clinical pedigree interview requires no expensive laboratory infrastructure or proprietary biotechnology. Healthcare providers can dramatically upgrade clinical assessment simply by gathering structured information regarding biological kinship, total sibling count, and parental illness severity. Rather than relying on superficial binary queries, practitioners should document exactly which relatives experienced mood disorders across multiple generations. Furthermore, health technology innovators can seamlessly embed liability threshold calculations, such as PAFGRS formulas, directly into existing hospital electronic health records. Automated clinical algorithms could instantly transform routine family charts into precise, calibrated risk estimates during outpatient triage. This quantitative stratification allows clinicians to identify vulnerable individuals long before severe depressive episodes manifest clinically. Early detection subsequently facilitates proactive lifestyle counseling, targeted psychotherapy, stress reduction interventions, and close outpatient monitoring. Ultimately, refining routine genealogical assessments bridges the gap between complex psychiatric genetics and accessible, cost-effective primary healthcare delivery worldwide. Therefore, adopting refined pedigree indicators provides immediate clinical advantages across diverse real-world healthcare settings.
Standard clinical questions merely document whether any relative suffered from depression, treating all family sizes and kinships identically. In contrast, the Pearson-Aitken Family Genetic Risk Score uses the liability threshold model. It mathematically incorporates pedigree size, specific degrees of biological relatedness, baseline population prevalence, and trait heritability to generate a calibrated continuous genetic risk score.
Polygenic scores reflect only common single nucleotide polymorphisms identified through genome-wide association studies. Conversely, family history captures rare penetrant variants, gene-gene interactions, structural variations, and shared environmental exposures. Consequently, these tools reflect distinct dimensions of depressive vulnerability, yielding a modest correlation of approximately 0.15 despite their mutual clinical value.
Yes, clinicians can immediately apply these principles by gathering detailed genealogical pedigrees rather than relying on binary yes-or-no questions. By systematically recording pedigree size, biological kinship, and illness severity, physicians markedly enhance clinical risk stratification. This structured approach provides powerful diagnostic and prognostic insights even when molecular profiling tools remain completely unavailable.
Disclaimer: This content is for informational and educational purposes only. It is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study from the Netherlands Study of Depression and Anxiety demonstrates that advanced family history metrics, such as PAFGRS, outperform simple indicators and act independently of polygenic scores to predict depressive disorder, highlighting the strong complementary value of pedigree and genomic data.
Today
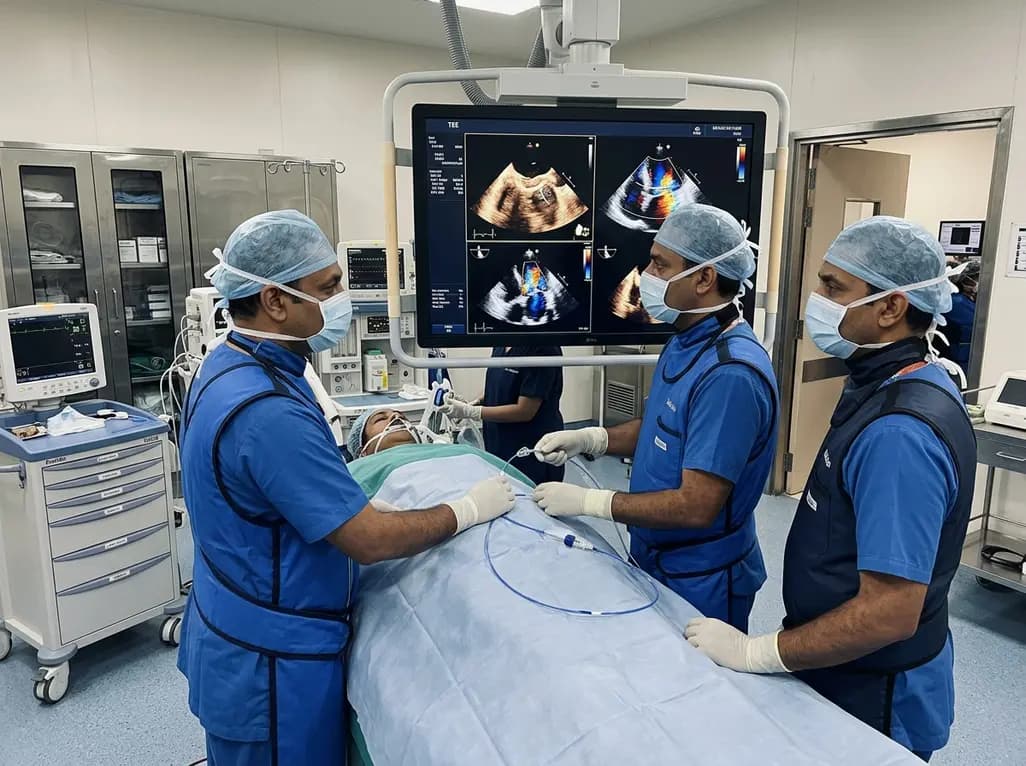
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today
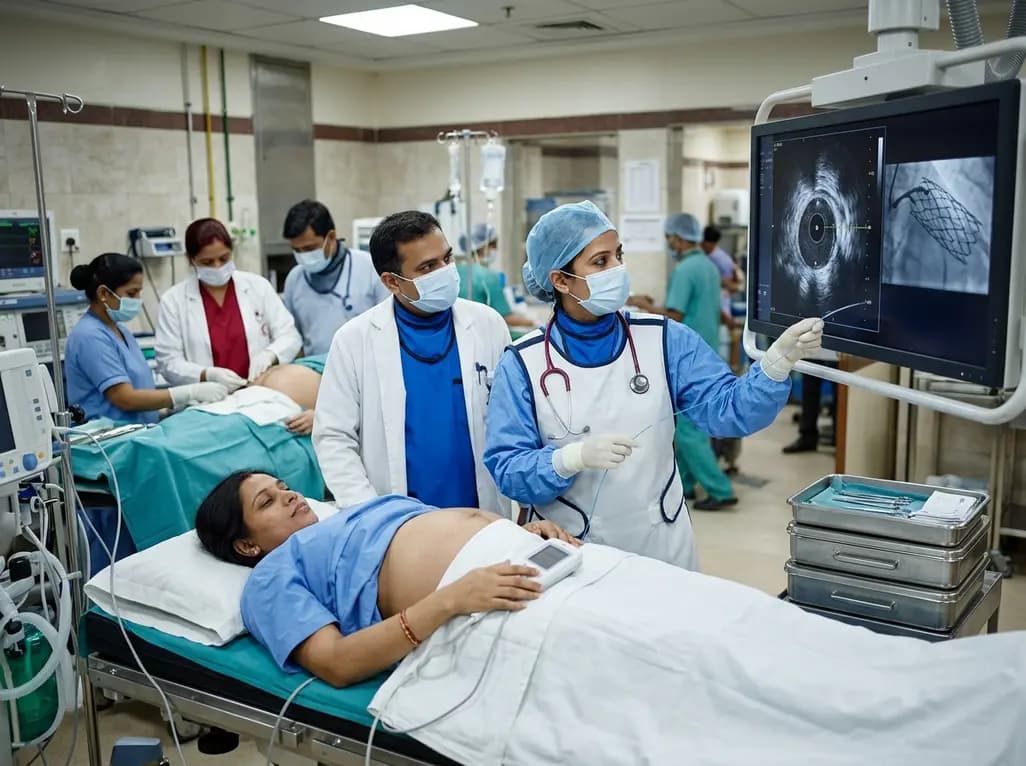
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday
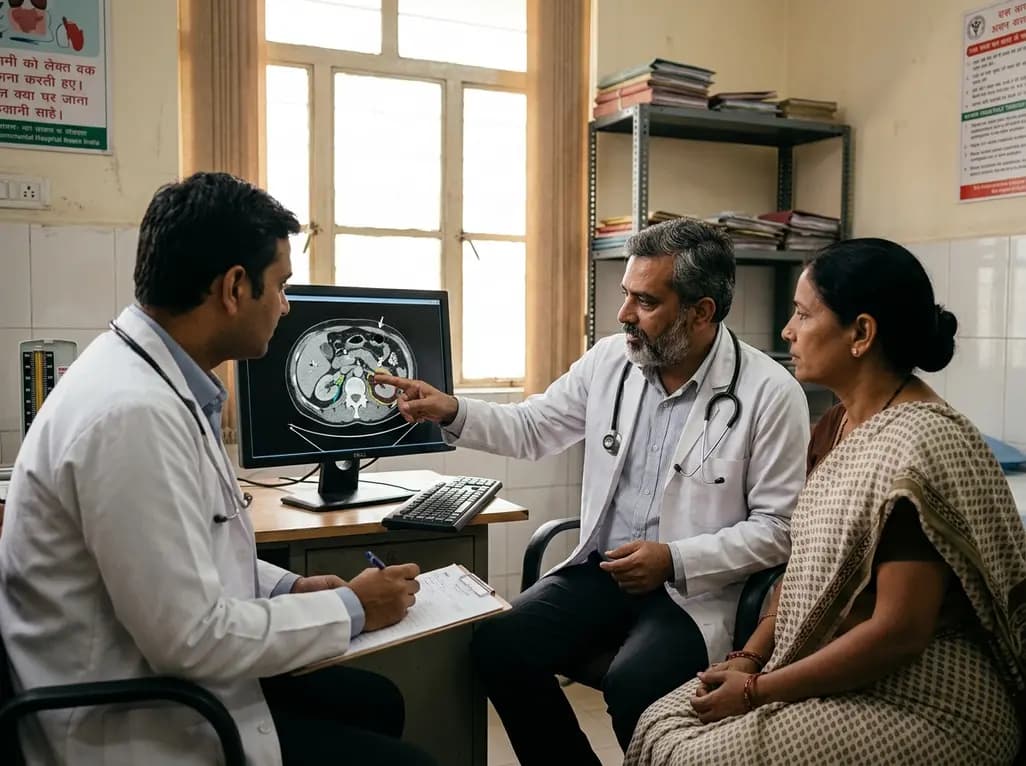
New ADIPO-CKD study findings demonstrate that both GLP-1 receptor agonists and SGLT2 inhibitors significantly reduce perirenal adipose tissue thickness in chronic kidney disease patients, with GLP-1 therapy achieving greater reductions, highlighting a novel mechanism for cardiorenal metabolic protection.
Today
