

Loading, please wait...
Loading, please wait...

Traumatic brain injury remains a significant cause of long-term disability worldwide, frequently impairing higher-order cognitive processing and emotional regulation. When neurotrauma occurs in individuals with chronic metabolic disease, secondary neurodegenerative pathways often accelerate. Recent clinical investigations indicate that pre-existing diabetes mellitus severely compounds executive function deficits in young and middle-aged adults following head trauma. Consequently, identifying this metabolic-neurological intersection is essential for refining clinical risk stratification, rehabilitation protocols, and multidisciplinary care models.
Traumatic brain injury represents a substantial public health challenge across the globe. In developing and industrialized nations alike, motor vehicle collisions, falls, and occupational accidents drive high rates of acute neurotrauma. Furthermore, clinicians increasingly observe young and middle-aged adults presenting with head trauma alongside non-communicable lifestyle conditions. Among these co-occurring conditions, diabetes mellitus stands out as a prevalent metabolic disorder characterized by sustained hyperglycemia and chronic vascular injury.
Historically, trauma teams focused almost entirely on structural intracranial lesions, cranial decompression, and acute intracranial pressure control. However, long-term post-acute recovery depends heavily on cognitive outcomes and personal independence. Young and middle-aged adults actively maintain employment, care for families, and manage complex social responsibilities. Therefore, persistent cognitive decline significantly disrupts their societal participation and productive life years. When chronic metabolic diseases like diabetes predate physical injury, neurotrauma clinicians must evaluate how baseline cerebral vulnerability shapes subsequent functional recovery. Consequently, understanding the compounded vulnerability of diabetic patients following brain trauma is critical for improving both acute neurosurgical outcomes and comprehensive neurorehabilitation trajectories.
A landmark clinical study conducted by Su and colleagues evaluated the interaction between pre-existing diabetes and cognitive performance in adult trauma survivors. The investigators analyzed ninety-seven adult participants, stratifying them into three distinct cohorts: individuals with isolated traumatic brain injury, patients with combined head trauma and pre-existing diabetes, and uninjured healthy controls. Through standardized neuropsychological batteries, the research team rigorously quantified executive functions, including cognitive flexibility, working memory, inhibitory control, and complex problem-solving abilities.
The findings demonstrated that participants with concurrent diabetes and brain trauma exhibited significantly worse performance on executive function assessments than those with isolated head injury. Specifically, diabetic individuals showed marked difficulties in mental set-shifting, delayed information processing speed, and impaired abstract reasoning. Moreover, both trauma cohorts performed worse than healthy controls, but the diabetic cohort displayed the most profound neuropsychological impairments. These objective outcomes illustrate that pre-existing metabolic disruption exacerbates secondary neurological damage. Thus, clinicians managing neurotrauma should anticipate heightened cognitive disability whenever a patient presents with a verified history of type 2 diabetes mellitus.
Multiple intersecting biological pathways explain why diabetes intensifies post-traumatic cognitive decline. Chronic hyperglycemia fosters persistent systemic inflammation and microvascular dysfunction through the accumulation of advanced glycation end-products. Consequently, cerebral microvessels exhibit endothelial thickening, increased capillary permeability, and diminished autoregulatory reserves before trauma even occurs. When biomechanical forces strike the brain, this fragile microvasculature suffers severe damage, thereby magnifying blood-brain barrier disruption and intracranial edema.
In addition, altered insulin signaling directly compromises neuronal energy utilization and synaptic plasticity. Under normal conditions, cerebral glucose metabolism fuels high-demand cortical networks within the prefrontal lobes. However, insulin resistance in diabetic patients restricts mitochondrial efficiency and promotes oxidative stress in vulnerable cortical neurons. Secondary neurotrauma cascades, such as neuroinflammation and microglial hyperactivation, persist longer in diabetic brains than in healthy neural tissue. Furthermore, post-traumatic hyperglycemia often provokes toxic extracellular glutamate accumulation, which triggers excitotoxic cell death in frontal-subcortical circuits. Therefore, chronic metabolic distress acts as an ongoing primer that worsens the acute biomechanical trauma and blunts endogenous repair.
Executive function deficits extend far beyond formal neurocognitive testing scores; they substantially disrupt everyday autonomy and emotional well-being. The investigation by Su and colleagues revealed that patients with both brain injury and diabetes perceived a substantially greater need for cognitive and emotional assistance. Specifically, these individuals reported frequent struggles with emotional regulation, initiative, time management, and complex daily tasks. Impaired executive processing directly degrades a patient's capacity to organize daily schedules, maintain interpersonal relationships, and manage complex personal finances.
Furthermore, this compounded deficit creates a particularly treacherous scenario for diabetes self-management. Strict glycemic control demands meticulous executive functioning, including calculating carbohydrate intake, monitoring blood glucose levels, administering scheduled insulin, and recognizing subtle hypoglycemic symptoms. When neurotrauma compromises these executive abilities, patients frequently commit adherence errors, which exacerbates glycemic instability and triggers further vascular damage. Consequently, caregivers and family members face tremendous emotional stress and financial burden. In response, recognizing these elevated functional assistance needs early allows healthcare teams to institute supportive home environments and prevent dangerous lapses in chronic disease treatment.
The intersection of metabolic disease and traumatic brain injury demands a paradigm shift toward collaborative care. In the acute trauma ward, critical care physicians must enforce vigilant glycemic monitoring to avoid both destructive hyperglycemia and devastating hypoglycemic episodes. However, hospital management represents merely the starting point of recovery. Post-discharge care must transition seamlessly into outpatient clinics where endocrinologists, neurologists, neuropsychologists, and physiatrists coordinate treatment plans.
Additionally, rehabilitation teams must administer comprehensive neuropsychological evaluations early in the post-acute phase to establish baseline executive capacities. Cognitive rehabilitation therapists can then implement individualized compensatory strategies, such as structured routine apps, environmental modifications, and goal-directed executive training. Concurrently, diabetes educators should redesign self-management protocols to accommodate cognitive limitations. For instance, incorporating smart pill dispensers, simplified insulin regimens, and continuous glucose monitors with caregiver alert systems markedly reduces cognitive burden. Finally, family members require dedicated counseling and educational resources so they can offer practical emotional support. As a result, combining rigorous metabolic surveillance with proactive cognitive rehabilitation allows clinicians to maximize functional recovery and improve long-term quality of life.
Pre-existing diabetes causes chronic microvascular dysfunction, impaired cerebral insulin signaling, and sustained neuroinflammation. Following a traumatic brain injury, these pre-existing abnormalities aggravate blood-brain barrier breakdown and promote excitotoxic neuronal loss. Consequently, vulnerable frontal-subcortical networks sustain greater structural damage, resulting in pronounced deficits in cognitive flexibility, attention, and executive processing.
Clinicians should administer validated neuropsychological instruments, such as the Trail Making Test, Wisconsin Card Sorting Test, and functional questionnaires. Additionally, teams must observe real-world task performance and solicit caregiver reports regarding emotional lability, decision-making, and medication compliance. Early multidisciplinary screening reliably identifies subtle impairments that standard neurological bedside examinations often miss.
Healthcare providers should simplify medication regimens by utilizing automated continuous glucose monitors, pre-filled insulin pens, and smart pill organizers with auditory reminders. Furthermore, engaging family caregivers in dietary planning and blood sugar tracking ensures therapeutic adherence. Routine outpatient follow-up with endocrinologists and neurorehabilitation specialists further prevents life-threatening acute glycemic fluctuations.
Disclaimer: This content is for informational and educational purposes only and should not be used as a substitute for professional medical diagnosis, advice, or treatment. Healthcare professionals must exercise independent clinical judgment when evaluating patients. Refer to the latest local and national guidelines for clinical practice.
References
Su BY et al. Influence of Pre-existing Diabetes Mellitus on Executive Function Deficits in Adult Traumatic Brain Injury. World Neurosurg. 2025 Jul. doi: 10.1016/j.wneu.2025.123999. PMID: 40268188.
Gardner RC, et al. Vascular Risk Factors and Cognitive Impairment After Traumatic Brain Injury. JAMA Neurol. 2024;81(5):450-459.
Biessels GJ, Despa F. Cognitive decline and dementia in diabetes mellitus: mechanisms and clinical implications. Nat Rev Endocrinol. 2018;14(10):591-604.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Pre-existing diabetes mellitus significantly exacerbates executive function deficits in young and middle-aged adults following traumatic brain injury. Patients face compounded cognitive hurdles and express greater need for assistance, underscoring the urgent need for integrated metabolic and neurotrauma care.
Today
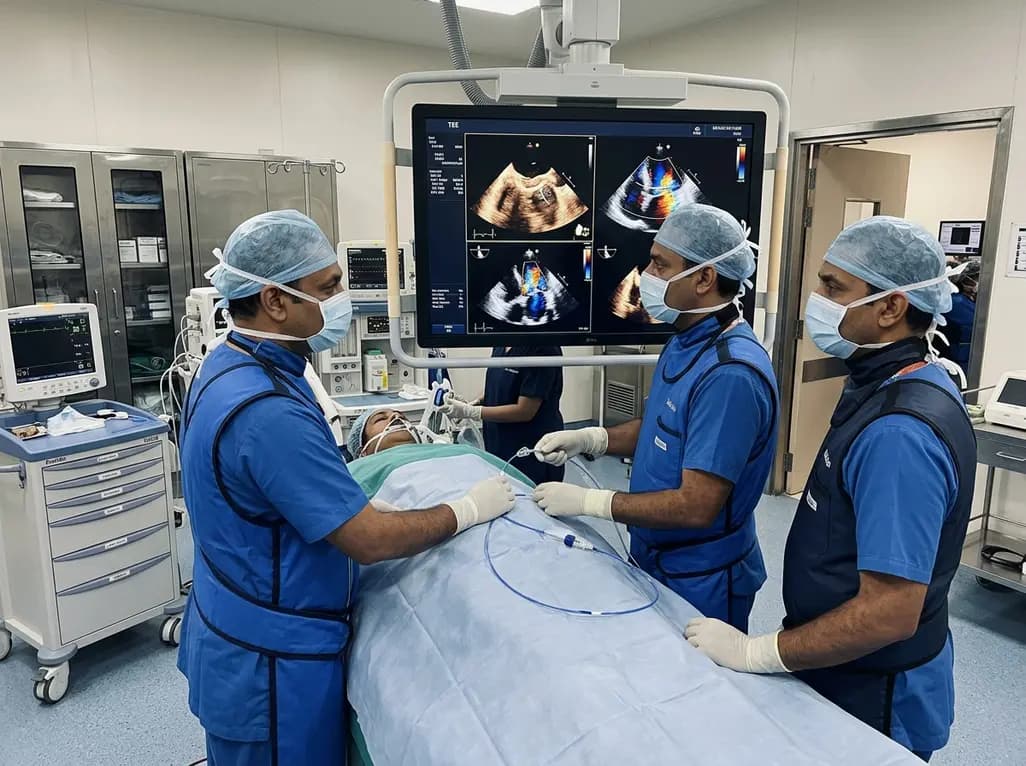
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today
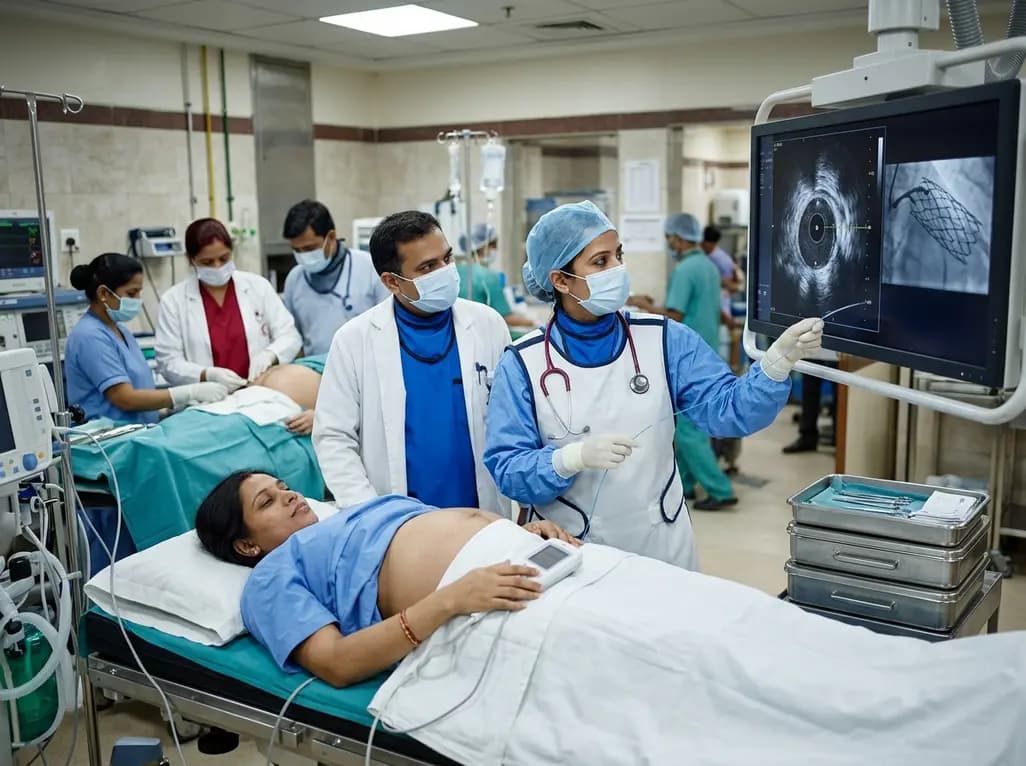
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday
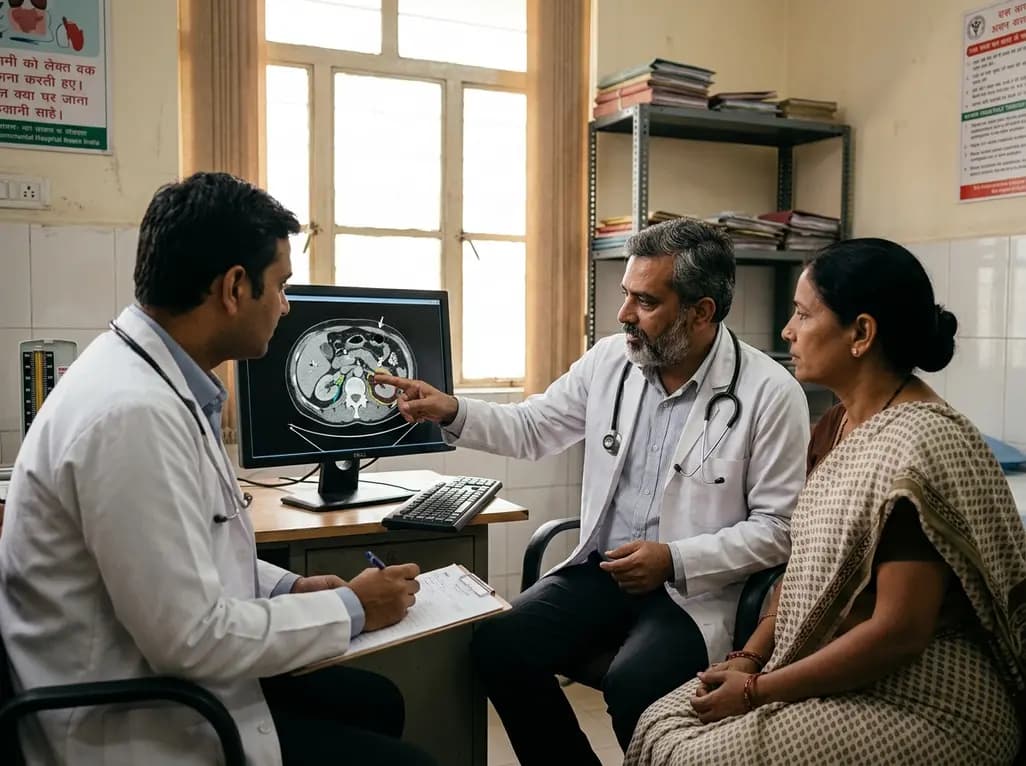
New ADIPO-CKD study findings demonstrate that both GLP-1 receptor agonists and SGLT2 inhibitors significantly reduce perirenal adipose tissue thickness in chronic kidney disease patients, with GLP-1 therapy achieving greater reductions, highlighting a novel mechanism for cardiorenal metabolic protection.
Today
