

Loading, please wait...
Loading, please wait...

Renal insufficiency represents a pervasive challenge following orthotopic cardiac transplantation. Consequently, clinicians actively seek innovative therapeutic options to preserve kidney function and prolong survival. The landmark DAPARHT clinical trial evaluated the efficacy of dapagliflozin in heart transplant recipients experiencing ongoing nephron decline. Progressive renal injury in this population typically stems from calcineurin inhibitor nephrotoxicity, pre-existing comorbidities, and microvascular stiffness. Although calcineurin inhibitors prevent allograft rejection, they induce severe renal vasoconstriction and arteriolar hyalinosis over time.
Sodium-glucose cotransporter-2 inhibitors confer robust cardiorenal protection in native diabetic and non-diabetic kidney diseases. However, prospective randomized evidence evaluating these agents in solid organ transplant recipients remained sparse until recently. Clinicians frequently questioned whether immunosuppressed patients would tolerate cotransporter inhibition without experiencing severe infections. Therefore, the DAPARHT trial provides critical, high-quality evidence regarding the role of gliflozins in this vulnerable cohort. Ultimately, these findings offer clear therapeutic direction for cardiologists and nephrologists managing chronic post-transplant care.
The DAPARHT study enrolled patients across six specialized cardiothoracic transplant centers throughout Northern Europe. Investigators designed the study as a multicenter, double-blind, randomized, placebo-controlled trial. Furthermore, eligible participants included adult heart transplant recipients who survived at least one full year after transplantation. Candidates required an estimated glomerular filtration rate of twenty-five mL/min/1.73 m² or higher at initial screening. Between June 2022 and September 2025, researchers randomized 430 participants to oral dapagliflozin 10 mg daily or placebo.
Specifically, the full analysis set included 424 patients with at least one post-baseline filtration measurement. The cohort showed a mean age of 53 years, and women comprised 29 percent of participants. Notably, the median duration from transplantation stood at seven years, reflecting an established long-term survivor population. Participants presented with a mean baseline estimated glomerular filtration rate of 67 mL/min/1.73 m². In addition, all patients maintained their standard immunosuppressive regimens throughout the twelve-month treatment course. This rigorous methodology allowed investigators to evaluate real-world transplant pharmacology accurately.
The primary trial endpoint focused on the chronic slope of estimated glomerular filtration rate. Investigators evaluated filtration trajectories from two weeks post-randomization through the completion of the twelve-month treatment period. This landmark analysis deliberately excluded the initial two-week period to neutralize expected reversible hemodynamic changes. Dapagliflozin significantly improved the chronic filtration slope compared with placebo over the twelve-month duration. Specifically, patients allocated to dapagliflozin achieved an estimated filtration rate increase of 2.0 mL/min/1.73 m².
Conversely, participants in the placebo group displayed an estimated filtration rate change of only 0.3 mL/min/1.73 m². This trajectory produced a statistically significant between-group difference of 1.7 mL/min/1.73 m², yielding a p-value of 0.03. Consequently, the trial confirmed that sodium-glucose cotransporter inhibition successfully decelerates functional nephron loss in heart transplant recipients. Furthermore, the sustained benefit indicates that hemodynamic modulation protects renal microvasculature from relentless calcineurin inhibitor-induced injury. These compelling data illustrate genuine nephroprotection rather than a temporary numerical fluctuation.
Safety remains a paramount clinical consideration when prescribing new therapies to transplant recipients receiving immunosuppression. Because transplant recipients maintain vulnerable immune defenses, clinicians often anticipate potential complications such as genitourinary infections. Fortunately, the DAPARHT trial documented no unexpected safety signals throughout the entire twelve-month observation period. Overall adverse event rates remained remarkably similar between the dapagliflozin cohort and the placebo cohort. In particular, researchers observed no significant difference in the incidence of serious infectious episodes.
Additionally, patients experienced no excess occurrences of urinary tract infections or mycotic genital complications during active therapy. Routine monitoring confirmed stable calcineurin inhibitor levels, proving that dapagliflozin does not disrupt immunosuppressive drug metabolism. The study recorded no elevated risks of acute allograft rejection, symptomatic hypotension, or volume depletion. Similarly, rare metabolic concerns such as euglycemic ketoacidosis did not emerge during the trial. Therefore, these safety data offer strong reassurance to clinicians contemplating early SGLT2 inhibitor therapy for heart transplant recipients.
Integrating dapagliflozin into daily post-transplant clinical protocols represents an evidence-based opportunity to prevent end-stage kidney failure. Practicing clinicians should identify heart transplant recipients who remain clinically stable at least one year following surgery. Before starting therapy, clinicians should obtain baseline creatinine, electrolyte levels, and estimated glomerular filtration measurements. When starting treatment, physicians must anticipate a modest, transient drop in filtration rate during the initial two weeks. Because this early dip reflects therapeutic reductions in glomerular hypertension, clinicians should avoid prematurely stopping the medication.
Moreover, multidisciplinary collaboration between transplant cardiologists, nephrologists, and primary physicians optimizes therapeutic monitoring and patient compliance. Clinicians must counsel patients regarding adequate fluid intake, particularly in warm environments or during transient gastrointestinal illnesses. In addition, periodic surveillance of calcineurin inhibitor trough concentrations ensures continued patient safety, despite minimal pharmacological interaction. Although conventional guidelines historically emphasized immunosuppressive adjustments alone, cotransporter inhibition provides direct nephron protection. Consequently, routine implementation of dapagliflozin can substantially preserve kidney function and enhance overall post-transplant survivorship.
Dapagliflozin inhibits sodium-glucose cotransporters in the proximal renal tubules, thereby promoting urinary glucose and sodium excretion. This mechanism increases sodium delivery to the macula densa, which activates tubuloglomerular feedback and modulates arteriolar tone. Consequently, the drug reduces intraglomerular hypertension, mechanical sheer stress, and long-term hyperfiltration injury. In heart transplant recipients, this physiological response directly counteracts chronic vasoconstriction induced by calcineurin inhibitors, ultimately preserving renal structural integrity and attenuating progressive filtration decline.
The DAPARHT trial demonstrated no significant increase in serious infectious complications among patients receiving dapagliflozin compared with placebo. Although clinicians often worry about urinary tract infections or genital mycotic infections in immunosuppressed transplant recipients, overall adverse event rates remained thoroughly balanced between study arms. Participants tolerated daily therapy remarkably well without experiencing unexpected infectious signals. Therefore, clinicians can safely prescribe dapagliflozin in stable heart transplant recipients while maintaining standard hygiene education and routine surveillance protocols.
In accordance with the DAPARHT trial inclusion criteria, clinicians should consider initiating dapagliflozin in patients who are at least one year post-transplantation. This timing ensures that surgical wounds have healed and baseline maintenance immunosuppression has stabilized. Furthermore, candidates must maintain an estimated glomerular filtration rate of at least twenty-five mL/min/1.73 m² without acute rejection episodes. Clinicians should closely evaluate volume status and concurrent diuretic requirements before initiation to prevent potential intravascular volume depletion.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals should exercise independent clinical judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The randomized DAPARHT trial demonstrates that dapagliflozin 10 mg once daily significantly improves the chronic eGFR slope compared to placebo in heart transplant recipients, offering safe and effective renal protection against calcineurin inhibitor-induced nephrotoxicity.
Today
A 21-year-old postpartum female presenting with right heart failure was initially suspected of peripartum cardiomyopathy, but comprehensive imaging and serology confirmed MCTD-associated pulmonary hypertension. Early diuretic and immunosuppressive therapy led to successful clinical stabilization.
Today
A comprehensive review of the 2025 European Resuscitation Council guidelines on resuscitation education, highlighting blended learning, deliberate simulation, non-technical team skills, and practical implementation across diverse resource environments.
Today
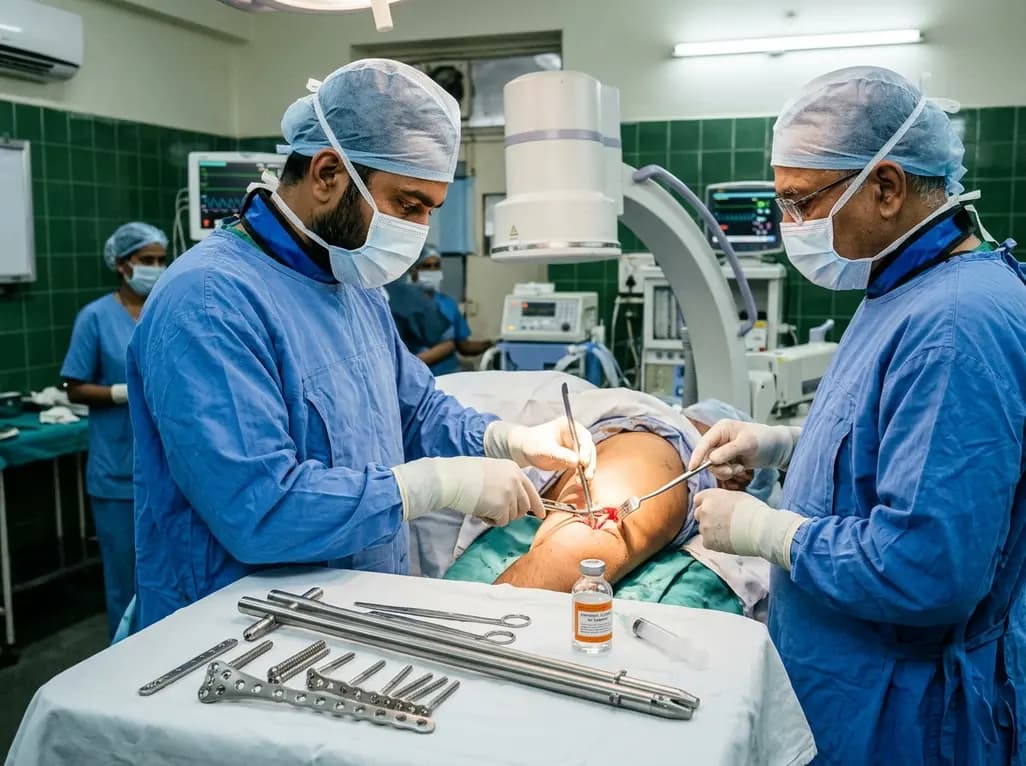
Septic humeral shaft nonunion in patients with obesity presents extreme mechanical and biological challenges. Discover how hybrid nail-plate osteosynthesis paired with targeted antibiotic therapy provides rigid stability, eradicates infection, and restores maximal upper extremity function.
Today

A case report details how reusing single-use insulin cartridges caused device failure and diabetic ketoacidosis in a type 1 diabetes patient using an advanced hybrid closed-loop system. The report highlights technological blindspots, mechanical degradation, and safety protocols during supply shortages.
Today
