

Loading, please wait...
Loading, please wait...

Inborn errors of immunity present diagnostic dilemmas for clinicians worldwide. Specifically, CTLA-4 haploinsufficiency causes an autosomal dominant immune dysregulation syndrome. Affected patients develop recurrent infections, progressive hypogammaglobulinemia, and severe autoimmune manifestations. Heterozygous mutations in the cytotoxic T-lymphocyte associated protein 4 gene impair immune tolerance. However, clinical penetrance remains incomplete, and symptoms often exhibit variable onset. Recent groundbreaking research using a patient-derived Y139C knock-in mouse model provides crucial mechanistic insights into why overt clinical autoimmunity often delays its presentation.
The human immune system relies on regulatory checkpoints to maintain peripheral tolerance. Cytotoxic T-lymphocyte associated protein 4 acts as a critical negative regulator of adaptive immunity. Consequently, loss of a single functional allele impairs peripheral T cell suppression. To elucidate the disease course, immunologists introduced the human pathogenic Y139C missense mutation into mice. Young heterozygous animals developed pronounced lymphadenopathy and splenomegaly. Furthermore, flow cytometric analysis confirmed that CD4 and CD8 effector T cells displayed persistent activation markers. However, despite marked cellular activation, these juvenile mice showed no signs of active tissue destruction or histological autoaggression. This observation mirrors the enigmatic asymptomatic period often observed in young human mutation carriers. In addition, the mice resisted experimentally induced acute inflammation. Thus, cellular hyperactivation and overt autoimmune disease clearly represent distinct immunological phases governed by age-dependent regulatory thresholds.
CTLA-4 controls immune activation through a specialized cell-extrinsic mechanism known as trans-endocytosis. Regulatory T cells utilize cell-surface CTLA-4 to physically capture and internalize CD80 and CD86 costimulatory ligands from antigen-presenting cells. Therefore, conventional T cells cannot access the critical CD28 costimulation required for expansion. In this study, co-culture functional assays demonstrated that the Y139C variant severely disrupted ligand trans-endocytosis. Consequently, costimulatory molecules persisted on dendritic cells and B cells. Surprisingly, regulatory T cells maintained substantial suppressive capacity despite this severe functional impairment. Transcriptomic profiling revealed that systemic cellular stress triggered CTLA-4-independent compensatory pathways within the regulatory T cell compartment. Specifically, alternative inhibitory mediators, including interleukin-10 and transforming growth factor-beta, preserved basal suppression. Consequently, these robust backup adaptations buffered the host against immediate autoimmune destruction during early life.
Although compensatory adaptations protect juvenile animals, this physiological equilibrium eventually falters. As heterozygous mice aged, they experienced progressive immune breakdown. Furthermore, older animals developed spontaneous autoimmune pathologies characterized by severe multi-organ lymphocytic infiltration. Spleen and peripheral lymph node architecture underwent significant disorganization. Histopathological examination demonstrated substantial leukocyte invasion into non-lymphoid tissues, including the lungs, liver, and gastrointestinal mucosa. In contrast, age-matched wild-type littermates maintained intact organ architecture. Cellular analyses revealed that regulatory T cells gradually lost their compensatory capacity over time. Continuous antigen exposure and chronic low-grade inflammation ultimately exhausted secondary inhibitory pathways. Consequently, unconstrained effector T cells targeted self-antigens, producing destructive inflammatory lesions. This progressive decline directly explains why human patients often present with late-onset cytopenias, enteropathy, and interstitial lung disease.
These preclinical findings carry substantial implications for Indian clinical practice. In India, physicians frequently encounter adolescents and adults presenting with unexplained immune cytopenias, refractory autoimmune enteropathy, or chronic splenomegaly. Because clinical features overlap heavily with common variable immunodeficiency and sarcoidosis, diagnosis faces frequent delays. Furthermore, infectious endemic challenges, including tuberculosis, often complicate the evaluation of systemic lymphoproliferation. Incorporating next-generation sequencing into clinical workflows enables early detection of monogenic inborn errors of immunity. Clinicians should maintain high suspicion when patients present with familial autoimmune disease or cytopenias unresponsive to standard steroids. Moreover, distinguishing CTLA-4 defects from primary antibody deficiencies prevents inappropriate immunosuppressive therapies. Timely genetic confirmation directs appropriate supportive interventions, family counseling, and disease surveillance before irreversible end-organ damage occurs.
Understanding the molecular defects of trans-endocytosis provides targeted opportunities for intervention. Standard broad-spectrum immunosuppression carries substantial infectious risks, particularly in hospital settings managing opportunistic pathogens. In contrast, precision biologic therapy directly addresses the underlying costimulatory excess. Abatacept, a soluble CTLA-4-immunoglobulin fusion protein, directly mimics endogenous CTLA-4 function. By binding CD80 and CD86 ligands on antigen-presenting cells, abatacept restores extrinsic costimulatory blockade. Clinical trials have confirmed that abatacept effectively controls autoimmune cytopenias and enteropathy in affected patients. Furthermore, identifying alternative compensatory pathways opens avenues for novel therapeutic synergy. Monitoring regulatory T cell fitness and costimulatory expression profiles may predict impending clinical relapse. Ultimately, targeting the CTLA-4 pathway restores immunological balance while minimizing the toxicities associated with conventional cytotoxic regimens.
The primary mechanism involves defective trans-endocytosis of CD80 and CD86 costimulatory ligands from antigen-presenting cells. Because one CTLA-4 allele carries a loss-of-function mutation, regulatory T cells express insufficient functional protein. Consequently, antigen-presenting cells retain high costimulatory molecule density. This excess costimulation allows autoreactive effector T cells to escape regulatory checkpoints, leading to chronic lymphoproliferation and eventual autoimmune tissue destruction.
Patients experience delayed disease onset because regulatory T cells recruit robust CTLA-4-independent compensatory mechanisms during early life. These alternative pathways produce immunosuppressive cytokines that temporarily restrain effector responses. However, cumulative immune activation, chronic microbial exposure, and physiological aging eventually exhaust these compensatory reserves. Once cellular compensation fails, spontaneous autoimmunity emerges against vulnerable tissues such as the bone marrow, lungs, and gut.
Clinicians manage this condition by combining targeted biological therapies with individualized supportive care. The CTLA-4-Ig fusion protein abatacept serves as the primary targeted agent by binding excess CD80 and CD86 ligands. In addition, patients benefit from immunoglobulin replacement therapy, antimicrobial prophylaxis, and organ-specific surveillance. Hematopoietic stem cell transplantation remains a definitive curative consideration for patients presenting with refractory or life-threatening multi-organ disease.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





New research shows that CTLA-4 haploinsufficiency carrying a patient-derived Y139C mutation causes delayed autoimmune disease in mice. Despite early trans-endocytosis failure, compensatory regulatory T cell pathways preserve immune homeostasis until aging precipitates overt multi-organ autoimmunity.
Today
A bibliometric study maps global research on intimate partner violence during COVID-19, revealing a 17.08% publication growth rate and motor themes of mental health and social support. Clinicians require trauma-informed screening and systemic crisis preparedness to protect vulnerable women during ongoing crises.
Today
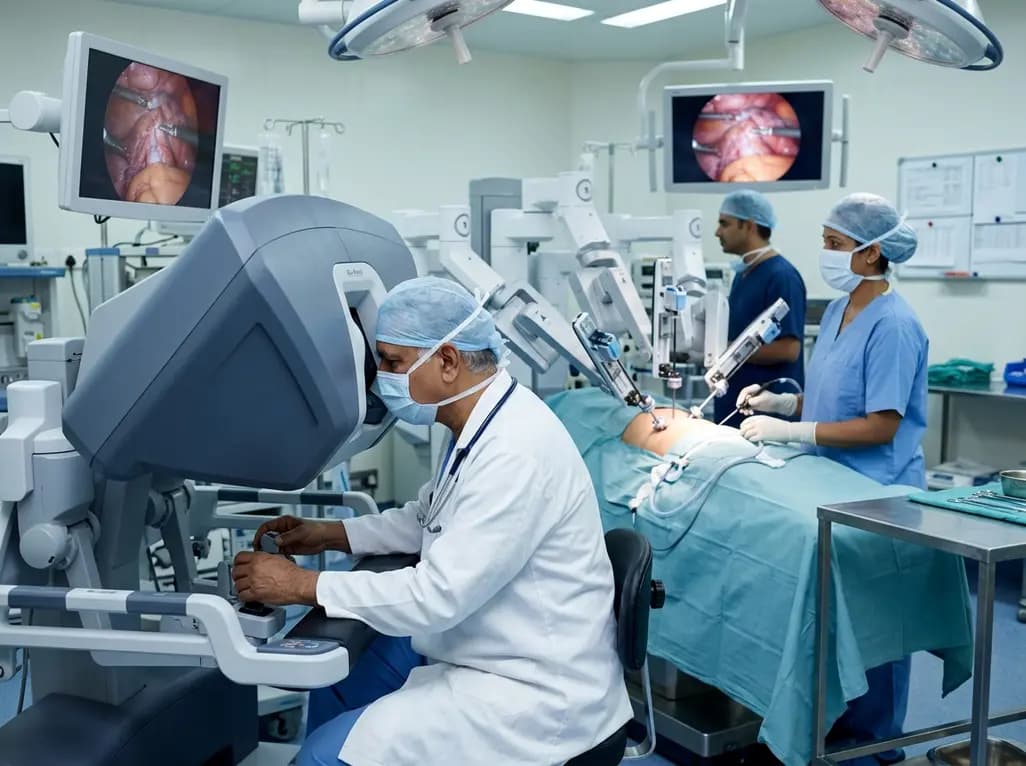
Surgical robotics is redefining modern operating theaters by replacing extensive open incisions with micro-dexterity and stereoscopic 3D vision. Multi-specialty surgeons highlight how robotic platforms mitigate tissue trauma, enhance functional organ preservation, and shorten postoperative hospital recovery.
Today
Piezoelectric amino acids and peptides convert mechanical stress into bioelectric cues. By mimicking endogenous electrical fields, these biodegradable biomaterials advance tissue regeneration, biosensing, antimicrobial therapy, and targeted oncology without leaving toxic residues.
Today

A network meta-analysis of 10 RCTs comprising 37,923 patients reveals that SGLT2 inhibitors offer the broadest cardiorenal protection in diabetic kidney disease. Dapagliflozin reduced kidney outcomes more than semaglutide, while finerenone increased hyperkalaemia and treatment discontinuation rates.
Today
