

Loading, please wait...
Loading, please wait...
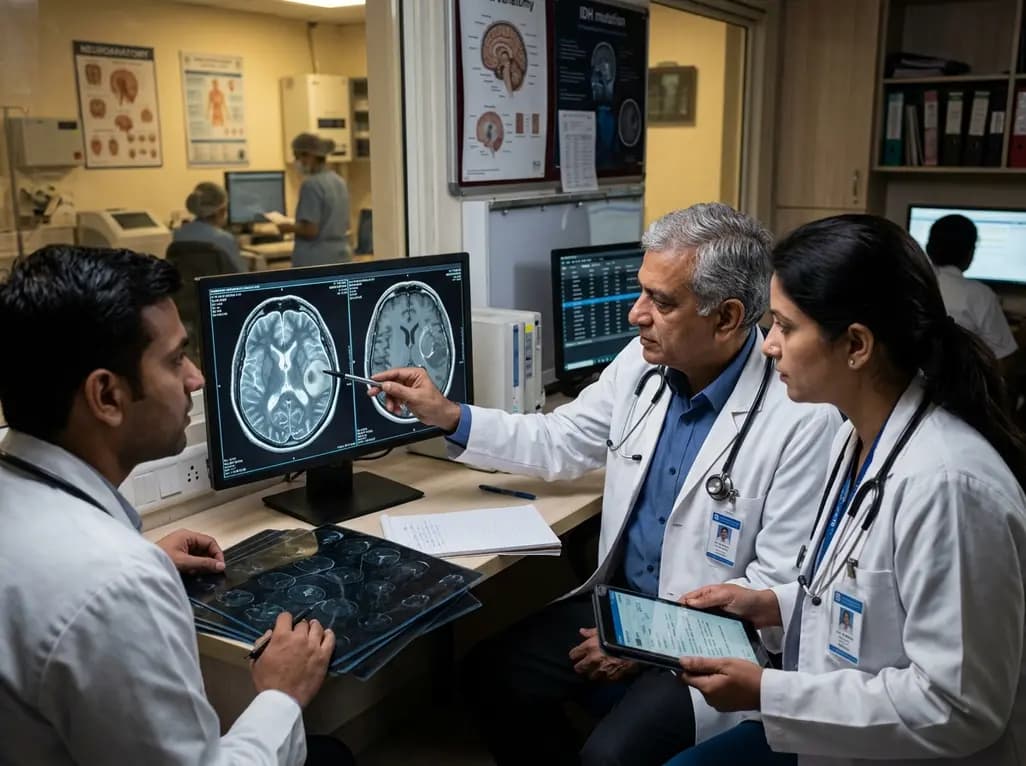
Accurate preoperative diagnosis plays an essential role in guiding neuro-oncology treatment decisions. Historically, clinicians required invasive tissue biopsy to determine critical molecular alterations. However, modern magnetic resonance imaging provides powerful noninvasive radiogenomic tools. A pivotal advancement in this field is the CONTIN sign in glioma evaluation. This marker specifically identifies cortical nonenhancing tumor infiltration on standard diagnostic sequences. Consequently, clinicians can predict isocitrate dehydrogenase mutation status before undertaking surgical resection. Therefore, this radiological feature refines operative planning, risk counseling, and therapeutic pathways. Overall, noninvasive molecular profiling substantially enhances modern neurosurgical care.
Diffuse gliomas represent a biologically heterogeneous group of primary central nervous system neoplasms. According to current World Health Organization guidelines, molecular markers define glioma classification. In particular, mutations in the isocitrate dehydrogenase enzyme alter tumor behavior and patient prognosis. Patients harboring these mutations experience considerably longer survival than wild-type cases. Furthermore, mutated tumors display distinct metabolic pathways that respond favorably to aggressive cytoreductive surgery.
Conversely, wild-type glioblastomas exhibit aggressive invasion, rapid clinical deterioration, and treatment resistance. Therefore, establishing genetic status prior to surgery provides critical clinical value. Traditional neuropathological examination requires formal resection or needle biopsy. However, invasive biopsies carry inherent surgical risks, including hemorrhage and neurological deficits. Moreover, tissue sampling cannot always capture tumor heterogeneity. Consequently, noninvasive radiogenomic markers address a crucial diagnostic need. By anticipating molecular subtypes preoperatively, surgical teams can optimize resection margins safely. Hence, molecular imaging biomarkers represent an indispensable component of neuro-oncology.
The cortical nonenhancing tumor infiltration sign, abbreviated as CONTIN, represents an intuitive radiogenomic feature. Neuroradiologists identify this pattern by assessing high-resolution T2-weighted and FLAIR sequences alongside post-contrast T1-weighted images. Specifically, the sign denotes infiltrative neoplastic expansion into the cerebral cortex without contrast enhancement. This subtle architectural feature mirrors the natural growth of lower-grade or secondary infiltrating glioma cells.
Importantly, clinicians demonstrate remarkable consistency when interpreting this specific radiological sign. Independent reviewers achieved almost perfect interrater agreement with a Cohen kappa coefficient of 0.812. This impressive reproducibility ensures reliable performance across hospital reading rooms. Furthermore, the sign shows high prevalence among isocitrate dehydrogenase-mutant tumors. In retrospective cohort data, researchers detected the sign in over 90% of mutated cases. In contrast, wild-type glioblastomas cause abrupt cortical destruction and intense contrast enhancement without nonenhancing cortical margins. Therefore, identifying nonenhancing cortical expansion offers a reliable sign of favorable tumor biology.
For several years, clinicians relied on the T2-FLAIR mismatch sign to identify mutated astrocytomas noninvasively. When present, that classic sign provides near-perfect diagnostic specificity. However, its real-world application suffers from notably poor sensitivity. In addition, the mismatch sign rarely appears in tumors with macroscopic contrast enhancement. Because high-grade transformation induces neoangiogenesis and contrast enhancement, clinicians cannot use mismatch criteria for advanced tumors.
Herein lies the substantial advantage of the CONTIN sign. In contrast-enhancing gliomas, this imaging feature dramatically improves diagnostic sensitivity. Specifically, clinical studies revealed that sensitivity increased from roughly 15% with mismatch criteria to over 92% with cortical infiltration assessment. Moreover, external validation cohorts confirmed this increase, demonstrating a sensitivity rise from 23.3% to 81.4%. Notably, this surge in sensitivity does not compromise diagnostic specificity, which remains above 82%. Furthermore, the negative predictive value consistently exceeds 94%. Consequently, radiologists can rule out wild-type disease with exceptional confidence. Thus, this biomarker addresses a major clinical gap in neuro-oncology.
Rigorous clinical validation is mandatory before clinicians adopt any novel imaging biomarker into routine practice. To evaluate diagnostic reproducibility, investigators examined multi-institutional cohorts across international institutions. The discovery phase analyzed 526 patients with diffuse gliomas at Beijing Tiantan Hospital. Subsequently, researchers tested the diagnostic framework against 501 patients from the University of California San Francisco repository.
Critically, the biomarker maintained consistent diagnostic performance across both medical centers. In the validation dataset, the overall prevalence reached 85.4% among mutated neoplasms. Additionally, the feature appeared in 81.4% of enhancing lesions and 88.3% of nonenhancing tumors. These findings confirm that diverse MRI scanner manufacturers and patient demographics do not diminish diagnostic accuracy. Furthermore, investigators integrated this sign with patient age and enhancement patterns to create a comprehensive diagnostic protocol. Younger patients presenting with cortical nonenhancing infiltration demonstrated an overwhelming probability of harboring mutations. Therefore, this multivariable approach provides clinicians with an exceptionally robust, validated diagnostic pathway.
Preoperative knowledge of tumor genetics fundamentally transforms surgical decision-making and patient counseling. When neurosurgeons anticipate an isocitrate dehydrogenase mutation, they often pursue aggressive supratotal resection. Emerging evidence indicates that extending tumor resection into nonenhancing infiltrative cortex significantly improves overall patient survival. Conversely, aggressive debulking in wild-type tumors requires careful moderation to avoid causing irreversible neurological deficits.
Furthermore, early molecular insight enhances preoperative family discussions. Mutated gliomas carry a substantially better prognosis, which provides measurable emotional comfort during consultations. In addition, knowing molecular status preoperatively accelerates enrollment in targeted therapeutic trials. For example, novel oral inhibitors specifically target mutated metabolic enzymes to control tumor recurrence. Neurosurgeons can also employ intraoperative functional brain mapping to protect critical speech and motor pathways during cortical resection. Meanwhile, radiation oncologists can schedule adjuvant therapy protocols without awaiting lengthy genomic sequencing delays. Consequently, integrating this radiogenomic sign streamlines clinical care from admission through long-term follow-up. Ultimately, patients receive personalized, biology-driven interventions.
The clinical success of this imaging biomarker highlights the growing impact of radiogenomics in modern neuro-oncology. Routine magnetic resonance sequences offer rich pathophysiological information that healthcare teams can easily leverage. Because conventional imaging requires no proprietary tracer injections, hospitals avoid prohibitive equipment expenses. Therefore, this noninvasive approach offers immediate utility for tertiary neurosurgical centers and community clinics across India.
Moreover, artificial intelligence algorithms can help standardize the detection of nonenhancing cortical tumor spread. Deep neural networks can identify subtle cortical expansion and signal changes automatically. When paired with expert radiologist review, automated tools reduce diagnostic variability and streamline neuroimaging workflows. Furthermore, future studies will evaluate whether specific cortical patterns differentiate oligodendrogliomas from astrocytomas. Distinguishing 1p/19q codeletions noninvasively remains an exciting research objective. As clinical trials validate these tools prospectively, neuro-oncology societies may officially endorse them in clinical guidelines. Consequently, clinicians can deliver timely, personalized interventions that preserve functional capacity and improve survival outcomes.
The CONTIN sign identifies cortical nonenhancing tumor infiltration on conventional magnetic resonance imaging. Radiologists evaluate T2, FLAIR, and contrast-enhanced T1 sequences to observe neoplastic cortical invasion without contrast leakage. This distinctive pattern serves as a reliable, noninvasive radiogenomic biomarker for isocitrate dehydrogenase gene mutations across both low-grade and high-grade diffuse gliomas.
While the T2-FLAIR mismatch sign offers excellent specificity, it exhibits notoriously low sensitivity, especially in contrast-enhancing tumors. Conversely, the CONTIN sign dramatically improves diagnostic sensitivity, rising above 81% in enhancing neoplasms while maintaining specificity over 82%. Consequently, it detects mutated gliomas that traditional mismatch assessments overlook during routine neuroimaging evaluation.
Preoperative IDH status informs surgical aggressiveness, patient prognosis, and adjuvant treatment timing. IDH-mutant tumors benefit substantially from maximal supratotal resection extending into nonenhancing boundaries. In addition, early molecular confirmation facilitates targeted therapy selection, enables accurate survival counseling, and helps multidisciplinary teams design individualized therapy strategies before receiving final histopathology.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The CONTIN sign on MRI serves as a reliable radiogenomic biomarker for IDH-mutant diffuse gliomas, offering high sensitivity and specificity even in contrast-enhancing tumors to optimize preoperative surgical strategies.
last month

Momelotinib offers unique clinical benefits for myelofibrosis patients with moderate-to-severe anemia via dual JAK and ACVR1 inhibition. While registration trials show positive hematologic outcomes, emerging real-world data underscore the need for vigilant surveillance of renal function and peripheral neuropathy.
Today

Delhi is undergoing a major healthcare overhaul with enhanced Ayushman Bharat insurance up to ₹10 lakh, increased MBBS and PG medical training seats, expanded primary network mandirs, new tertiary neuro-ICUs, and public-private reproductive technology initiatives to build a resilient, preventative healthcare model.
Today
A 78-year-old patient with high-grade aneurysmal subarachnoid hemorrhage complicated by refractory Takotsubo cardiogenic shock achieved full recovery following microaxial flow pump (Impella 5.5) rescue, demonstrating the safety and feasibility of advanced mechanical circulatory support during dual antiplatelet therapy.
Today

Non-union fractures occur in 2-5% of cases, causing significant disability and cost. Conservative modalities such as LIPUS, PEMF, and focused ESWT offer non-surgical healing options for defects up to 5-10 mm when adequate mechanical stability exists without infection.
Yesterday

The randomized HOBIT-AF trial reveals that while structured weight loss after catheter ablation significantly improves cardiometabolic health in obese patients with paroxysmal atrial fibrillation, it does not reduce arrhythmia recurrence compared to standard care.
Today
