

Loading, please wait...
Loading, please wait...

Adolescent mental health challenges continue to escalate globally, posing complex diagnostic questions for pediatricians, psychiatrists, and family physicians. Frequently, clinicians encounter young patients who appear chronically lost in thought, lethargic, and emotionally withdrawn. In recent years, psychiatric literature has characterized this distinct presentation as cognitive disengagement syndrome, a clinical construct previously termed sluggish cognitive tempo. While earlier investigations linked this syndrome directly to mood disorders, questions remained regarding which cognitive factors moderate the vulnerability. Consequently, emerging empirical evidence demonstrates that a negative interpretation bias significantly magnifies this relationship. Therefore, evaluating how youth perceive ambiguous everyday scenarios provides essential insights into early adolescent depression.
Historically, clinicians grouped youth exhibiting persistent daydreaming, mental confusion, and slow processing speed under inattentive attention disorders. However, modern psychiatric research has validated cognitive disengagement syndrome as an independent neurocognitive construct. Youth affected by this condition display internal hypoarousal rather than overt physical restlessness. For example, these individuals experience persistent mental fog, diurnal lethargy, and notable delays in initiating purposeful activities. Furthermore, they struggle to sustain active mental alertness during routine academic lessons.
Importantly, this syndrome differs from classical attention-deficit/hyperactivity disorder in its emotional trajectory. While hyperactive youth externalize frustration, children with disengagement syndrome turn inward. Consequently, they experience elevated rates of internalizing distress, including social withdrawal and major depression. Because these youth remain quiet in classrooms, teachers often overlook their functional impairments. In addition, their chronic lethargy impedes academic success and healthy peer bonding. Therefore, healthcare providers must identify these distinct symptoms early to prevent lasting emotional complications. Furthermore, their slowed processing speed creates daily executive burdens that compound chronic feelings of inadequacy and low self-esteem.
Cognitive theories of depression propose that maladaptive information processing drives depressive vulnerability. Specifically, a negative interpretation bias occurs when an individual habitually assigns threatening meaning to ambiguous situations. For instance, when a peer does not reply to a greeting, a biased adolescent assumes intentional rejection. Similarly, when receiving neutral feedback on schoolwork, they infer personal incompetence and failure. Thus, benign social interactions transform into distressing subjective experiences.
Furthermore, empirical evidence reveals that interpretation biases do not simply accompany sadness. Rather, these cognitive distortions actively maintain depressive episodes over time. When youth consistently interpret events through a negative lens, their perceived self-efficacy deteriorates. In addition, these distorted appraisals promote persistent rumination and hopeless thought cycles. Because early adolescence involves shifting peer hierarchies, this developmental period represents a vulnerable window. Consequently, understanding how cognitive processing habits interact with neurodevelopmental traits is critical for clinicians. As a result, uncorrected cognitive biases solidify into rigid depressogenic schemas that resist natural self-correction during interpersonal stress.
To investigate these interconnected phenomena, researchers examined a well-defined cohort of 336 early adolescents. Specifically, the participants ranged from 10 to 12 years of age. The investigation employed a rigorous multi-informant design, capturing ratings from both adolescents and caregivers. In addition, the researchers measured interpretation bias objectively using the Scrambled Sentences Test. This computerized cognitive task requires youth to unscramble word strings under cognitive load, revealing implicit interpretive habits.
The regression analyses yielded compelling findings regarding depressive symptom manifestation. For adolescent-reported depressive symptoms, cognitive disengagement syndrome and interpretation bias each independently predicted higher depression scores. However, the interaction between these two variables was not statistically significant in adolescent reports. In contrast, a significant interaction emerged when analyzing caregiver-reported depressive symptoms. Specifically, cognitive disengagement syndrome was more strongly associated with depression among youth with high interpretation bias. Therefore, cognitive interpretation bias clearly moderates the behavioral manifestation of depression observed by parents. Moreover, these statistical interactions underscore that cognitive distortions magnify observable clinical dysfunction within family and academic environments.
The divergence between adolescent self-reports and caregiver observations provides profound clinical lessons. In clinical settings, pediatricians and psychiatrists frequently encounter informant discrepancies during adolescent evaluations. In fact, caregivers primarily observe externalized indicators of emotional withdrawal and behavioral lethargy. When an adolescent suffers from severe disengagement and harbors a negative cognitive bias, outward slowing becomes visible. Consequently, parents notice reduced participation in family routines, neglected hobbies, and declining academic performance.
Conversely, adolescents evaluate internal emotional anguish, loneliness, and subjective feelings of sadness. To an adolescent, chronic mental fog and negative thoughts feel distressing regardless of external confirmation. Therefore, relying exclusively on either child self-reports or caregiver ratings introduces diagnostic error. A multi-informant protocol allows clinicians to bridge the gap between subjective despair and functional impairment. Furthermore, integrating performance-based cognitive tests eliminates reporting bias. Ultimately, comprehensive multi-method assessments generate a solid foundation for targeted therapeutic planning. In clinical practice, collecting collateral reports from educators further refines diagnostic precision and highlights unnoticed contextual triggers across settings.
These empirical insights carry direct therapeutic implications for managing vulnerable early adolescents. Traditionally, clinicians treat attentional sluggishness with stimulant medications, yet these drugs show variable efficacy. Instead, psychological interventions must target the maladaptive information processing that amplifies depressive risk. Specifically, cognitive behavioral therapy can teach adolescents to challenge automatic negative appraisals during ambiguous social interactions. By reframing these distorted thoughts, clinicians can disrupt the pathway leading to clinical depression.
Additionally, clinicians should implement behavioral activation tailored to lethargic presentations. Because disengagement syndrome causes mental exhaustion, patients benefit from structured daily routines and graded activities. Furthermore, psychoeducation helps parents understand that cognitive slowness reflects an authentic neurocognitive trait. When caregivers reduce criticism, household stress decreases substantially. In conclusion, combining cognitive restructuring with functional environmental support provides the most comprehensive clinical protection. Furthermore, clinicians should schedule routine follow-up consultations to evaluate mood stability and adapt psychotherapeutic interventions as cognitive maturity develops.
Cognitive disengagement syndrome involves internal hypoactivity, frequent daydreaming, mental fogginess, and sluggish information processing. In contrast, inattentive attention-deficit/hyperactivity disorder primarily reflects external distractibility, poor organizational skills, and executive dysfunction. While both conditions impair academic performance, adolescents with disengagement syndrome lack the impulsivity typically observed in classical attention-deficit disorders.
Negative interpretation bias causes youths to habitually interpret ambiguous social cues or neutral events as threatening or intentionally rejecting. Consequently, this cognitive distortion magnifies feelings of helplessness and perceived failure. When combined with slow processing or mental lethargy, these persistent negative appraisals accelerate the onset and severity of depressive illness.
Caregivers usually evaluate observable external behaviors, such as academic withdrawal, social retreat, and psychomotor slowing. Conversely, adolescents report their private emotional pain and internal distress that parents may not immediately observe. Therefore, clinicians must gather multi-informant reports to build an accurate clinical picture and prevent underdiagnosing masked mood disorders.
Disclaimer: This content is for informational and educational purposes only and should not be considered as professional medical advice, diagnosis, or treatment. It is not intended to replace consultation with qualified healthcare professionals. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A multi-informant study reveals that negative interpretation bias significantly moderates the relationship between cognitive disengagement syndrome and depressive symptoms in early adolescents, emphasizing the critical value of multi-method psychiatric evaluations in pediatric practice.
Today

Cardiac involvement is the leading cause of mortality in EGPA. This report highlights an overlap phenotype of lymphocyte-predominant myocardial injury, Takotsubo-like cardiomyopathy, and left ventricular thrombus, emphasizing early multimodality diagnostics and aggressive immunosuppressive biologic therapy.
Today
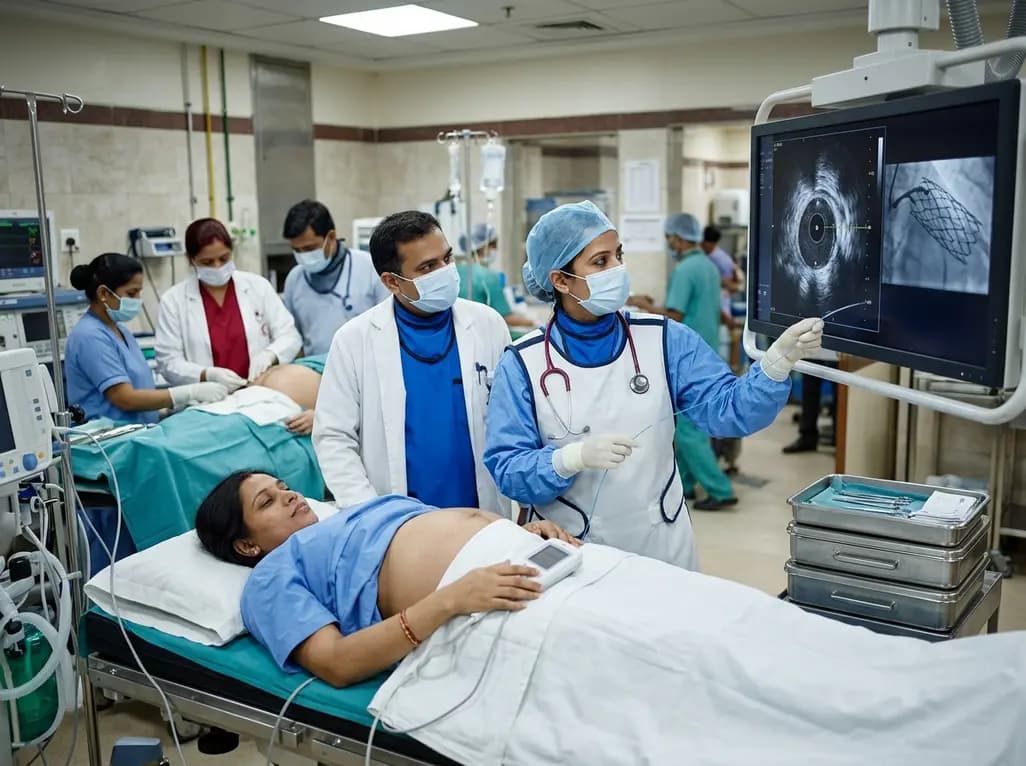
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today
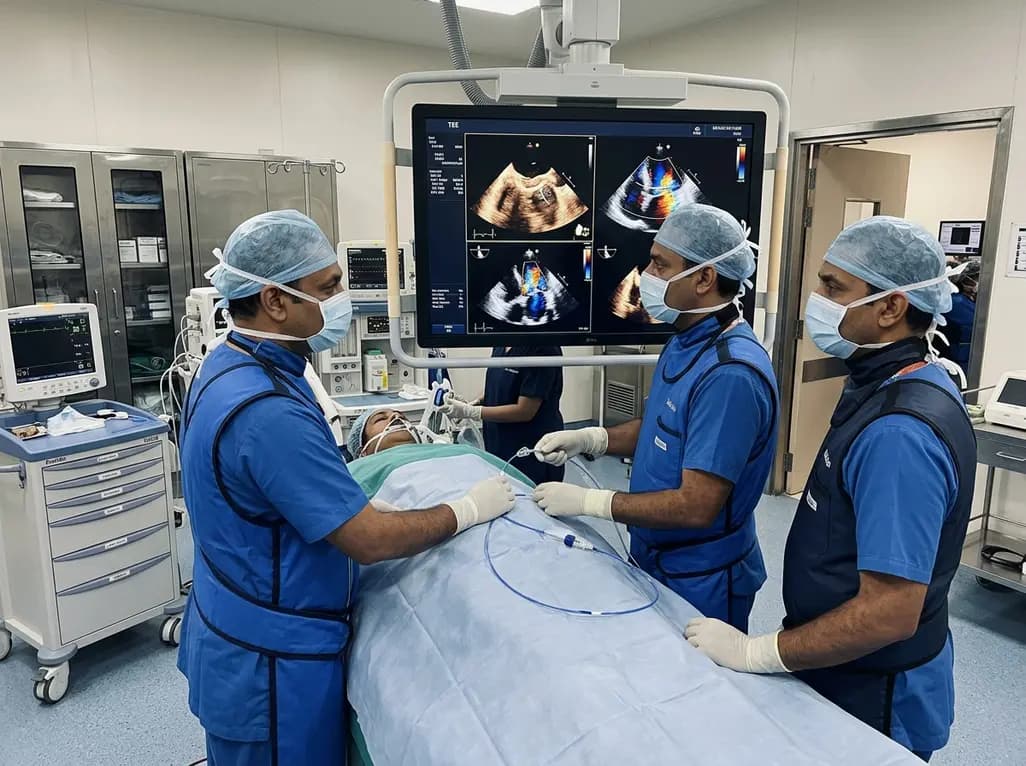
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today
